Related Experiment Video
Updated: Sep 23, 2026
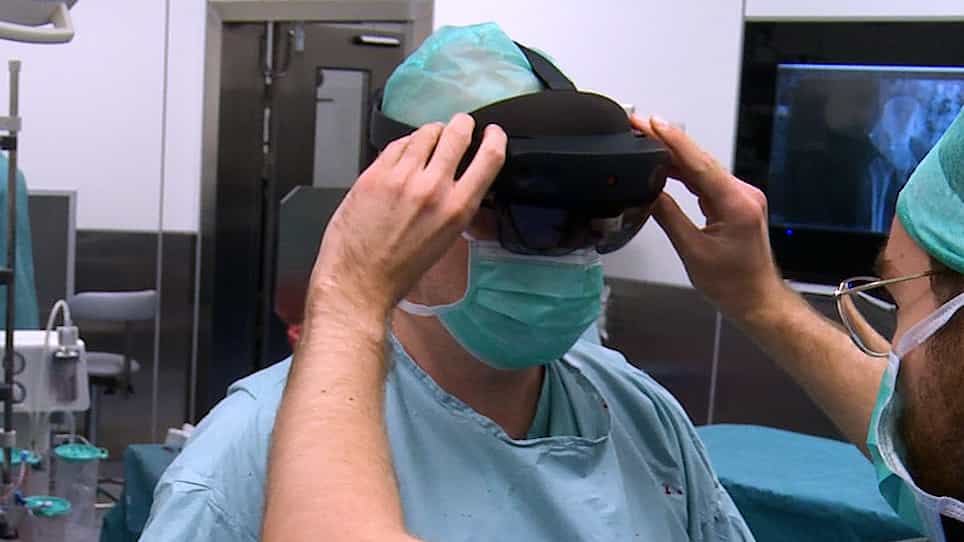

The Use of Mixed Reality in Custom-Made Revision Hip Arthroplasty: A First Case Report
Published on: August 4, 2022
Temporal Trends in Surgical Site Infections After Hip and Knee Arthroplasty in California, 2015 to 2024
Farzad Haji Boloori1, Alex Kubiak1, McCord Meyers1
1Kansas City University College of Osteopathic Medicine, 2901 St. Johns Boulevard, Joplin, Missouri 64804, USA.

Background:
Surgical site infections (SSI) following primary total hip arthroplasty (THA) and total knee arthroplasty (TKA) remain clinically consequential and economically burdensome adverse events. Despite California's decade-long mandatory SSI surveillance system and public reporting of Standardized Infection Ratios (SIR), it remained unclear whether hospital arthroplasty volume, policy implementation, or the COVID-19 pandemic were associated with population-level SSI risk. We examined temporal trends in SSI rates after primary THA and TKA in California, and whether hospital volume, policy epoch, or the COVID-19 pandemic was associated with SSI risk.
Methods:
We conducted a retrospective, facility-level longitudinal cohort study using state-mandated healthcare-associated infection surveillance data for hip and knee arthroplasty procedures performed in California from 2015 through 2024. The analytic unit was the hospital-year-procedure stratum, and the final panel comprised 5,880 hospital-year-procedure observations. Hospitals were categorized into low (less than 25 procedures/year), medium (25 to 100), or high (greater than 100) baseline annual volume. Generalized linear models with a log link and log-procedure offset estimated adjusted incidence rate ratios (IRR) for SSI, with covariates for year, policy epoch, procedure type, and volume category.
Results:
Crude SSI rates were consistently higher for hip than knee arthroplasty (range, 0.5 to 0.7% versus 0.3 to 0.4% annually). In adjusted models, knee arthroplasty had an IRR of 0.62 (95% confidence interval [CI], 0.57 to 0.68) versus hip. Hospital volume demonstrated no association with SSI risk; medium-volume (IRR 1.07; 95% CI, 0.78 to 1.47) and high-volume (IRR 1.07; 95% CI, 0.79 to 1.44) hospitals did not differ from low-volume hospitals. Epoch indicators and linear year terms were non-significant across all models.
Conclusion:
In a statewide analysis, SSI rates following primary THA and TKA remained low and stable across hospital settings, policy periods, and the COVID-19 era. Hospital-level procedure volume was not associated with SSI incidence, and no temporal shifts corresponded to public reporting implementation or pandemic disruption.
Related Concept Videos
 01:22
Healthcare Associated Infections II: Preventive Measures
The best practices for preventing healthcare-associated infections include hand hygiene, patient risk...
 01:26
Healthcare Associated Infections I: Iatrogenic, Exogenic and Endogenic
HAIs significantly increase the cost of health care. Extended stays in healthcare institutions, increased disability, increased costs of medications, including specialized antibiotics, and prolonged recovery times add to the patient's expenses and the healthcare institution and funding bodies. Common...