Related Experiment Video
Updated: Sep 23, 2026


Measurement of Factor V Activity in Human Plasma Using a Microplate Coagulation Assay
Published on: September 9, 2012
The hidden threat: understanding anti-PF4 disorders without proximate heparin exposure
Zhiyan Liu1, Yan Li2, Liang Ma2
1Institute of Clinical Pharmacology, Peking University First Hospital, Beijing, China.

Abstract:
Heparin-induced thrombocytopenia (HIT) is now recognized as one subset of a broader group of disorders: anti-platelet factor 4 (anti-PF4) disorders. This review provides an updated framework for anti-PF4 immunothrombosis without proximate heparin exposure-a clinical syndrome with phenotypic and laboratory features resembling classic HIT but with no recent heparin use (no heparin exposure within 14 days before onset). The core characteristics are a ≥50% platelet count decrease from baseline or an absolute platelet count <100×109/L, often associated with elevated arterial or venous thrombosis risk. Historically, these heparin-independent syndromes encompass spontaneous HIT-like syndrome, vaccine-induced immune thrombotic thrombocytopenia (VITT/TTS), and autoimmune HIT (aHIT)-notably, nearly all aHIT cases are initiated by prior heparin exposure before progressing to sustained heparin-independent platelet-activating antibodies. This review exclusively focuses on patients with no heparin exposure within 14 days of symptom onset, including: (1) patients with prior heparin exposure >14 days ago whose antibodies have evolved heparin-independent pathogenicity (aHIT), (2) patients with truly spontaneous HIT-like syndrome without any prior heparin, and (3) VITT. For aHIT specifically, prior heparin exposure is the initiating event in >95% of cases, but the antibodies become heparin-independent over time; thus these patients fall within our 14-day window of interest when presenting with delayed-onset thrombocytopenia beyond the acute heparin exposure phase. Pathogenesis centers on PF4-driven abnormal immune responses: PF4 forms complexes with polyanions (von Willebrand factor [VWF], pathogen surface molecules, etc.), inducing pathogenic antibodies that activate platelets via FcγRIIA, creating a self-amplifying "immune activation-thrombosis" cycle. Diagnosis requires combined clinical, laboratory, and imaging evaluation to distinguish from other thrombocytopenia-with-thrombosis disorders. Current treatment includes non-heparin anticoagulation plus high-dose IVIG for heparin-independent forms. Future research should validate diagnostic criteria, biomarkers, and targeted therapies.
More Related Videos
 04:37
Comprehensive Analysis of Procoagulant Platelets Exhibiting Features of Necrosis, Apoptosis and Platelet Activation
Published on: May 23, 2025
 08:01
The Nijmegen Hemostasis Assay: Simultaneous Fluorogenic Measurement of Thrombin and Plasmin Generation in a Single Well
Published on: February 27, 2026
Related Concept Videos
 01:24
Disorders of Hemostasis
Thromboembolic Disorders
Two factors primarily cause thromboembolic conditions.
 01:30
Anticoagulant Drugs: Low-Molecular-Weight Heparins
 01:36
Humoral Immune Responses
 01:29
Venous Thrombosis III: Interprofessional Care
 01:19
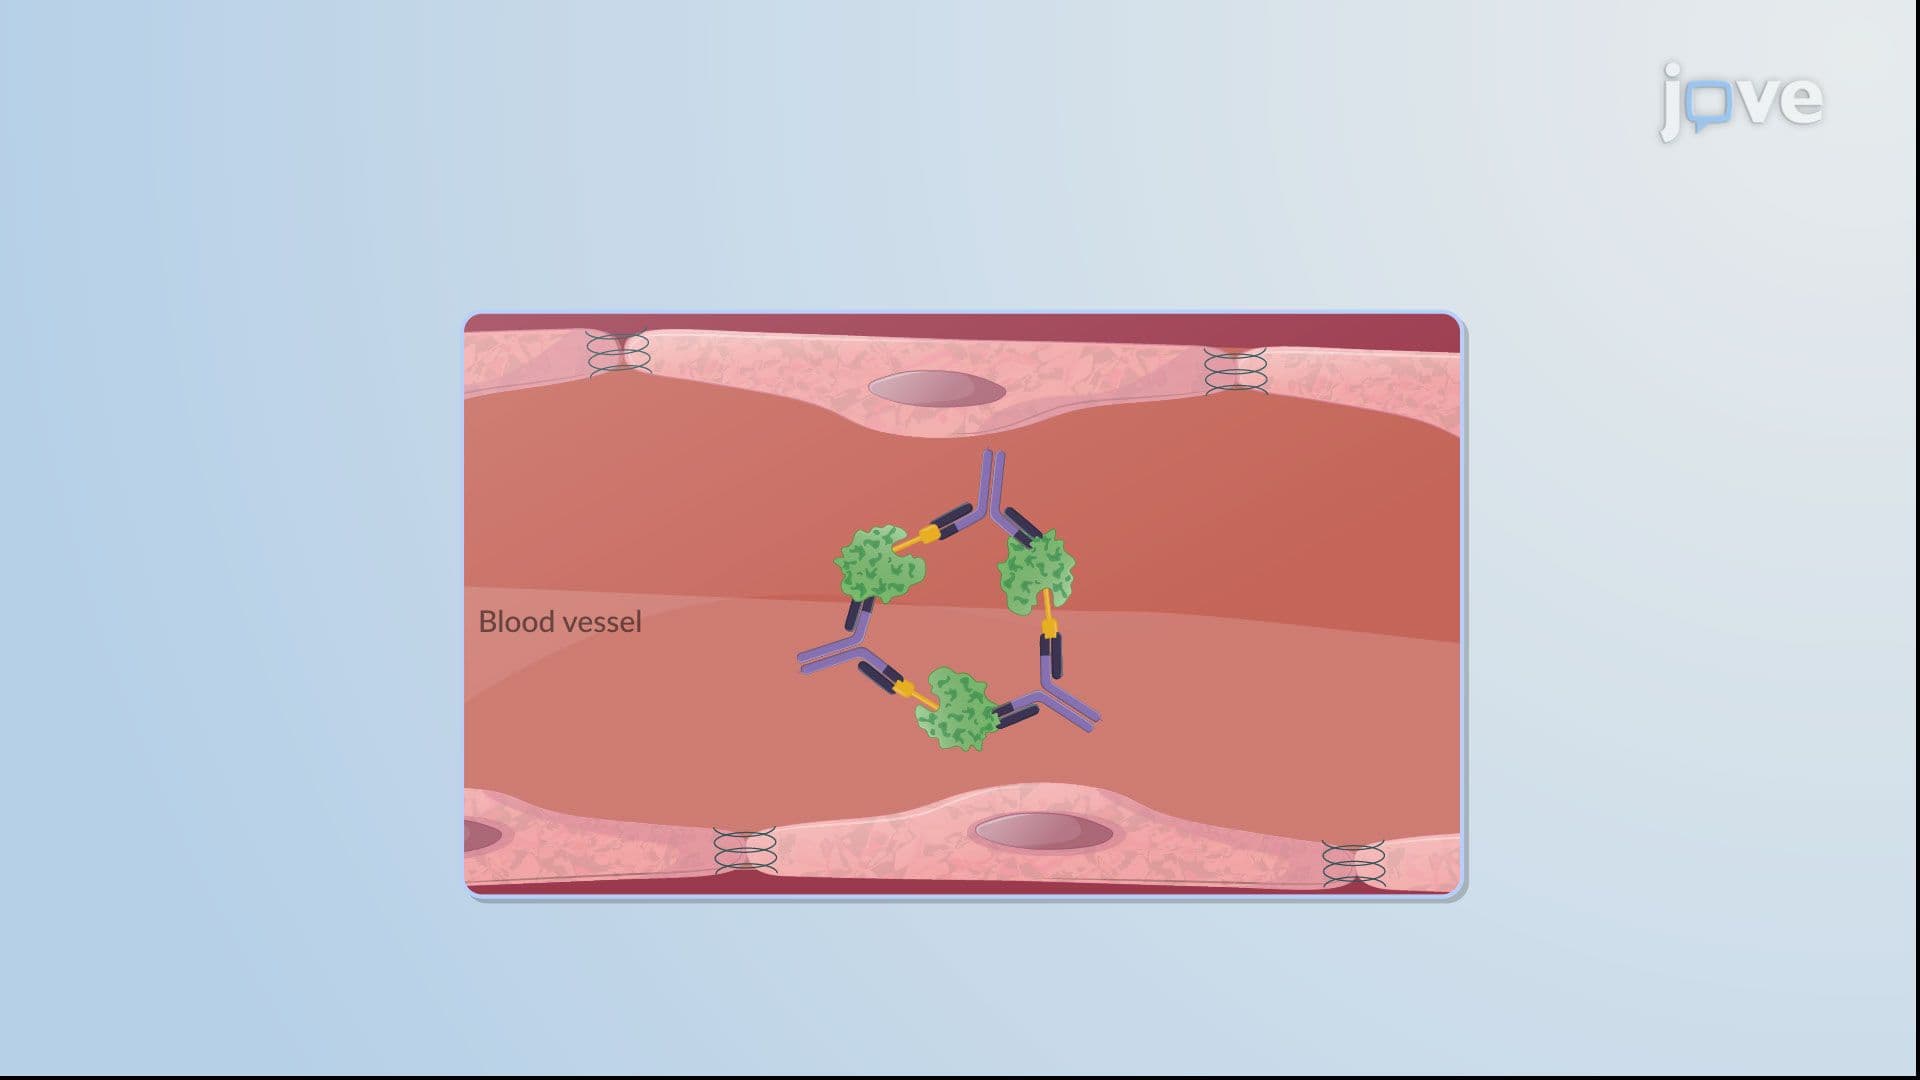
Hypersensitivity Reactions: Immune-Complex Reactions
 01:20
Extrinsic and Intrinsic Pathways of Hemostasis
The Extrinsic Pathway
The extrinsic pathway of coagulation is typically initiated by tissue damage that exposes blood to tissue factor (TF), a protein released by the damaged tissue cells outside the blood vessels—this interaction with TF triggers biochemical reactions involving specific clotting factors. The key player here is Factor VII, which forms a...