Related Experiment Video
Updated: Sep 23, 2026

Treatment of Ejaculatory Duct Obstruction by Seminal Vesiculoscopy Assisted Flow Modification
Published on: December 8, 2023
Ejaculation sparing versus standard technique in bladder outlet obstruction procedures: a systematic review,
David E Hinojosa-Gonzalez1, Alejandro Calvillo-Ramirez2, Andres Gutierrez-Gamez3
1Scott Department of Urology, Baylor College of Medicine, Houston, TX 77030, United States.

Introduction:
Surgical management of benign prostatic hyperplasia (BPH) effectively improves urinary symptoms in patients refractory to medical therapy; however, loss of antegrade ejaculation (AE) remains a major drawback of BPH procedures. Ejaculation-sparing (ES) techniques have been proposed to address this limitation, although their impact on functional urinary outcomes remains uncertain.
Objectives:
This study aimed to evaluate AE preservation rates and functional outcomes of ES approaches compared with the standard technique in BPH surgeries.
Methods:
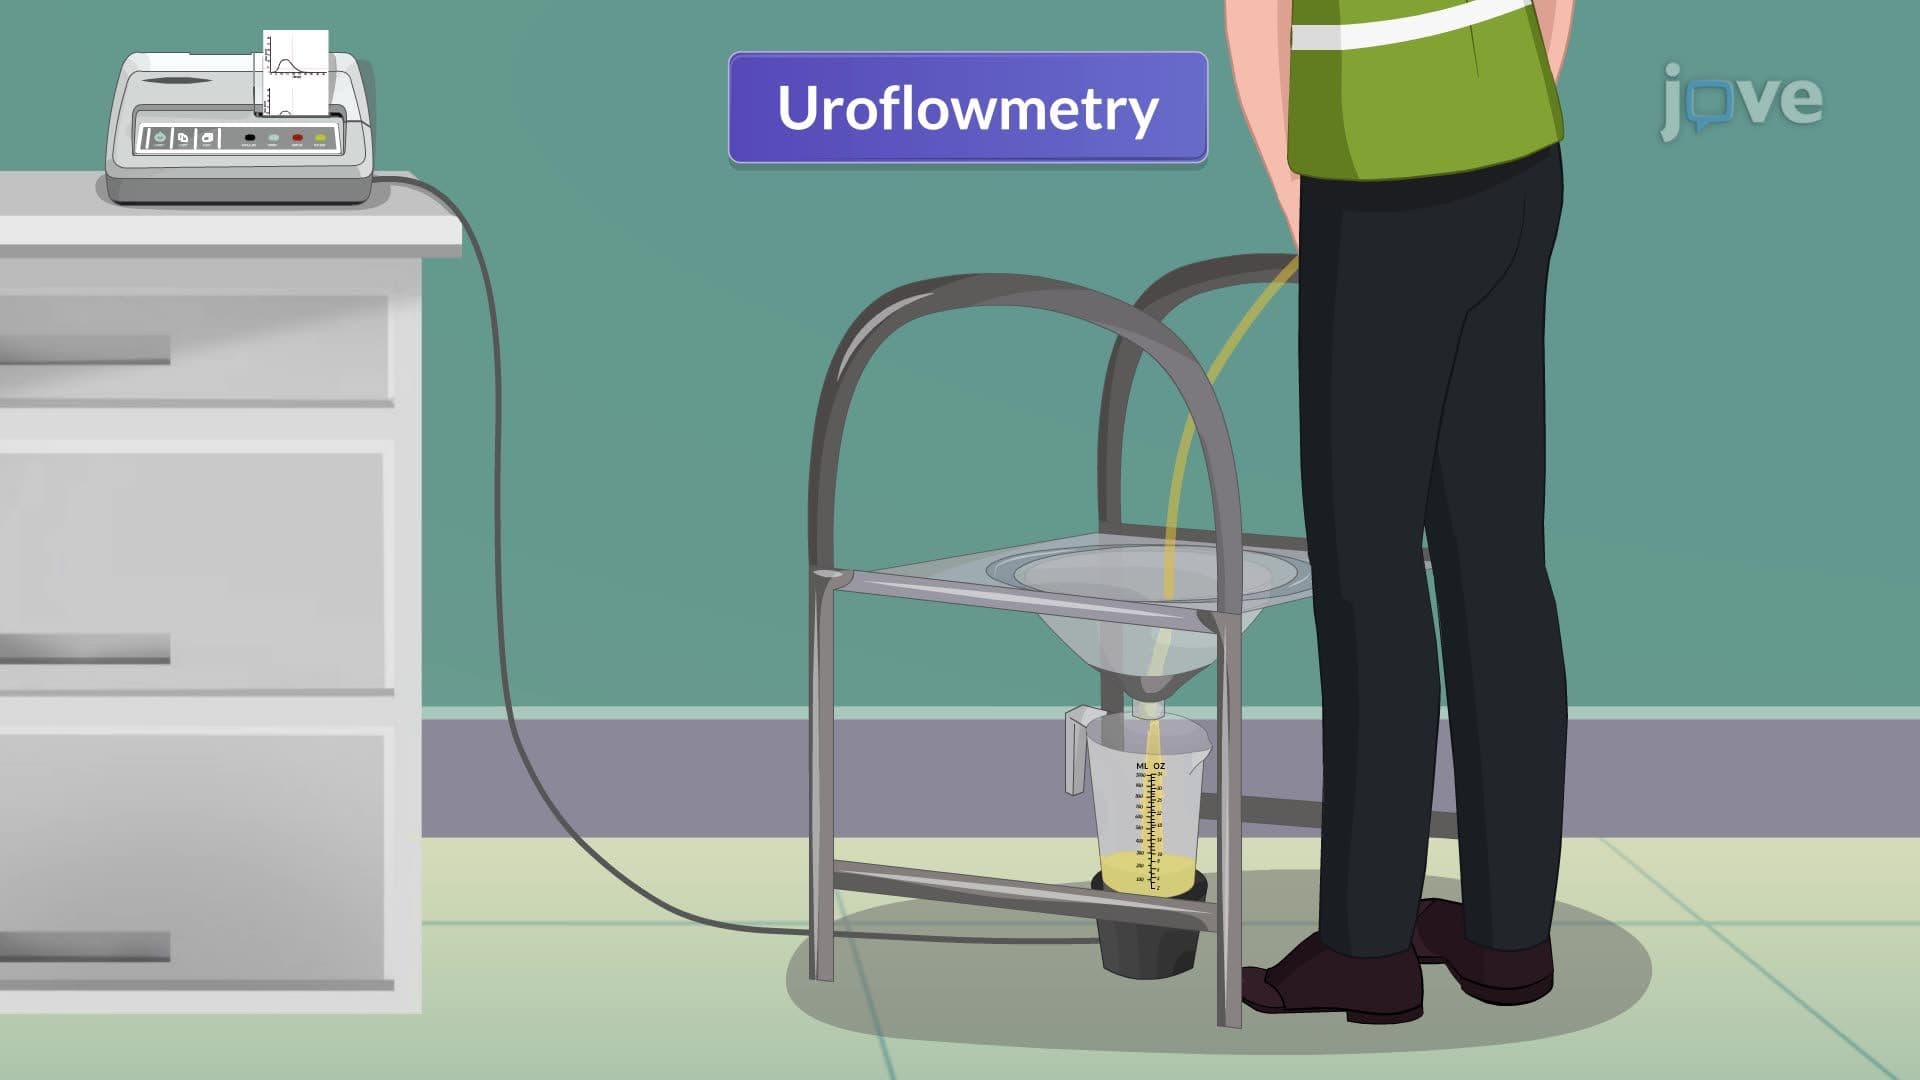
A systematic review and meta-analysis were conducted adhering to the Preferred Reporting Items for Systematic reviews and Meta-Analyses (PRISMA) guidelines. PubMed, Embase, and Scopus databases were searched to identify randomized and non-randomized studies comparing ES and standard techniques for BPH surgery. The primary outcome was preservation of AE. Secondary outcomes included International Prostate Symptom Score (IPSS), International Index of Erectile Function (IIEF), and maximum urinary flow rate (Qmax).
Results:
Sixteen studies (9 randomized and 7 observational) comprising 1493 patients were included. Ejaculation-sparing techniques demonstrated significantly higher AE preservation rates compared with the standard approach (OR: 6.76, 95% CI: 3.86-11.84, P < .001). In anatomy-based subgroup analyses, ES techniques were associated with greater AE preservation in the localized peri-verumontanum/apical preservation subgroup (OR: 5.79, 95% CI: 2.73-12.29) and the combined bladder-neck and supramontanal preservation subgroup (OR: 17.79, 95% CI, 7.12-44.42), whereas the extended urethral/ejaculatory-tract preservation subgroup demonstrated an OR of 3.95 (95% CI: 0.98-15.94); the test for subgroup differences was not significant (P = .09). At 6-12 months postoperatively, no significant between-group differences were observed in IPSS (MD: 0.05, 95% CI, -1.59 to 1.68, P = .95), Qmax (MD: -0.68, 95% CI, -2.00 to 0.64, P = .31). Similarly, early postoperative IIEF-5 scores did not differ significantly between groups (MD: 0.94, 95% CI: -0.19 to 2.07, P = .10).
Conclusions:
Ejaculation-sparing techniques conferred greater preservation of AE compared with standard BPH procedures, without adversely affecting urinary or sexual functional outcomes at short-term follow-up. These findings support consideration of ES techniques in appropriately selected patients for whom preservation of sexual function is a priority. Further prospective studies with standardized surgical definitions and longer follow-up periods are warranted to determine the long-term efficacy and durability of these approaches.