Related Experiment Video
Updated: Sep 25, 2026
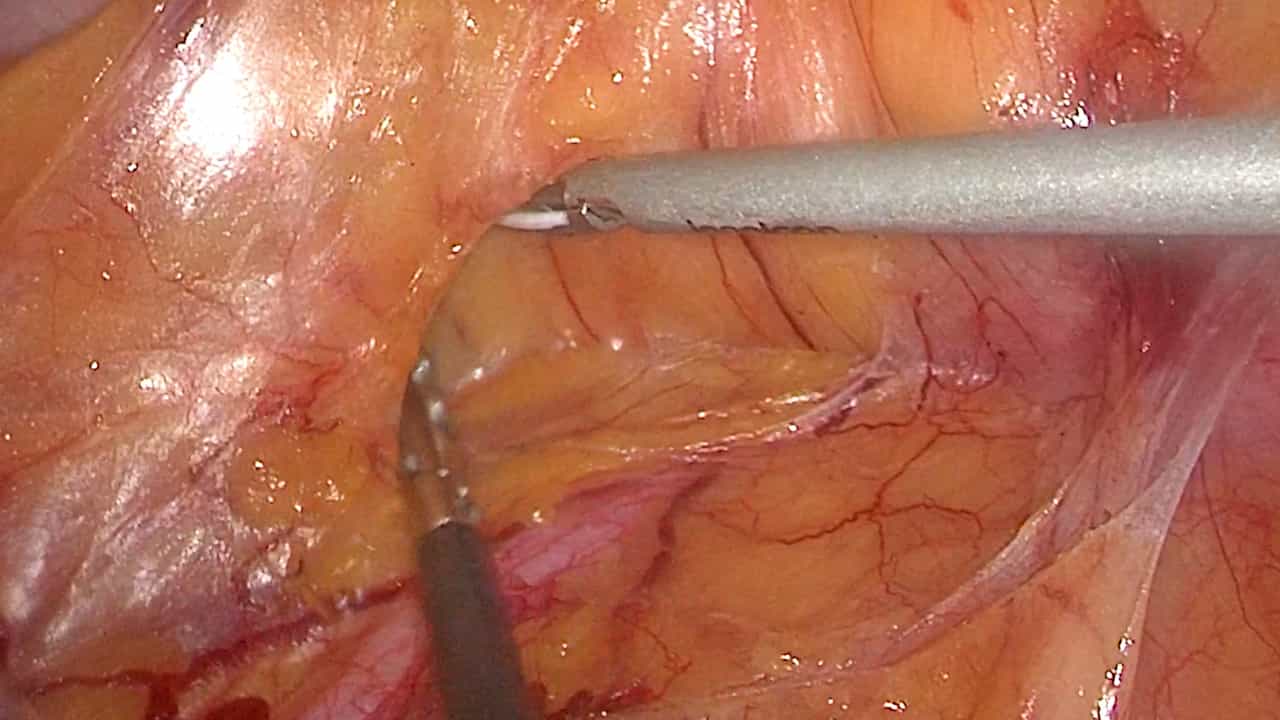
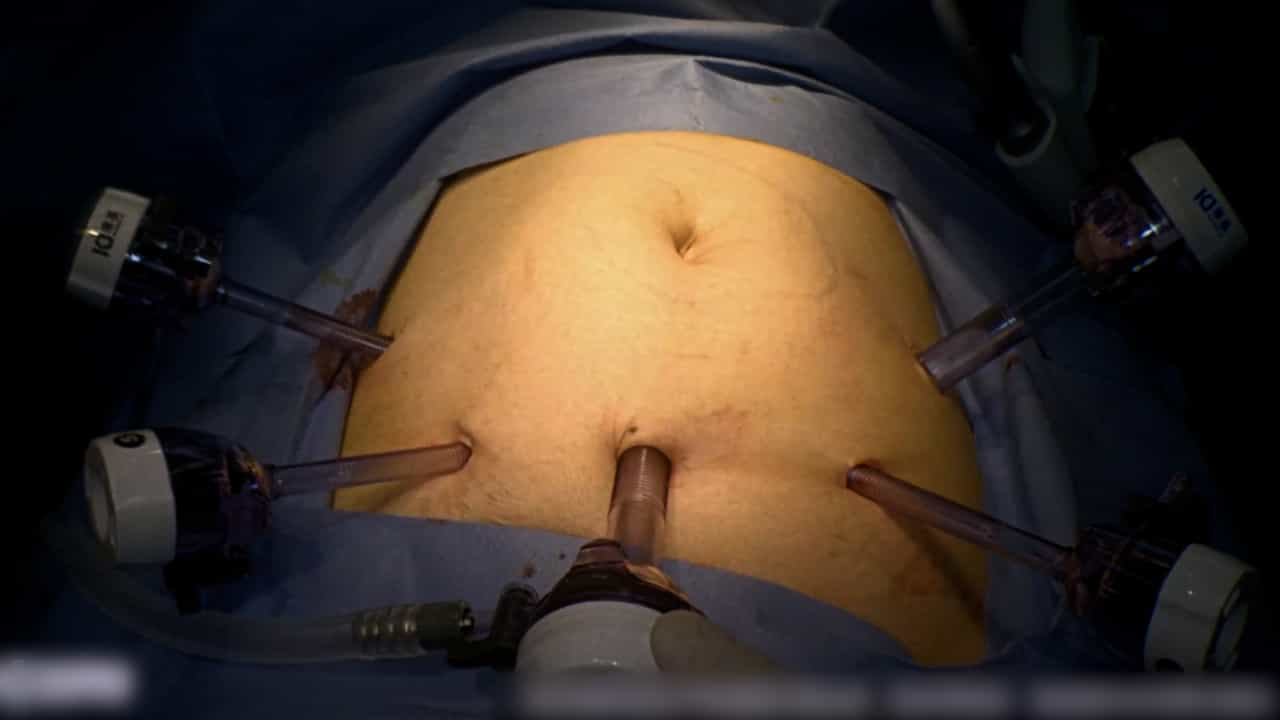
Caudal-to-cranial Approach in Laparoscopic Right Hemicolectomy with Complete Mesocolon Excision and D3 Lymph Node Dissection
Published on: January 9, 2026
Impact of an institutional shift to intracorporeal anastomosis on postoperative outcomes after laparoscopic right
Federico Ghignone1, Davide Zanotti2, Margherita Minghetti3
1Department of Medical and Surgical Sciences, University of Bologna, Bologna, Italy; Colorectal and General Surgery Unit, Ospedale Santa Maria delle Croci-Ravenna, Ravenna, Italy.

Purpose:
Variation in surgical technique remains an important source of heterogeneity in postoperative outcomes after colorectal surgery. Although enhanced recovery pathways have standardized perioperative care, less attention has been devoted to the systematic standardization of surgical techniques. We evaluated whether the implementation of a standardized institutional program that adopts intracorporeal anastomosis during laparoscopic right colectomy for cancer was associated with improved postoperative outcomes.
Methods:
This was a single-center retrospective pre-post cohort study. The primary outcome was the rate of incisional hernia at the extraction site. Secondary outcomes included postoperative complications, reintervention, unplanned readmission, and postoperative length of stay. Patients were stratified according to the anastomotic technique. Multivariable regression models were used to adjust for clinically relevant confounders. A propensity score matched analysis was performed to mitigate selection bias.
Results:
A total of 438 patients were included. Institutional implementation of intracorporeal anastomosis correlated with a lower rate of incisional hernia than extracorporeal anastomosis (2.5% vs 13.1%; P <.001). On adjusted analysis, intracorporeal anastomosis remained independently associated with reduced odds of incisional hernia (odds ratio, 0.15; 95% CI, 0.05-0.46; P <.001) and shorter length of stay. No significant differences were observed in overall complications, anastomotic leak, ileus, bleeding, reintervention, or readmission. These findings were consistent in the propensity score matched cohort.
Conclusion:
Institutional standardization of intracorporeal anastomosis during laparoscopic right colectomy was associated with improved recovery and a marked reduction in extraction-site hernia without compromising postoperative safety. These findings suggest that standardizing surgical technique, alongside established enhanced recovery pathways, may represent an effective strategy for improving the quality of colorectal surgical care.