Related Experiment Video
Updated: Sep 24, 2026


Application of Granger Causality Analysis of the Directed Functional Connection in Alzheimer's Disease and Mild Cognitive Impairment
Published on: August 7, 2017
Multimodal network alterations in diagnosis-age-defined early- and late-onset Alzheimer's disease
Zesong Yuan1, Jing Wang1, Baohua Cheng1
1First Clinical Medical College of Guangzhou University of Chinese Medicine, Guangzhou, China.

Introduction:
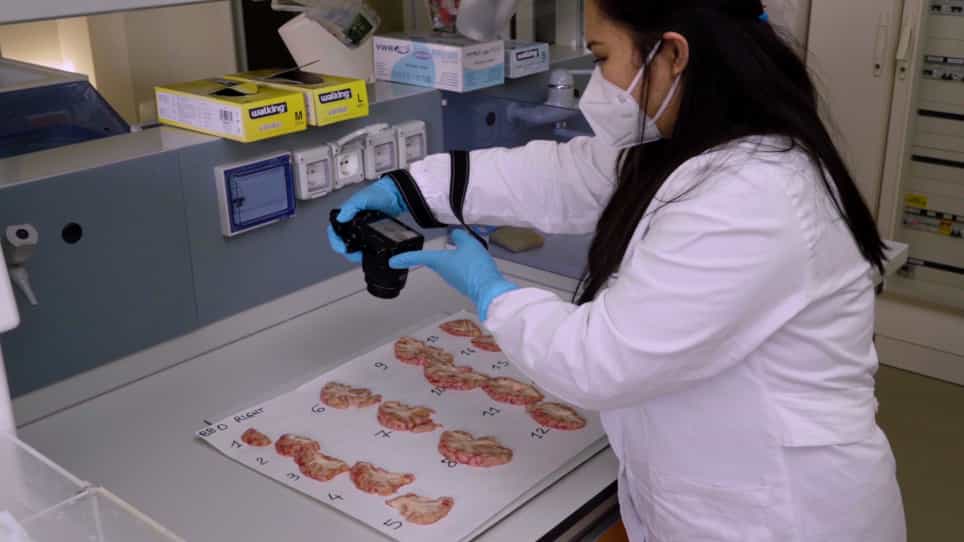
Early-onset Alzheimer's disease (EOAD) and late-onset Alzheimer's disease (LOAD) may differ in large-scale network organization. We compared multimodal MRI markers of diagnosis-age-defined Alzheimer's phenotypes.
Methods:
Alzheimer's Disease Neuroimaging Initiative participants were classified by age at first recorded mild cognitive impairment or Alzheimer's disease diagnosis: <65 years for EOAD and ≥65 years for LOAD. Retrospective symptom-onset information was consistent with this grouping when available. We assessed resting-state functional measures, graph-theoretical nodal metrics, structural-functional coupling (SFC), structural decoupling, and DTI-derived measures. Primary models adjusted for age and sex; sensitivity analyses examined nonlinear age, covariate overlap, clinical severity, disease stage, atrophy, biomarkers, head motion, regional coverage, and control-group composition.
Results:
The functional cohort included 50 EOAD, 72 LOAD, and 113 healthy controls. Global mean SFC showed only a modest group effect. LOAD showed higher regional SFC than EOAD in four frontal regions after false discovery rate correction. Graph-theoretical effects were predominantly nominal: only the overall three-group effect in Vermis 9 nodal efficiency survived within-family correction, and no EOAD-versus-LOAD nodal contrast survived. DTI-derived regional measures and structural decoupling were less subtype-discriminative. All four frontal effects remained significant after mean Power framewise displacement adjustment and overlap weighting, with bootstrap confidence intervals excluding zero. However, corrected support narrowed to one region in the nonlinear-age model and disappeared in disease- stage-, APOE ε 4-, amyloid PET-, and centiloid-adjusted models; restriction to amyloid-negative controls also retained one region.
Conclusion:
In the primary model, diagnosis-age-defined LOAD showed higher frontal regional SFC than EOAD. The absence of corrected EOAD-versus-LOAD graph findings, variable sensitivity-analysis support, and lack of corrected SFC-clinical associations indicate a model-sensitive network phenotype rather than a definitive onset-age biomarker or clinically validated subtype marker.

Related Concept Videos
 01:26
Alzheimer's Disease: Overview
The clinical diagnosis of AD hinges on the presence of memory and other cognitive impairments. Biomarkers, such as changes in Aβ and tau...
 01:22
Alzheimer's Disease: Treatment
 01:30
Dementia
The progression of dementia is generally gradual.
 01:29
Alzheimer Disease l: Introduction
 01:23
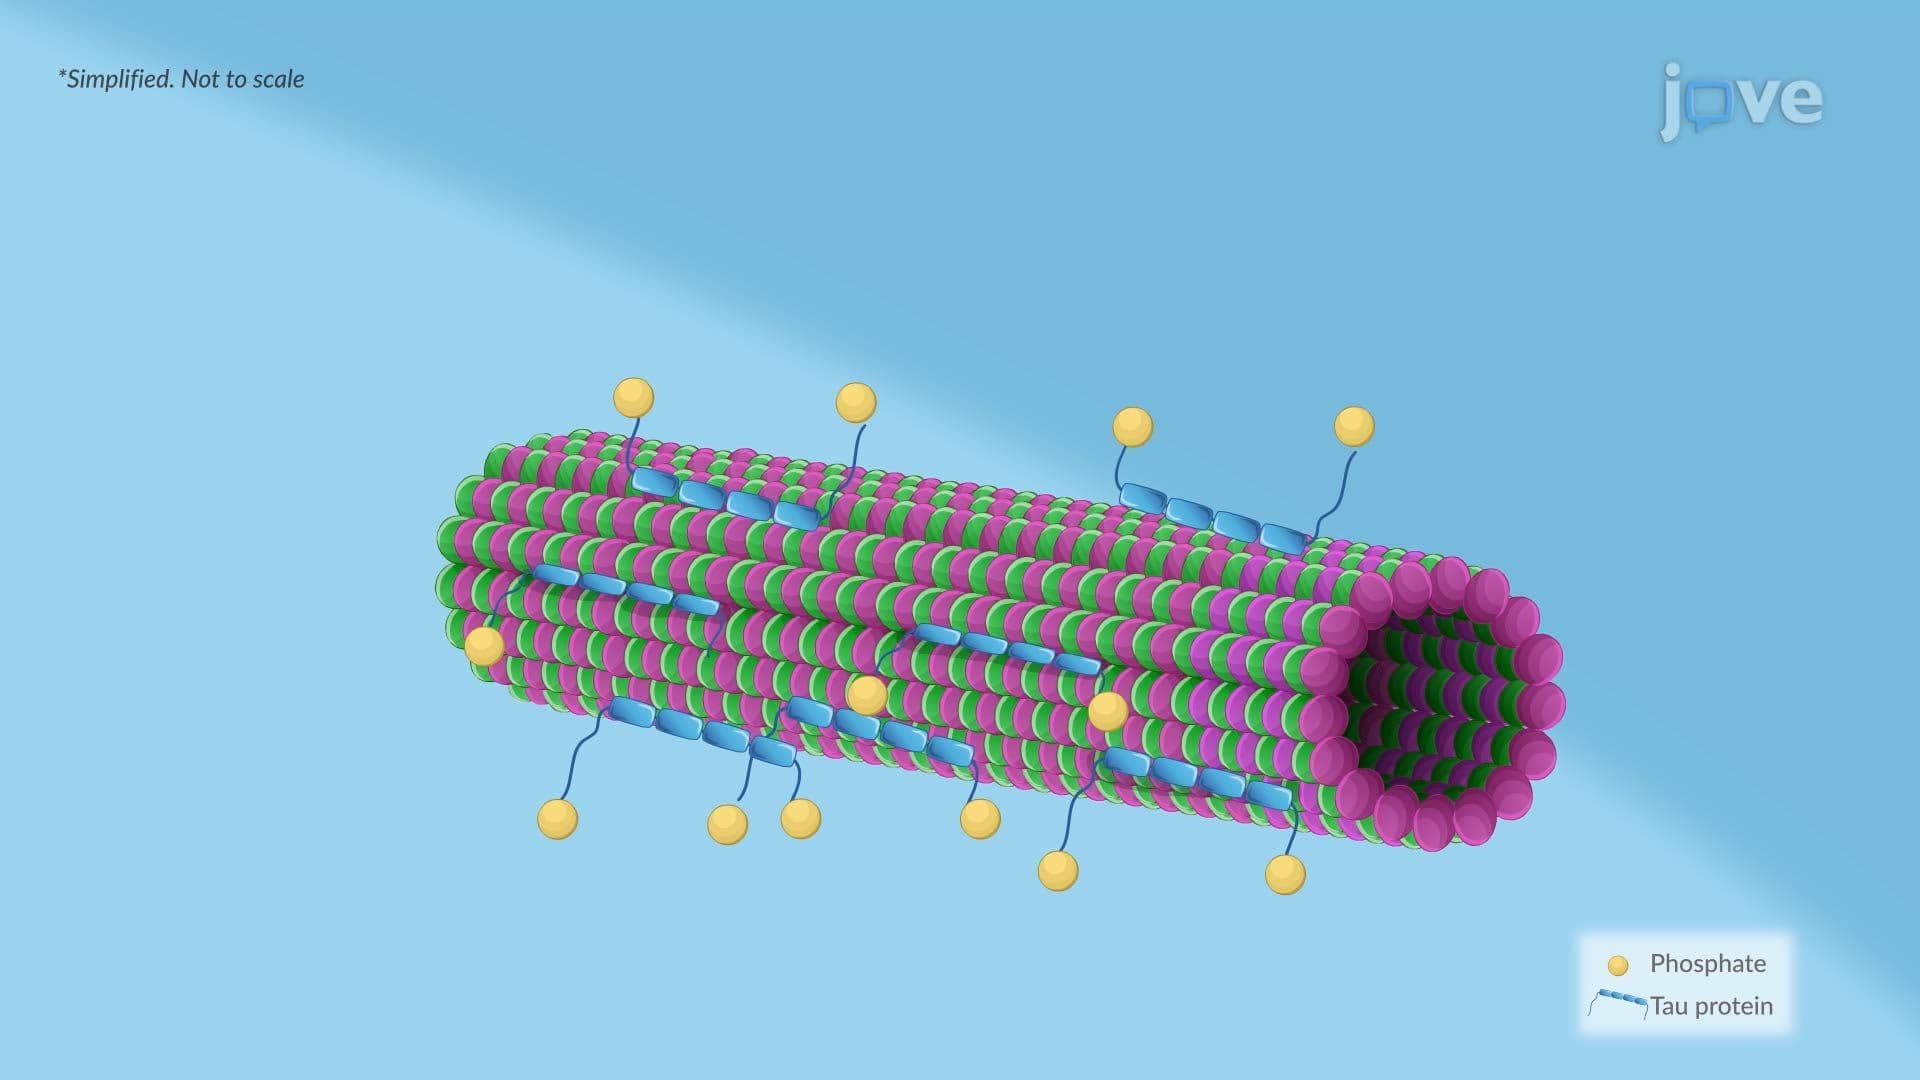
Alzheimer Disease ll: Pathophysiology
 01:22
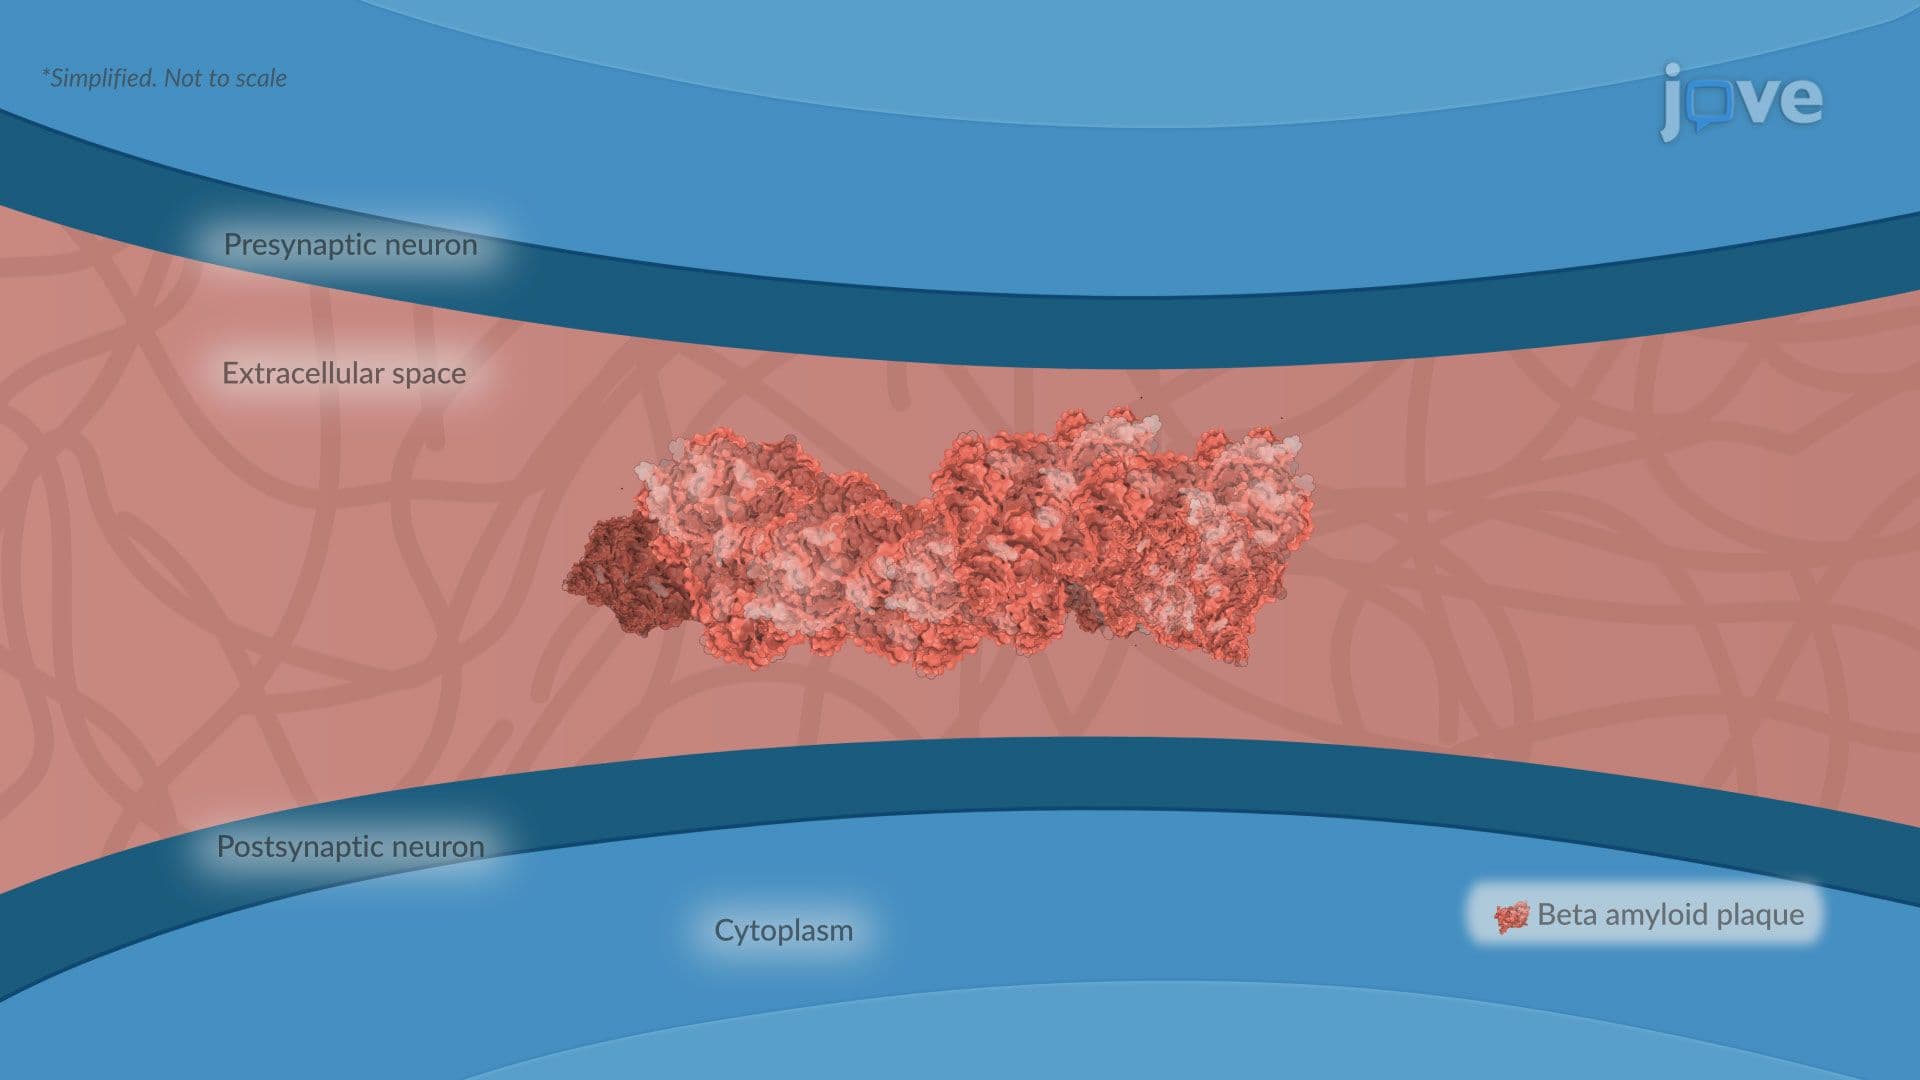
Dementia l: Introduction