
Meropenem Dosing for Pediatric Critical Care Patients: Multisite Pharmacokinetic Study, 2012-2020
Anh Thi Van Nguyen1, Evelyn Dhont1,2, Zhiyuan Tan1
1Department of Basic and Applied Medical Sciences, Faculty of Medicine and Health Sciences, Ghent University, Ghent, Belgium.

Objectives:
Critically ill children may present with altered pharmacokinetics (PK) and/or pharmacodynamics (PD), leading to suboptimal dosing of meropenem. We aimed to: 1) investigate meropenem PK in critically ill children, 2) identify factors associated with interindividual PK variability, and 3) evaluate the PK/PD target attainment rates of current and alternative dosing strategies against the most used PK/PD targets.
Design:
Observational PK study with plasma samples taken after the first and steady state doses after receiving IV meropenem. Data were analyzed using nonlinear mixed-effects modeling. Monte Carlo simulations were performed to evaluate the probability of PK/PD target attainment for different dosing strategies within the first 48 hours of treatment.
Setting:
Neonatal and PICU of two Belgian tertiary care hospitals, 2012-2020.
Patients:
Fifty-four critically ill children (7 d to 14.5 yr old) receiving meropenem infusion at 20-40 mg/kg every 6, 8, or 12 hours.
Interventions:
None.
Measurements And Main Results:
Four hundred twenty-three plasma samples were used for population PK analysis. A two-compartment model with allometric scaling and a sigmoidal maturation function accounting for the effects of growth and development best described the data. The typical values for clearance, central volume of distribution, intercompartmental clearance, and peripheral volume of distribution were 13.1, 12.5, 23.9 L/hr/70 kg, and 16.3 L/70 kg, respectively. A loading dose of 40 mg/kg, followed by a continuous infusion of 60 mg/kg/d, was required to achieve 100% of the time the unbound concentration above the minimum inhibitory concentration (MIC) against Enterobacterales species and Pseudomonas aeruginosa (MIC ≤ 2 mg/L) without compromising safety.
Conclusions:
Standard intermittent dosing regimens (20-40 mg/kg every 8 hr over 0.5 hr) are likely to result in subtherapeutic concentrations, thereby risking therapy failure in critically ill children. A loading dose followed by continuous infusion is suggested for optimal target attainment.


Related Concept Videos
 01:15
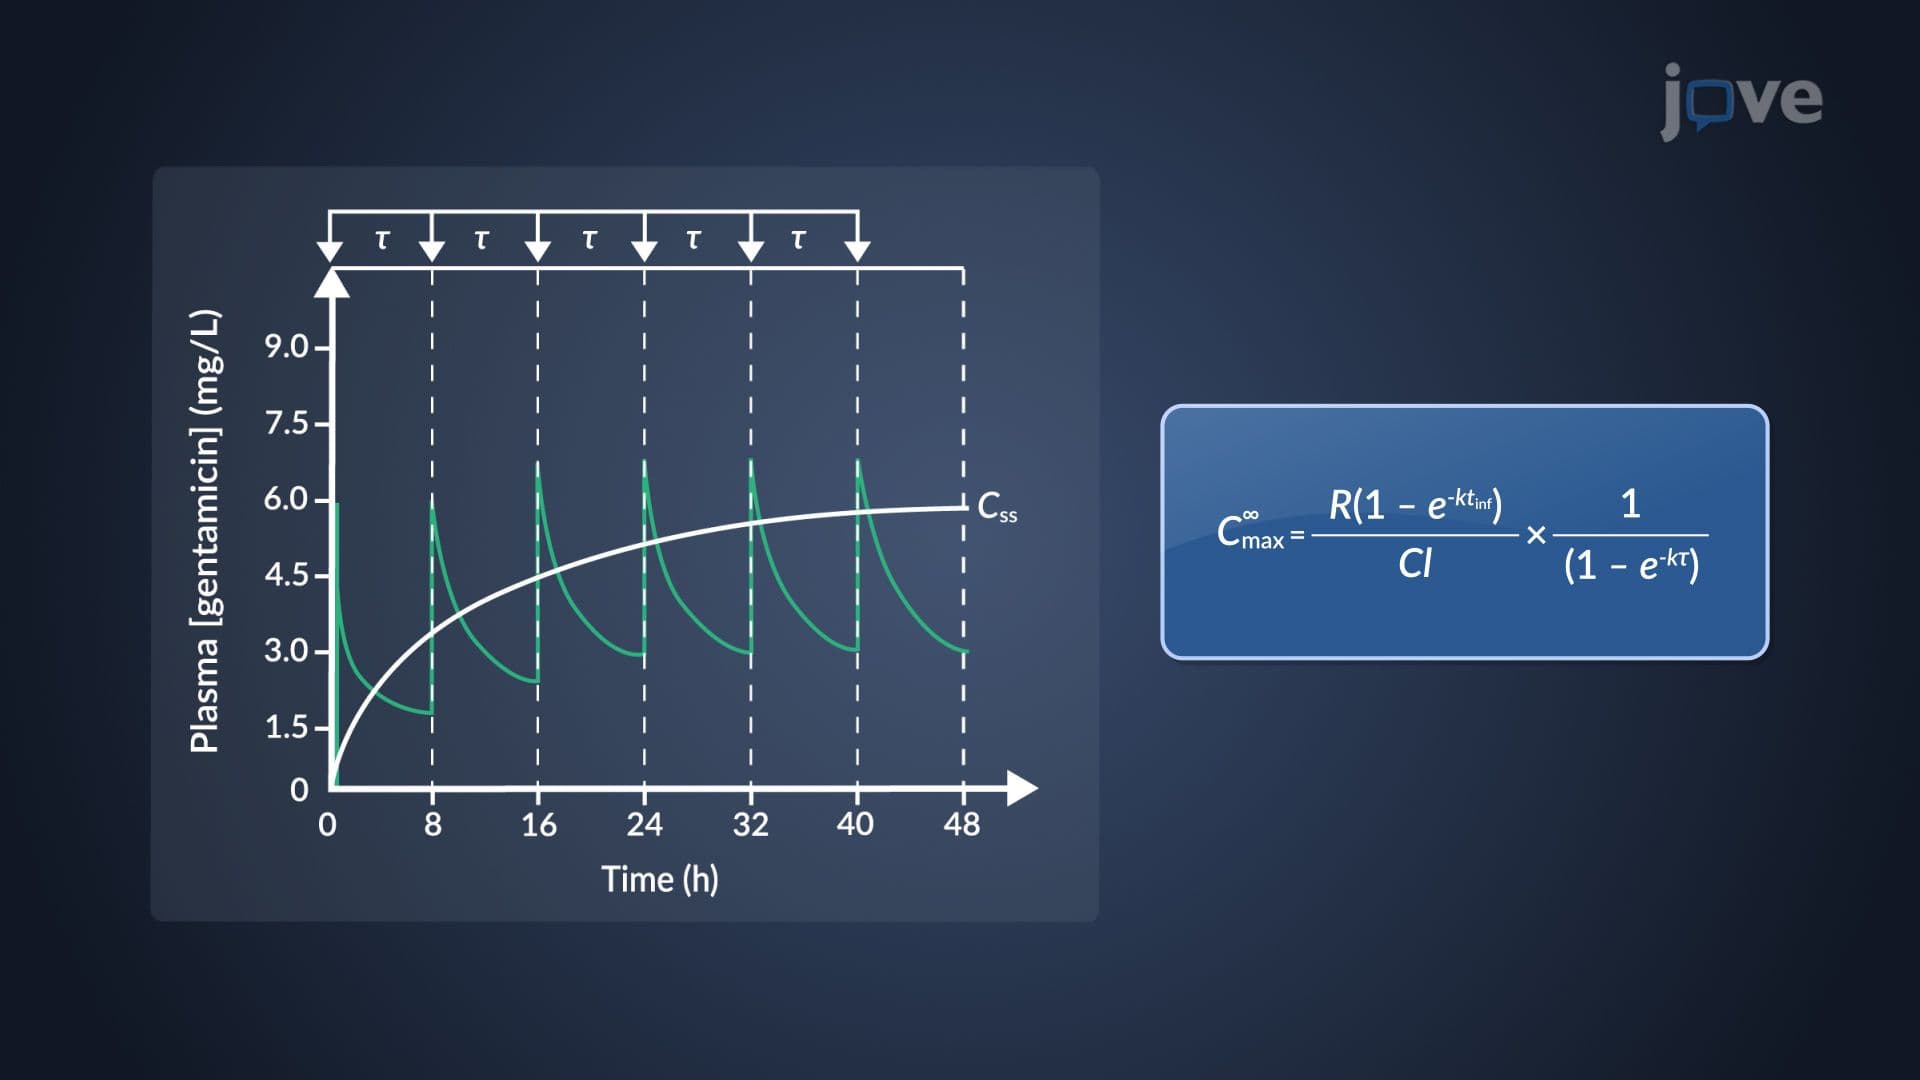
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:29
Drug Dosing: Infants and Children
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion