Related Experiment Video
Updated: Sep 25, 2026
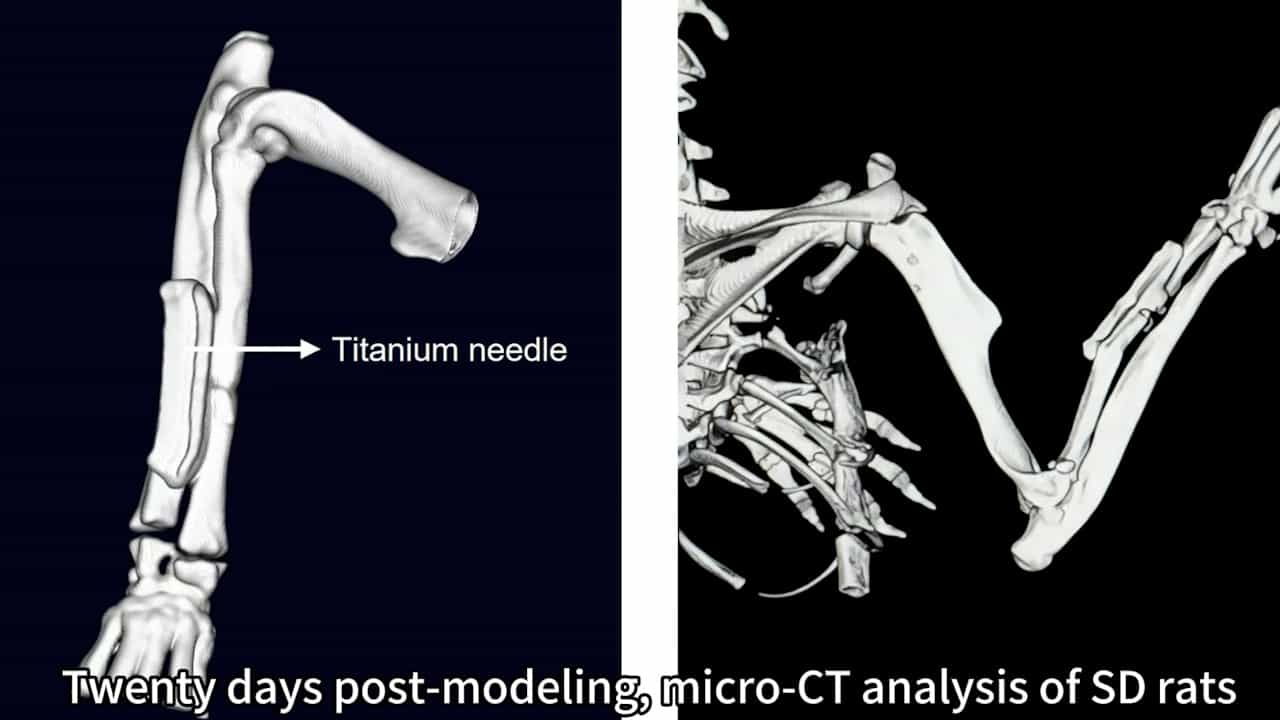

Development of a Novel Internal Fixation Model for Rat Radial Fractures: Fracture Healing Assessment and Dorsal Root Ganglion Isolation
Published on: March 13, 2026
Waiting time and mortality after hip fracture: findings from a large single-center cohort study
Mads Sundet1,2, Mette Martinsen3, Joseph Sexton4
1Department of Orthopedic Surgery, Diakonhjemmet Hospital, Box 23, Vinderen, Oslo, N-0319, Norway. mads.sundet@icloud.com.

Purpose:
Time to surgery after hip fracture is a potentially modifiable factor that may influence mortality, but the evidence for an association is conflicting for waiting time < 48 h. The aim of this study was to investigate the association between waiting time to surgery and mortality, with waiting time categorized into 12-hour intervals.
Methods:
We analysed all hip fractures operated at a large Norwegian hospital between 2015 and 2023. Waiting time from admission to surgery was categorized into 12-hour intervals. Mortality at one week, one month, three months (pre-specified primary endpoint) and one year was assessed using multivariable logistic regression, adjusting for age, sex, nursing home residency, Charlson Comorbidity Index (CCI), fracture type, calendar year of surgery, and direct-acting oral anticoagulant (DOAC) use. Model fit and discrimination were assessed for all models.
Results:
The study included 4136 hip fractures. At the pre-specified primary endpoint of three months, mortality was numerically higher in patients with waiting times > 12 h, but this did not reach statistical significance for any waiting-time category (adjusted odds ratio [AOR] 1.16-1.25, all p > 0.2). Among the secondary, exploratory endpoints, the one-year timepoint showed increased mortality with increased waiting: patients operated between 12 and 24 h had significantly higher one-year mortality (AOR 1.38, 95% CI 1.10-1.72), rising to an AOR of 1.80 (95% CI 1.20-2.71) for waiting times exceeding 48 h.
Conclusions:
In this cohort, waiting time beyond 12 h was associated with a higher one-year mortality, but the association was not statistically significant at the primary endpoint at three months. Given the observational design and the possibility of residual confounding, these findings should be interpreted with caution.
