Related Experiment Video
Updated: Sep 25, 2026
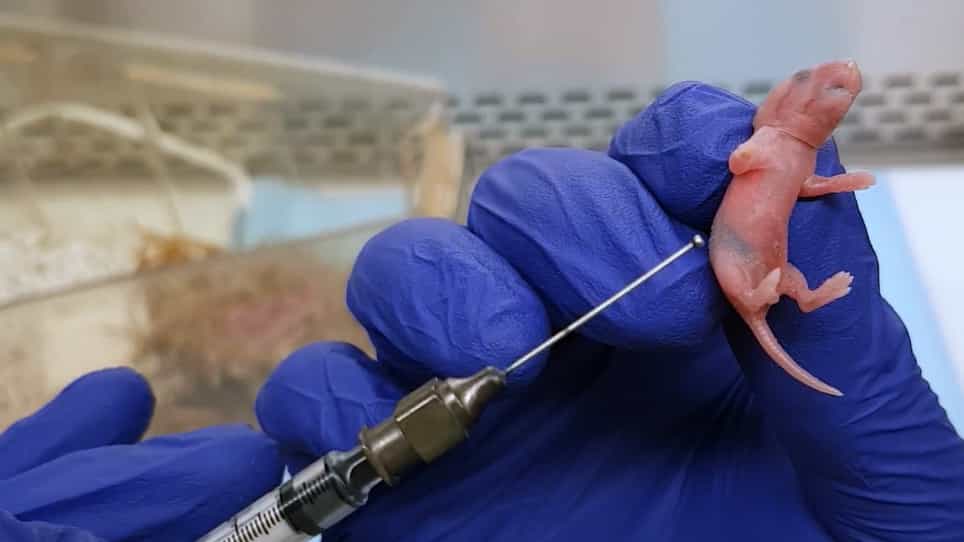

Probiotic Studies in Neonatal Mice Using Gavage
Published on: January 27, 2019
Probiotics and Risk of Death, Necrotizing Enterocolitis, and Sepsis in Very Preterm Infants
Ayoub Mitha1,2,3, Sofia Söderquist Kruth4,5, Emma Sinervo5,6
1Division of Clinical Epidemiology, Department of Medicine Solna, Karolinska Institutet, Stockholm, Sweden.

Importance:
Probiotics are reported to benefit preterm infants, but population-based clinical evidence is limited. In 2020, the Swedish Neonatal Society issued a national recommendation to supplement very preterm infants (28 weeks 0 days' to 31 weeks 6 days' gestation) with probiotics.
Objective:
To investigate whether probiotic supplementation was associated with risk of death, necrotizing enterocolitis (NEC), and/or culture-proven sepsis in infants born very preterm.
Design, Setting, And Participants:
This population-based cohort study examined data from the Swedish Neonatal Quality Register from January 1, 2017, through December 31, 2024. Live-born, very preterm infants, excluding those who died within the first 3 days of life or due to congenital or chromosomal abnormalities, were included.
Exposure:
Daily probiotic supplementation of 1 billion colony-forming units of freeze-dried Bifidobacterium infantis, Bifidobacterium lactis, and Streptococcus thermophilus initiated following birth and discontinued at postmenstrual week 34.
Main Outcomes And Measures:
Composites of death and/or NEC (Bell stage 2-3), death and/or surgical NEC (Bell stage 3), and death and/or culture-proven sepsis were assessed. Modified Poisson regression, propensity score-matched, and inverse probability of treatment weighting analyses were used for replication analyses. A multivariate bayesian modeling analysis accounting for the association between NEC and mortality was performed to estimate the association between probiotic exposure and mortality.
Results:
Among 4695 infants (mean [SD] gestational age, 30.2 [1.1] weeks; 2550 male [54.3%]), probiotic exposure increased from 0% before the national recommendation in 2020 to 16.9% in 2020 and a mean (SD) of 64.8% (4.7%) in 2021 to 2024. Probiotic supplementation vs no supplementation was associated with lower risk of death and/or NEC (rate, 0.8% vs 3.4%; adjusted relative risk [ARR], 0.28 [95% CI, 0.14-0.56]). When assessed separately, risks of death (rate, 0.3% vs 1.4%; ARR, 0.16 [95% CI, 0.06-0.45]) and NEC (rate, 0.6% vs 2.5%; ARR, 0.25 [95% CI, 0.10-0.61]) were both lower in the probiotic group. Multivariate bayesian modeling suggested that a substantial proportion of the observed mortality reduction was mediated via reduced NEC incidence (42.3% [credible interval, 16.1%-100%]). Probiotic supplementation was not associated with death and/or culture-proven sepsis (rate, 3.4% vs 4.4%; ARR, 0.86 [95% CI, 0.58-1.26]).
Conclusions And Relevance:
This cohort study of very preterm infants found that implementation of a multistrain probiotic was associated with a significant reduction in death and/or NEC, which may help inform shared decision-making between clinicians and families. These results should not be generalized to extremely preterm infants (<28 weeks' gestation).
More Related Videos
Related Concept Videos
 01:21
Microbiota Modulation by Antibiotics
 01:22
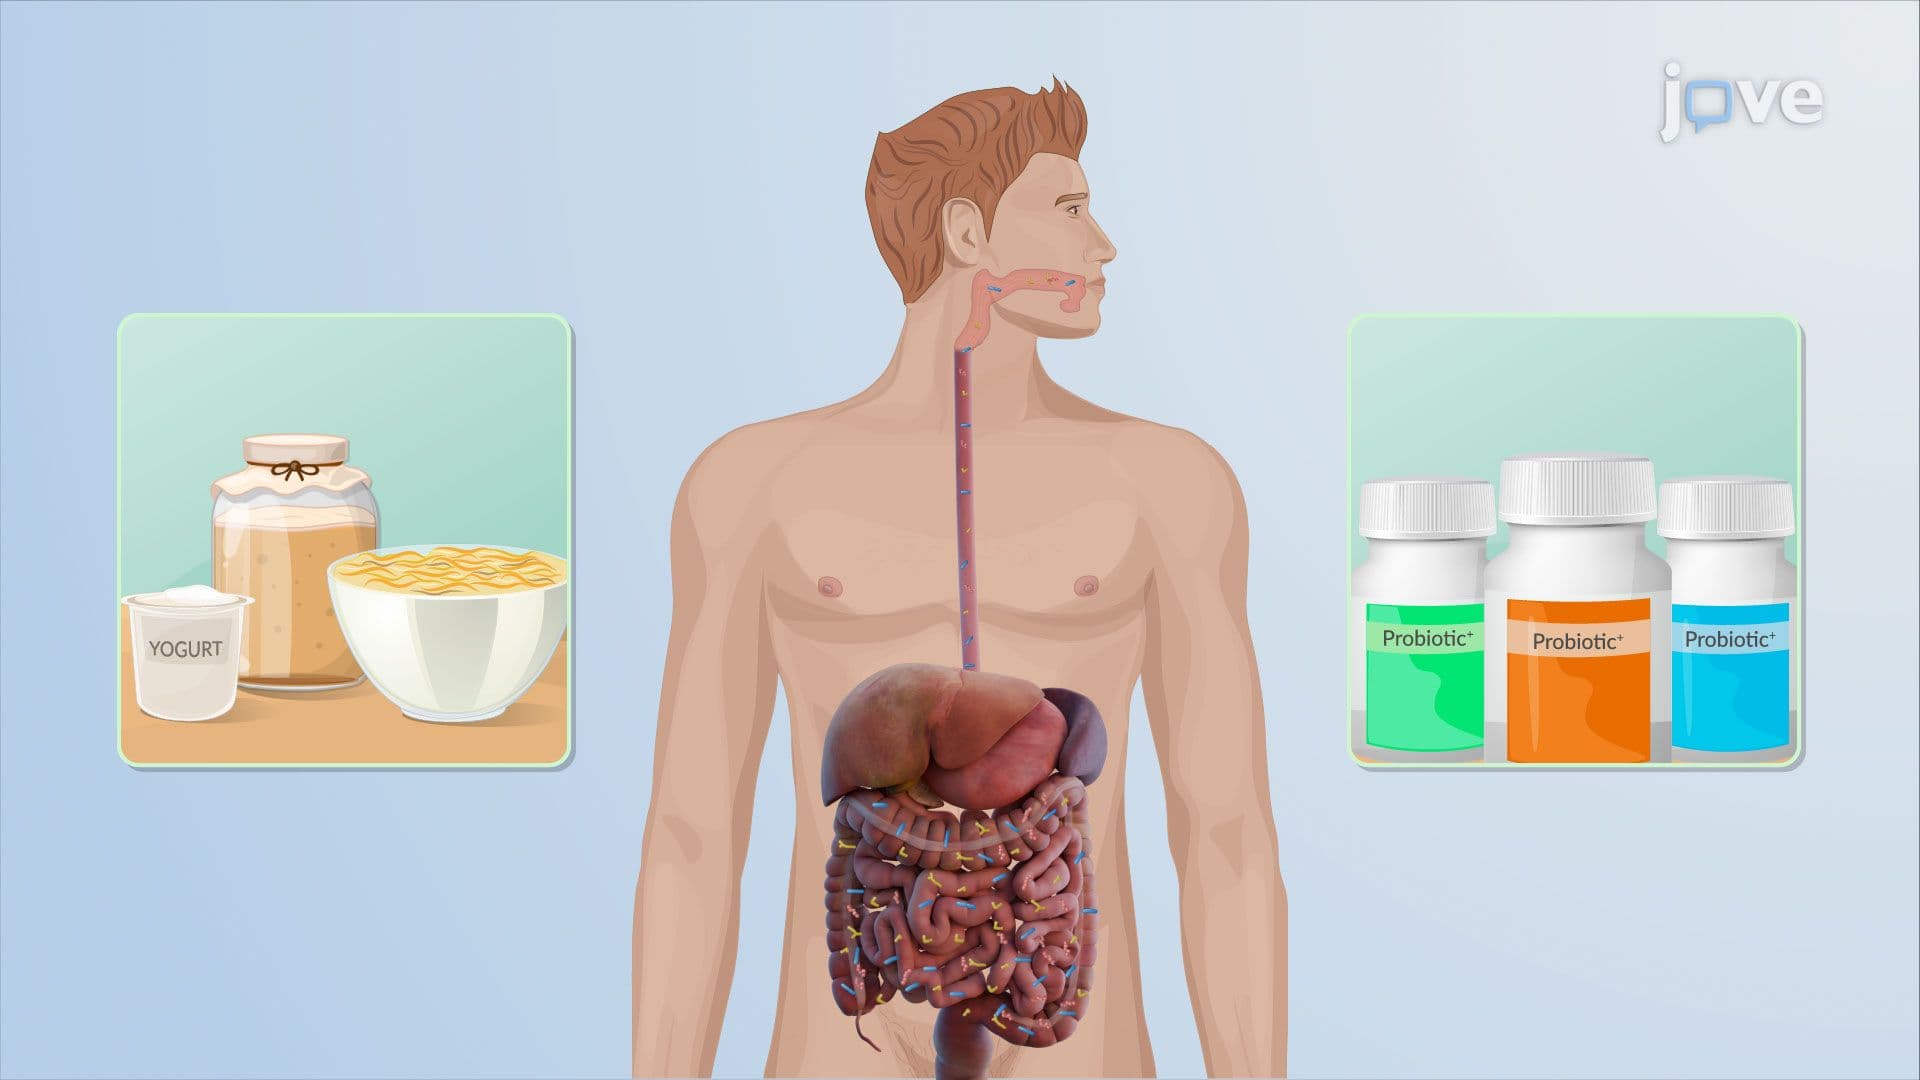
Probiotics
 01:30
Development of Human Microbiota
 01:28
Development of the Oral Microbiota
 01:53
Anatomy of the Intestines
 01:22
Introduction to the Human Microbiota