Related Experiment Video
Updated: Sep 25, 2026
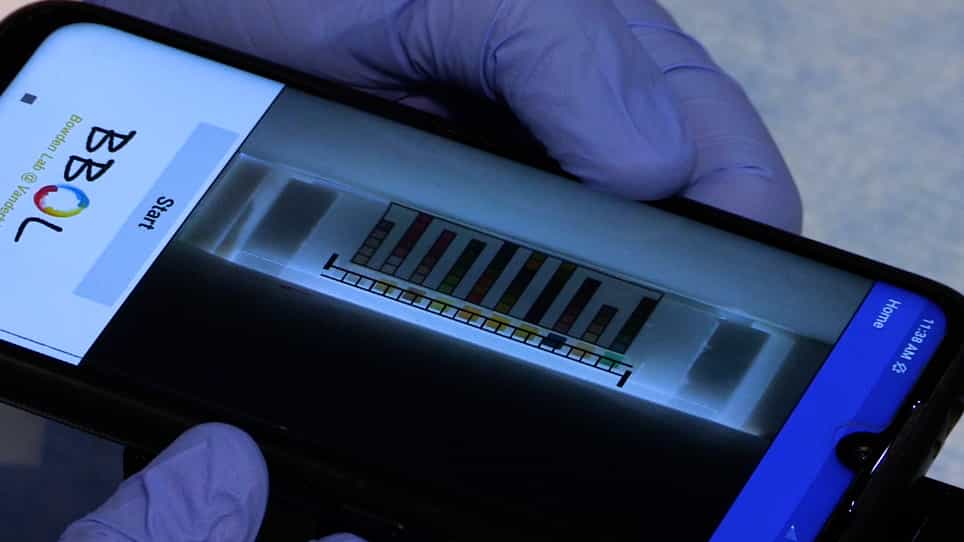

Low-Cost, Volume-Controlled Dipstick Urinalysis for Home-Testing
Published on: May 8, 2021
Pediatric urinalysis revisited: developmental physiology, preanalytical challenges, clinical decision limits, and
Karolina Samsel1, Olga Martyna Koper-Lenkiewicz1,2, Joanna Matowicka-Karna1,2
1Department of Clinical Laboratory Diagnostics, Clinical Hospital of the Medical University of Bialystok, Bialystok, Poland.

Abstract:
Urinalysis comprises test strip examination of physicochemical parameters together with microscopic or automated analysis of formed urine elements. The test strip covers pH, relative density (specific gravity, SG), protein, glucose, ketone bodies, urobilinogen, bilirubin, blood, and leukocyte esterase. In selected settings, it is supplemented by quantitative indices such as the urine protein-to-creatinine and albumin-to-creatinine ratios. This review evaluates age- and sex-specific reference intervals and clinical decision limits for urinalysis parameters in children, integrating developmental renal physiology with preanalytical and analytical determinants of test performance. A search of PubMed identified 148 publications published between 1982 and 2026. Pediatric urine composition is shaped by immature glomerular and tubular function, changing muscle mass, hormonal changes during puberty, and anatomical differences between sexes. Preanalytical variables, particularly the collection technique, materially affect reliability contamination rates range from approximately 1% for suprapubic aspiration to 26-80% for adhesive bag specimens. Automated systems improve reproducibility and require smaller specimen volumes, but pediatric validation data remain limited, and reference limits are not transferable between analyzer generations. Critically, values reported in the literature comprise both reference limits derived from healthy populations and clinical decision limits selected for diagnostic use; these are not interchangeable, and several widely cited pediatric values originate from screen-positive or hospitalized cohorts. Laboratories serving pediatric populations should report reference intervals together with the method, analyzer generation, and source population; define diagnostic decision limits locally rather than adopting adult-derived defaults; and confirm any positive bag-collected specimen by a less contamination-prone method. No reference intervals for formed elements have been published for preterm neonates, which remains the most urgent gap.

Related Concept Videos
 01:29
Urine Studies I: Urinalysis
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism
 01:18
Pharmacokinetics in Geriatric Patients: Effect of Age on Drug Excretion
 01:29
Drug Dosing: Infants and Children
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption