A new computational phenotyping framework for the clinical characterization of pediatric celiac disease
Related Experiment Video
Updated: Sep 25, 2026
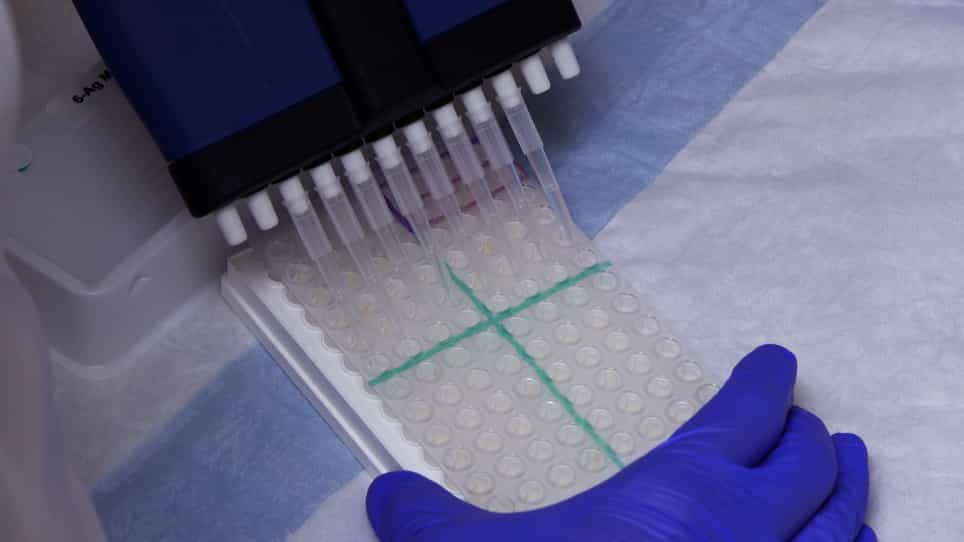
A High-Throughput Multiplexed Screening for Type 1 Diabetes, Celiac Diseases, and COVID-19
Published on: July 5, 2022
Giuseppe Albi1, Valentina Brembilla2, Erika Lenzi3
1Department of Electrical, Computer and Biomedical Engineering, University of Pavia, Italy.

Background And Objective:
Pediatric celiac disease (CD) is characterized by marked clinical and immunological heterogeneity that is not fully captured by the current symptom-based Oslo classification. Data-driven computational phenotyping may enable the identification of more homogeneous patient subgroups by integrating multimodal clinical information. This study proposes a topological data analysis (TDA)-based computational framework (pheTDA) to identify and characterize novel sub-phenotypes of pediatric CD from multicentric clinical data.
Methods:
A retrospective multicentric cohort of 2,922 pediatric CD patients described by 34 demographic, clinical, serological, genetic, and histological variables was analyzed. Mixed-type data were processed using Gower distance and mapped through a semi-supervised TDA Mapper pipeline, followed by Louvain community detection. The resulting communities were characterized through statistical testing and supervised machine learning. pheTDA was benchmarked against t-SNE followed by DBSCAN and agglomerative hierarchical clustering (AHC), and sensitivity analyses repeated pheTDA using clinical variables only and diagnostic-test variables only.
Results:
pheTDA identified seven relatively balanced sub-phenotypes with distinct combinations of symptoms, serological profiles, histological damage, growth delay, and autoimmune comorbidities. Compared with pheTDA, DBSCAN generated a markedly imbalanced nine-cluster partition, whereas the four-cluster AHC solution was dominated by sex. pheTDA showed a clinically broader effect-size profile, with its leading discriminators spanning clinical, serological, genetic, and histological domains. Clinical-only pheTDA communities were strongly aligned with the symptom-based Oslo categories, whereas diagnostic-test-only communities were more fragmented and reflected specific test combinations. Random Forest classifiers achieved a higher mean AUC for pheTDA communities than for Oslo classes (0.94 vs. 0.88).
Conclusions:
Multimodal pheTDA provides an exploratory and reproducible framework for identifying clinically interpretable pediatric CD sub-phenotypes. Benchmarking and feature-domain sensitivity analyses support the value of integrating clinical and diagnostic information while emphasizing that the resulting communities are data-dependent computational representations rather than definitive disease classes.