Related Experiment Video
Updated: Sep 25, 2026


Minimally Invasive Thumb-sized Pterional Craniotomy for Surgical Clip Ligation of Unruptured Anterior Circulation Aneurysms
Published on: August 11, 2015
Maximal Safe Resection and Targeted Intracavitary Therapy in Cladophialophora bantiana Brain Abscess: Illustration
Mazen Taman1, Abigail A Teshome1, Carl Porto1
1Department of Neurosurgery, Warren Alpert Medical School of Brown University and Brown University Health, Providence, RI.

Introduction:
Cladophialophora bantiana (C. bantiana) brain abscess is a rare dematiaceous mold infection often refractory to conventional treatment. Aspiration is commonly used for diagnosis and decompression, while resection may provide greater source control when anatomically feasible; however, comparative evidence remains limited and confounded.
Methods:
We report an illustrative surgically managed case and performed a PRISMA-guided systematic review with patient-level analysis to characterize management strategies and outcomes.
Results:
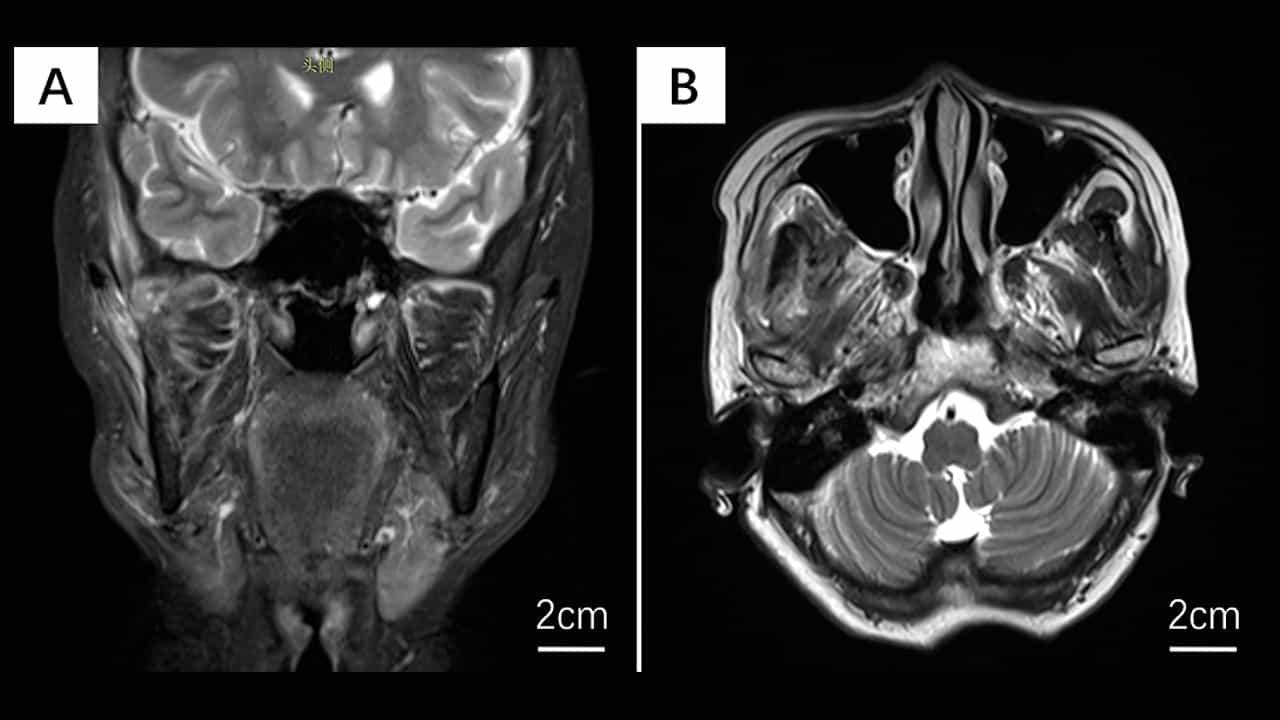
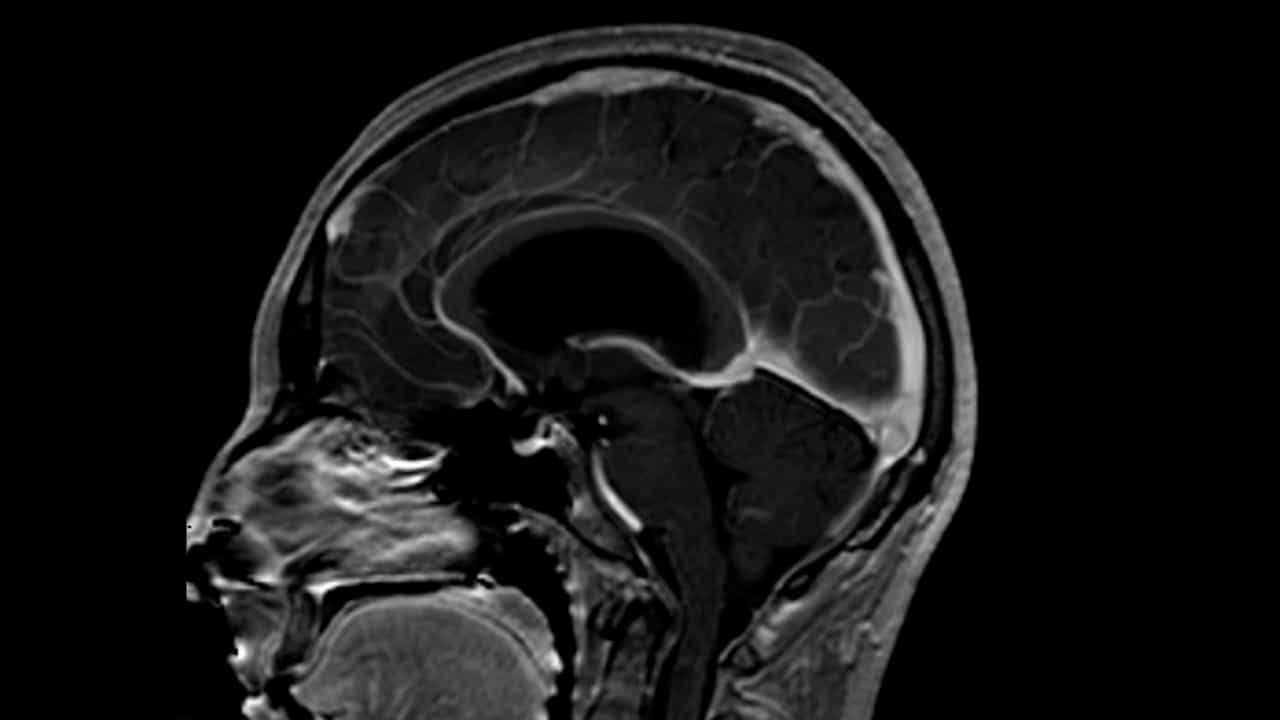
A 60-year-old immunocompromised male with symptomatic C. bantiana brain abscess underwent repeated resections, Ommaya-enabled intracavitary amphotericin B, systemic antifungals, and fosmanogepix, returning to neurologic baseline through two-year follow-up. Among 103 cases, 42 patients survived at last reported follow-up. Five patients had no abscess-directed operation, none of whom survived; 29 underwent aspiration-only, of whom 10 survived; and 69 underwent resection, of whom 32 survived. Among abscess-resected patients, 11/31 with unspecified extent of resection, 7/18 with subtotal resection, and 14/20 with gross total resection survived. Fourteen patients underwent ≥2 resections, of whom 9 survived; 3 underwent ≥3 resections, all of whom survived. Eight patients received an Ommaya reservoir; of whom 3 survived; all 3 survivors had also undergone gross total resection.
Conclusions:
These findings support source-control centered multidisciplinary management of C. bantiana brain abscess, with highest survival observed in selected patients who underwent reported GTR. Repeat resection and Ommaya-enabled intracavitary amphotericin B may be considered in selected complex cases. Standardized reporting of operative extent, reoperation timing, and antifungal protocols will help refine care.