Related Experiment Video
Updated: Sep 25, 2026
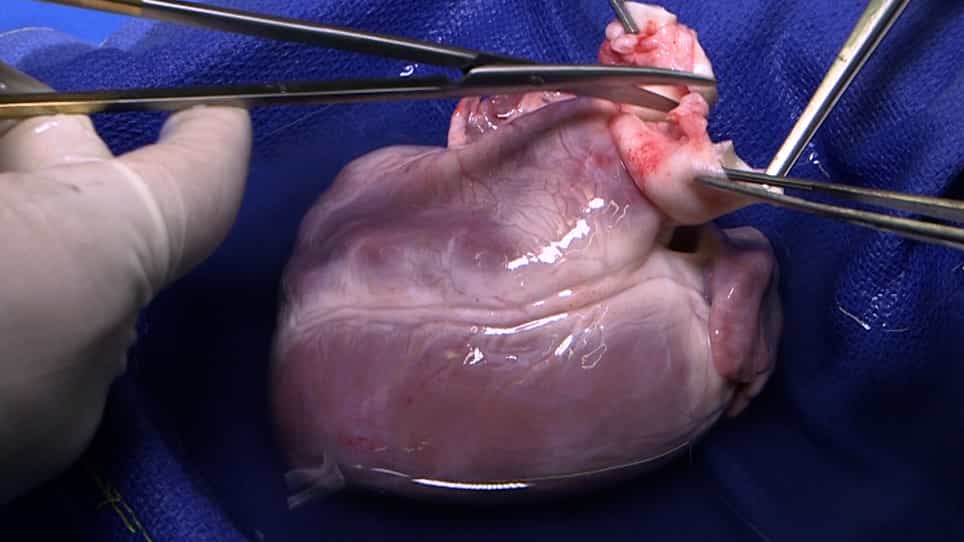

Functional Assessment of the Donor Heart During Ex Situ Perfusion: Insights from Pressure-Volume Loops and Surface Echocardiography
Published on: October 11, 2022
Intraoperative Right Ventricular Systolic Function in Liver Transplantation Recipients: A Prospective Observational
Shahbaz Hussain1, Yasir Bashir Butt1, Salman Shahzad1
1Department of Anesthesia, Pakistan Kidney and Liver Institute and Research Centre, Lahore, Pakistan.

Objectives:
This study evaluated dynamic changes in right ventricular (RV) systolic function using transesophageal echocardiography (TEE) during living-donor liver transplantation (LDLT).
Design:
Physiological echocardiographic observational study.
Setting:
Single tertiary transplant center.
Participants:
Fifty adult patients undergoing LDLT surgery between April 29 and November 14, 2025, were analyzed prospectively.
Interventions:
Intraoperative TEE was performed at 5 predefined surgical phases to assess RV systolic function using tricuspid annular plane systolic excursion (TAPSE), RV fractional area change (RVFAC), and tissue Doppler-derived systolic (S') velocity. Left ventricular ejection fraction and standard hemodynamic variables were recorded concurrently. The primary outcome was time-dependent change in RV systolic indices.
Measurements And Main Results:
The median Model for End-Stage Liver Disease score was 16 (interquartile range, 9), and 38 patients (76%) were men. RV systolic indices demonstrated significant time-dependent variation. TAPSE decreased from 2.15 ± 0.31 cm at baseline to 1.79 ± 0.45 cm during inferior vena cava clamping, with partial recovery to 2.08 ± 0.30 cm by the end of surgery (p < 0.001). Tissue Doppler S' velocity showed a similar pattern (10.58 ± 2.87 to 9.60 ± 2.89 to 11.72 ± 2.56 cm/s, p < 0.001). RVFAC remained relatively preserved but varied significantly across time points (p = 0.014). Left ventricular ejection fraction remained stable (p = 0.224). Hemodynamic changes paralleled RV alterations and responded to vasoactive support.
Conclusions:
Transient reductions in RV systolic indices occurred predominantly during inferior vena cava clamping and improved following reperfusion. Intraoperative TEE allowed serial assessment of these phase-specific RV changes during LDLT.
