Related Experiment Video
Updated: Sep 25, 2026
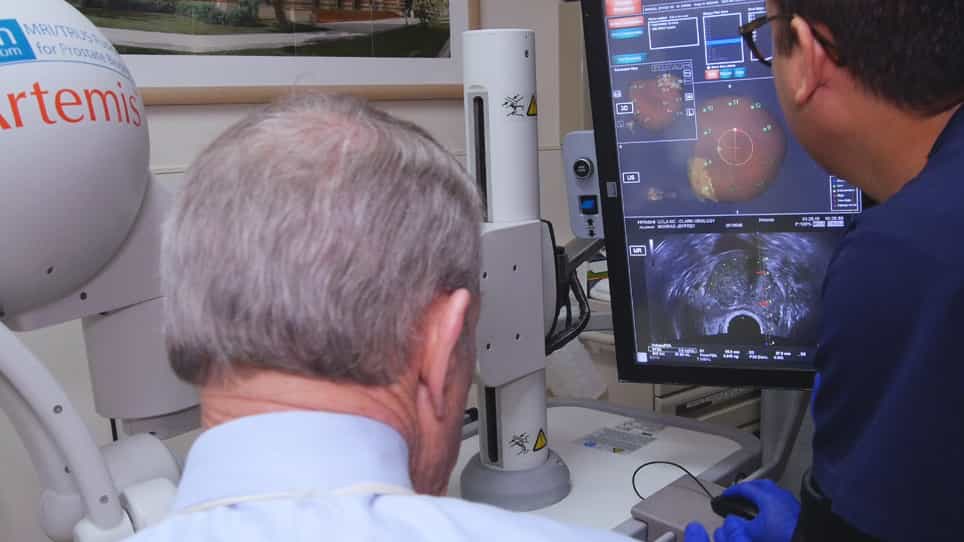

Use of MRI-ultrasound Fusion to Achieve Targeted Prostate Biopsy
Published on: April 9, 2019
Systematic versus perilesional sampling in transperineal MRI-fusion biopsy: is perilesional sampling ready for prime
Agneta Seebold1,2, Thomas Büttner3, Jörg Ellinger3,4
1Department of Urology and Pediatric Urology, University of Bonn, University Hospital Bonn, Bonn, Germany. Agneta.Seebold@ukbonn.de.

Background:
Multiparametric MRI has improved prostate cancer (PCa) diagnostics. The current standard combines MRI-targeted fusion biopsy (TB) with 12-core systematic biopsy (SB); current guidelines allow replacing SB with perilesional sampling (PB) penumbra to maintain diagnostic performance while reducing biopsy burden.
Methods:
We retrospectively analyzed 314 biopsy-naive men with Prostate Imaging Reporting and Data System (PI-RADS) 3-5 lesions who underwent transperineal MRI-fusion biopsy (TB plus 12-core systematic biopsy) under local anesthesia. A simulated PB strategy was evaluated post hoc by selecting four of the twelve systematic cores located in the directly adjacent sectors to the MRI-visible lesion on the standardized PI-RADS sector map and compared with SB. The primary objective was to assess whether PB replicates the diagnostic performance of SB for detecting clinically significant PCa (csPCa; ISUP grade group ≥ 2). We also compared biopsy and prostatectomy ISUP-grading, NCCN (National Comprehensive Cancer Network) -classification and the Briganti nomogram-based lymph-node metstasis risk. Statistical analyses used R and SPSS, with chi-square or Fisher's exact tests for categorial and t-tests for continuous variables; two-sided p < 0.05 was considered significant.
Results:
PCa was detected in 79.9% (251/314) of men, including 68.8% (216/314) with csPCa. TB alone detected 94.4% of csPCa, while SB detected 73.1%. The simulated TB + PB approach achieved 98.0% overall PCa detection and 99.1% csPCa detection (p = 0.48 vs. TB + SB). Concerning the impact on NCCN risk assessment, ISUP grade distribution was comparable across TB-based strategies, whereas SB alone detected fewer cancers and showed a trend towards lower ISUP grades. In the prostatectomy subgroup, ISUP grade concordance did not differ significantly between TB + SB and TB + PB (both 62.0%; p = 1.0). Mean Briganti scores did not differ significantly between TB + SB and TB + PB, with a minimal absolute difference of 0.17%. A 75% reduction of biopsy cores would be reached by a replacement of SB with PB. There was no significant loss of detection for csPCa (ISUP grade group 2-5; 99.1%) and no association with a loss of diagnostic yield for all ISUP grade groups. 11% reduction in detected cases was confined to ISUP grade group 1 (Supplementary Table S2).
Conclusions:
A TB plus 4-core PB may serve as an efficient alternative to conventional 12-core SB, without a significant reduction in diagnostic accuracy or a change in pretreatment risk assessment while markedly reducing procedural burden and resource use.

