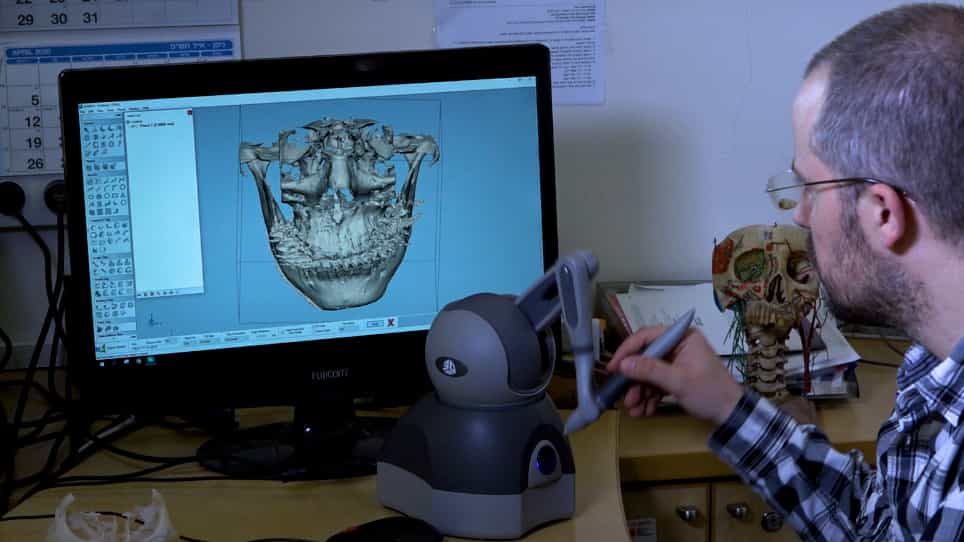
Related Experiment Video
Updated: Sep 26, 2026


Three-Dimensional Preoperative Virtual Planning in Derotational Proximal Femoral Osteotomy
Published on: February 17, 2023
Corrective osteotomies of malunited proximal humerus fractures with 3D patient-specific guides: a feasibility study
Stijn R J Mennes1,2,3, Anne M L Meesters4,5, Michel P J van den Bekerom2,3
1Department of Orthopaedic & Trauma Surgery, Flinders Medical Centre and Flinders University, Adelaide, Australia.

Background:
Corrective osteotomies for malunions after proximal humerus fractures are reserved for selected cases. These procedures are technically demanding, and surgical planning based on two-dimensional imaging, with free-hand operative correction, may lead to surgical inaccuracy. Three-dimensional (3D) pre-operative planning combined with patient-specific surgical guides and surgical simulation can overcome this issue. This study introduces 3D patient-specific guides for corrective osteotomies in proximal humeral malunions and determines the accuracy of achieved correction in human cadaveric shoulders with 2 innovative surgical techniques.
Methods:
Seven reversed corrective osteotomies were planned and performed on 4 Thiel-embalmed human specimens using 7 different respective 3D patient-specific cutting and reduction guides. Computed tomography scans were used to create 3D segmentations of all specimens. Subsequently, virtual surgical plans of osteotomies were created, and 3D-printed patient-specific cutting and reposition guides were designed and produced. Three humeri underwent an "extracapsular" corrective osteotomy, and 4 humeri underwent correction using a novel "humeral head-tuberosity separation" technique. Accuracy was assessed for valgus angulation and rotation by comparing pre-operative planning with post-operative results quantified with computed tomography scans.
Results:
The overall median difference between pre-operative planning and post-operative results was 5.2° (min-max: 2.9°-8.5°) for rotation and 3.4° (min-max: 2.4°-5.8°) for valgus angulation. For the "extracapsular" method, the median difference was 5.2° (min-max: 2.9°-7.0°) for rotation and 3.9° (min-max: 3.2°-5.8°) for valgus angulation. The median differences in rotation and valgus angulation for the "humeral head-tuberosity separation" corrections were 6.3° (min-max: 3.6°-8.5°) and 3.1° (min-max: 2.4°-3.6°), respectively.
Conclusion:
The application of 3D surgical planning and patient-specific guides is feasible for corrective osteotomies of malunited proximal humerus and resulted in reconstructions with less than 10° deviation from pre-operative planning, demonstrating acceptable technical accuracy and supporting the potential of this approach for future clinical application. The extracapsular osteotomy technique may serve as a solution for malunions with an intact anatomic relationship between the humeral head and greater tuberosity, whereas the novel osteotomy may be a solution for severe malunions with disrupted anatomy between the humeral head, greater tuberosity, and surgical neck. Future studies need to evaluate the use of the proposed techniques in patients with actual proximal humeral malunions.