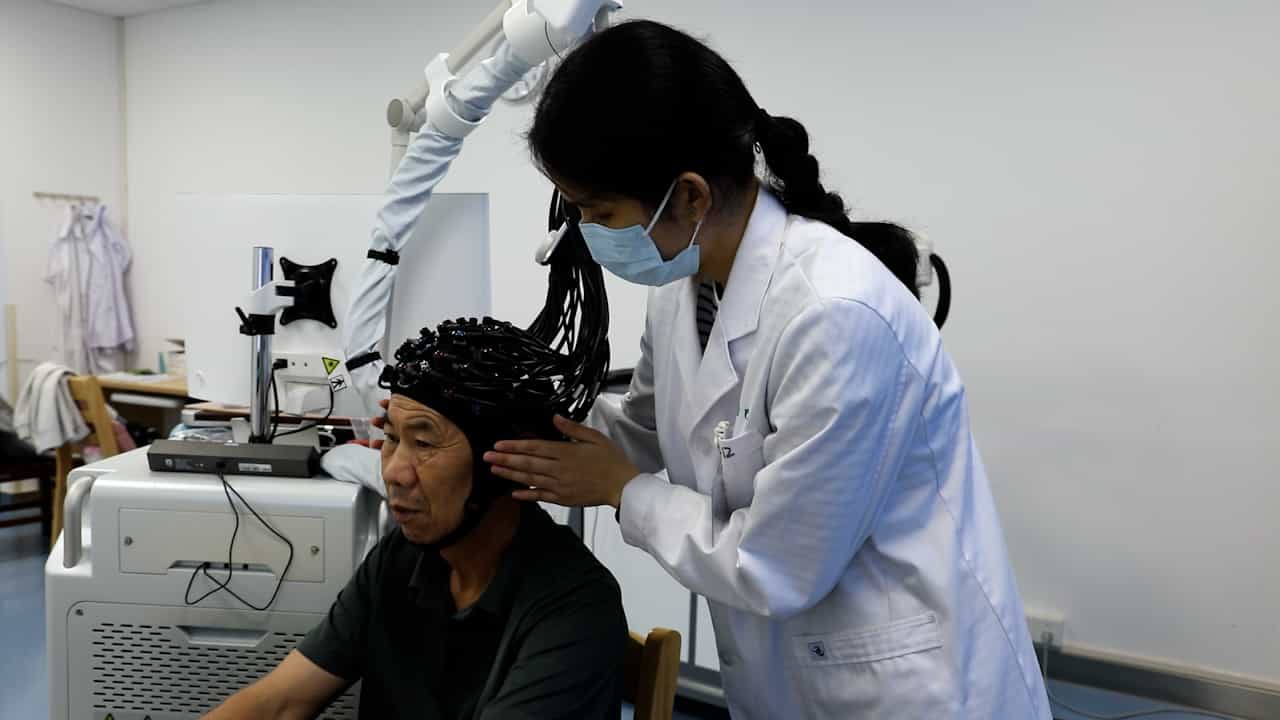
Related Experiment Video
Updated: Sep 26, 2026


Application of a Dual Upper Limb Task-Oriented Robotic System for the Functional Recovery of the Upper Limb in Stroke Patients
Published on: October 11, 2024
Completion rate and safety of non-invasive brain stimulation for upper limb dysfunction after stroke: a systematic
Juan Sun1, ZiLe Wang1, Yiming Huang1
1Xinxiang Medical University, Xinxiang, China.

Abstract:
Non-invasive brain stimulation (NIBS), including repetitive transcranial magnetic stimulation (rTMS) and transcranial direct current stimulation (tDCS), has been widely used as an adjunctive intervention for upper limb motor recovery after stroke; however, the treatment completion rates and comparative safety profiles across different NIBS modalities have not been systematically evaluated. This systematic review and network meta-analysis aimed to assess and compare the treatment completion rates of various NIBS interventions for post-stroke upper limb rehabilitation. We systematically searched six databases and trial registries (PubMed, Embase, Cochrane CENTRAL, CINAHL, WHO ICTRP, and ClinicalTrials.gov) for randomized controlled trials (RCTs) published up to January 20, 2025, with an updated search conducted to April 15, 2026. Random-effects single-arm meta-analyses using the Freeman-Tukey double arcsine transformation were performed to pool completion rates, and a Bayesian random-effects network meta-analysis estimated relative risks (RRs) with 95% credible intervals (CrIs); treatments were ranked using surface under the cumulative ranking curve (SUCRA) values. Risk of bias was assessed using the Cochrane Risk of Bias 2 tool. The protocol was registered with PROSPERO (CRD420261309536). Fifty-five RCTs comprising 68 comparisons and 2,640 participants were included. The pooled intervention group completion rate was 94.9% (95% CI: 93.3-96.4%; I2 = 46.8%). The network meta-analysis showed no statistically significant differences in completion rate between any NIBS intervention and sham/control (all 95% CrIs included 1.00). SUCRA rankings indicated that intermittent theta burst stimulation (iTBS; 71.1%), bilateral rTMS (BL-rTMS; 60.9%), and dual transcranial direct current stimulation (Dual-tDCS; 58.1%) ranked highest. The overall adverse event (AE) rate was 16.4% (95% CI: 8.5-26.2%) in intervention groups, predominantly mild headache and skin tingling, with an AE-related dropout rate of only 1.1%. Subgroup analyses showed higher completion rates for tDCS (96.8%) than rTMS (93.9%), with the chronic phase highest (97.1%) and the mixed phase lowest (89.1%). The LFK index was 0.04, indicating no publication bias. In conclusion, NIBS for post-stroke upper limb rehabilitation demonstrates favorable tolerability and safety, with an overall completion rate of approximately 95%. Exploratory SUCRA rankings placed iTBS, BL-rTMS, and Dual-tDCS in the top three positions; however, these rankings should be considered hypothesis-generating rather than definitive, as four interventions were informed by only a single study, absolute differences in completion rates were minimal, and all pairwise credible intervals included 1.00. These observed phase-specific differences suggest that stroke phase may be an important factor to consider when designing adherence strategies, although prospective evaluation of tailored interventions is needed.
Systematic Review Registration:
https://www.crd.york.ac.uk/prospero/display_record.php?ID=CRD420261309536, PROSPERO (Registration ID: CRD420261309536).