Related Experiment Video
Updated: Sep 26, 2026

Robotic Enucleation of Esophageal Leiomyoma
Published on: February 20, 2026
Case Report: Pulmonary benign metastasizing leiomyoma with mild 18F-FDG uptake occurring 30 years after hysterectomy
Huifeng Zou1,2, Shengjie Chen1,2
1Department of Thoracic Surgery, The Affiliated Hospital of Jiangsu University, Zhenjiang, Jiangsu, China.

Background:
Benign metastasizing leiomyoma (BML) is a rare smooth-muscle tumor that occurs in patients with a history of uterine leiomyoma, with the lungs being the most commonly involved extrauterine site. Pulmonary BML can mimic metastatic malignancy on imaging. Decades-long intervals after uterine surgery have been reported, and 18F-FDG uptake may vary among lesions.
Case Presentation:
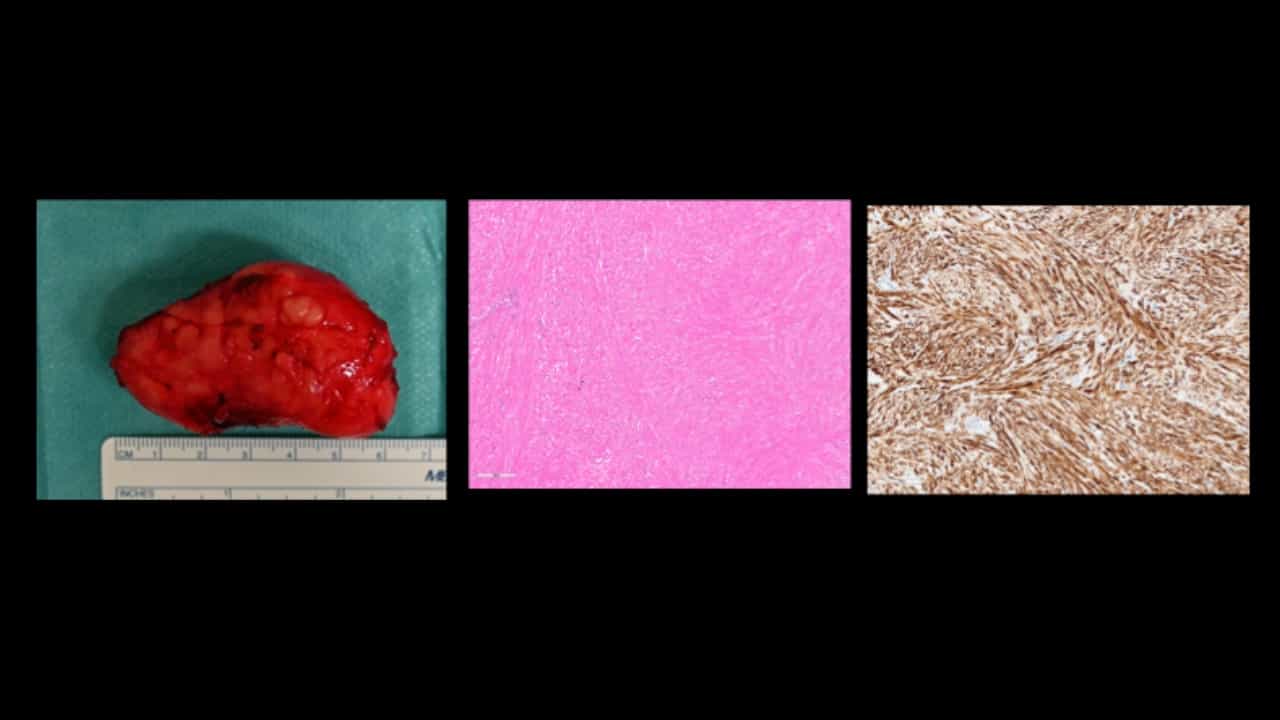
A 59-year-old postmenopausal, nonsmoking woman presented with multiple bilateral pulmonary nodules 30 years after hysterectomy for uterine leiomyoma. 18F-FDG PET/CT demonstrated mild FDG uptake in the dominant pulmonary lesion, with a maximum standardized uptake value (SUVmax) of 2.44. Although the uptake was not strongly suggestive of an aggressive malignancy, a low-grade neoplasm could not be excluded. Video-assisted thoracoscopic wedge resection was therefore performed. Histological examination revealed bland spindle-cell proliferation arranged in fascicles, with mitotic activity of < 1 per 10 high-power fields and a Ki-67 labeling index of approximately 2%. The spindle cells expressed desmin, vimentin, and estrogen receptor, whereas focal TTF-1 staining was restricted to entrapped bronchial epithelial cells. In conjunction with the bilateral multifocal pulmonary distribution and remote history of uterine leiomyoma, these findings supported a clinicopathological diagnosis of pulmonary BML. The patient recovered uneventfully without endocrine therapy. During postoperative telephone follow-up, she reported no new discomfort, and regular chest CT surveillance was recommended.
Conclusion:
Pulmonary BML should be considered in the differential diagnosis of multiple pulmonary nodules in women with a remote history of uterine leiomyoma. Mild FDG uptake cannot distinguish pulmonary BML from a low-grade malignancy. Integrated clinical, radiological, and pathological assessment is therefore required to establish the diagnosis and avoid unnecessary treatment.