Related Experiment Video
Updated: Sep 26, 2026
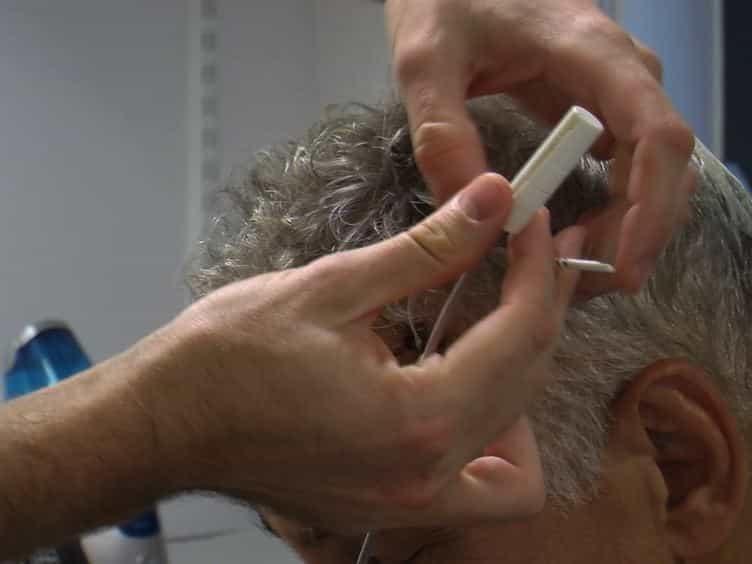

Controlling Parkinson's Disease With Adaptive Deep Brain Stimulation
Published on: July 16, 2014
Integrating Baduanjin exercise into Parkinson's rehabilitation: a randomized controlled trial
Muhammed Fatih Kavak1, Nur Betül Civelek2, Gülay Yalçın3
1Department of Physiotherapy and Rehabilitation, Faculty of Health Sciences, Üsküdar University, İstanbul, Türkiye.

Objective:
To evaluate whether adding Baduanjin exercise to conventional physiotherapy improves balance, functional mobility, walking capacity, and motor signs compared with conventional physiotherapy alone in nursing-home residents with Parkinson's disease.
Methods:
This assessor-blinded, two-group randomized controlled trial included 30 participants allocated equally to conventional physiotherapy (CPT) or Baduanjin plus conventional physiotherapy (BDJ + CPT). CPT consisted of supervised 45-min sessions three times weekly for 12 weeks; the intervention group received an additional 15 min of supervised Baduanjin during each session. Twenty-seven participants completed follow-up and were included in the complete-case analysis (BDJ + CPT, n = 13; CPT, n = 14). Balance, functional mobility, walking capacity, and motor signs were assessed using the Berg Balance Scale (BBS), Timed Up and Go test (TUG), Six-Minute Walk Test (6MWT), and Movement Disorder Society-sponsored Unified Parkinson's Disease Rating Scale Part III (MDS-UPDRS III), respectively. Because no single outcome had been designated a priori as primary, the four outcomes were analyzed in parallel using baseline-adjusted analysis of covariance (ANCOVA) with heteroskedasticity-consistent HC3 standard errors. Multiplicity was addressed using the Holm procedure.
Results:
At 12 weeks, BDJ + CPT was associated with a higher adjusted BBS score than CPT alone (adjusted mean difference, 9.93 points; 95% CI, 3.64 to 16.23; Holm-adjusted p = 0.006) and a greater 6MWT distance (38.76 m; 95% CI, 17.39 to 60.13; Holm-adjusted p = 0.002). The adjusted between-group difference in TUG favored BDJ + CPT but did not reach statistical significance (-4.73 s; 95% CI, -9.49 to 0.03; Holm-adjusted p = 0.103). No additional treatment effect was demonstrated for MDS-UPDRS III (1.78 points; 95% CI, -5.11 to 8.67; Holm-adjusted p = 0.613).
Conclusion:
In this small, single-site randomized trial, adding Baduanjin to conventional physiotherapy was associated with a higher BBS score and a longer 6MWT distance at 12 weeks after baseline adjustment. Additional benefits for TUG or MDS-UPDRS III were not demonstrated. Larger, prospectively powered trials are needed to determine the specific and clinically meaningful contribution of Baduanjin to Parkinson's rehabilitation.
Clinical Trial Registration:
ClinicalTrials.gov, identifier NCT07306169.


