Related Experiment Video
Updated: Sep 26, 2026
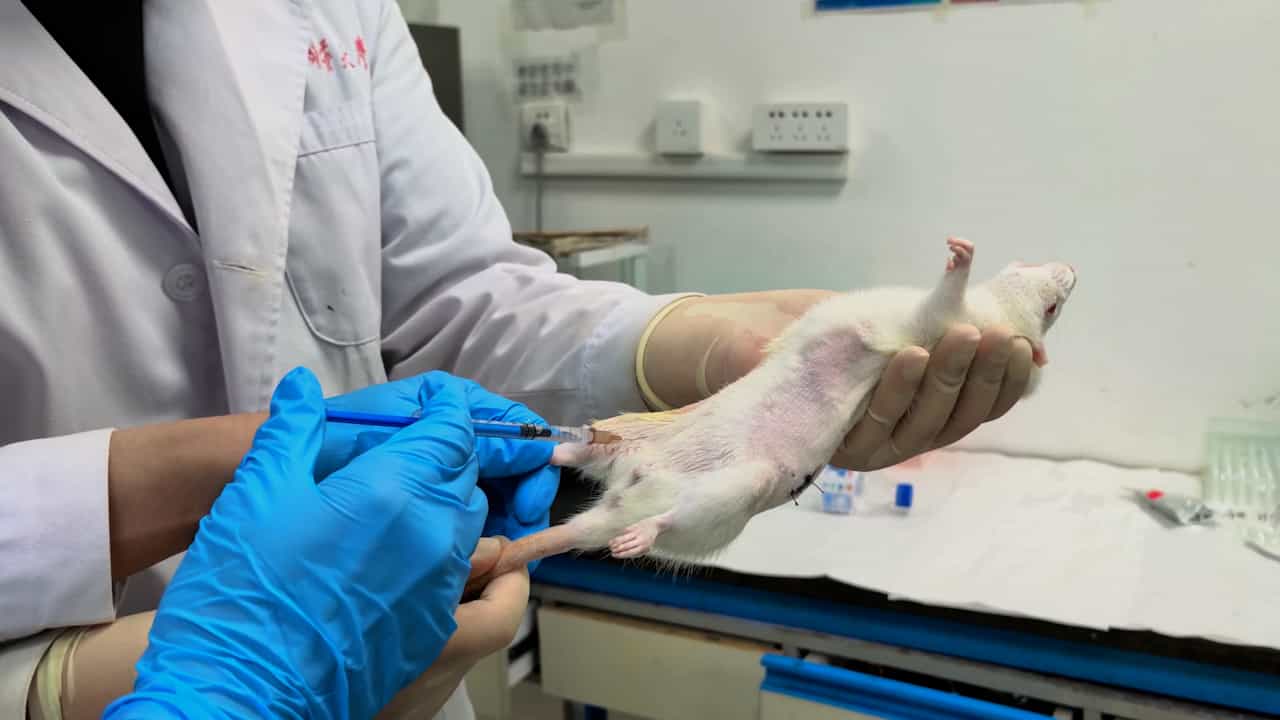

The Creation of a Rat Model for Osteosarcopenia via Ovariectomy
Published on: February 21, 2025
Sarcopenia Is Associated With Severe Treatment Toxicity and Mortality in Older Adults With Advanced Cancer: A
Lindsey J Mattick1, Mostafa Mohammed2, Chin-Shang Li1
1Division of Supportive Care in Cancer, Department of Surgery, School of Medicine and Dentistry, University of Rochester Medical Center, Rochester, New York, USA.

Background:
Sarcopenia, a loss of muscle strength, quantity and performance that occurs primarily from ageing or secondary to disease, is hypothesized to worsen treatment outcomes in patients with cancer. Most published studies, however, focus solely on muscle quantity in patients under 70. Here, we evaluate the association between sarcopenia, defined as both a loss of strength and muscle quantity, and treatment tolerability in older adults receiving cancer treatment.
Methods:
This secondary analysis examines data from a randomized clinical trial evaluating a geriatric assessment intervention (NCT02054741). Older adults (≥ 70 years) with advanced cancer starting a new treatment regimen were recruited from community oncology practices across the United States. We analysed data from 161 participants in the usual care arm with baseline standard of care computed tomography (CT) scans. Sarcopenia was defined by reduced strength (chair stand > 16.7 s for five rises) and either a reduction in muscle quantity (skeletal muscle index [SMI] < 41 cm2/m2 women, < 43 cm2/m2 men with BMI < 24.9 kg/m2 or < 53 cm2/m2 men with BMI ≥ 25 kg/m2) or muscle quality. Sarcopenia was considered severe when the above criteria were met along with impaired physical performance (TUG > 13.5 s). Treatment toxicity was assessed via Common Terminology Criteria for Adverse Events (CTCAE) v4.0.
Results:
Among 161 participants (mean age: 76.6 ± 4.7; 61% male, 94% non-Hispanic white), 57% (91/161) met criteria for sarcopenia, of which 59% (54/91) were considered severe. Sarcopenia was associated with deficits in multiple geriatric assessment domains (nutrition, activities of daily living, instrumental activities and cognition; p < 0.05). In multivariable logistic regression and Cox proportional hazards regression analyses, patients with sarcopenia were more likely to experience severe non-hematologic toxicities (Grades 3-5; OR = 2.24, 95% confidence interval [CI]: 1.12-4.47). In participants receiving first-line therapy, sarcopenia was associated with worse 1-year survival (46% survival [95% CI: 35%-55%]; HR = 2.12 [95% CI: 1.14-3.93]; 49 events) compared to those without sarcopenia (60% survival [95% CI: 48%-70%]; 28 events). SMI alone was not significantly associated with severe nonhematologic toxicity or survival.
Conclusion:
Sarcopenia is highly prevalent in older patients with cancer and is associated with severe toxicity and mortality. Our findings highlight the importance of assessing muscle strength, quantity, quality and performance when evaluating older adults with cancer.
Trial Registration:
CLINICALTRIALS.GOV NCT02054741.
