Related Experiment Video
Updated: Sep 26, 2026
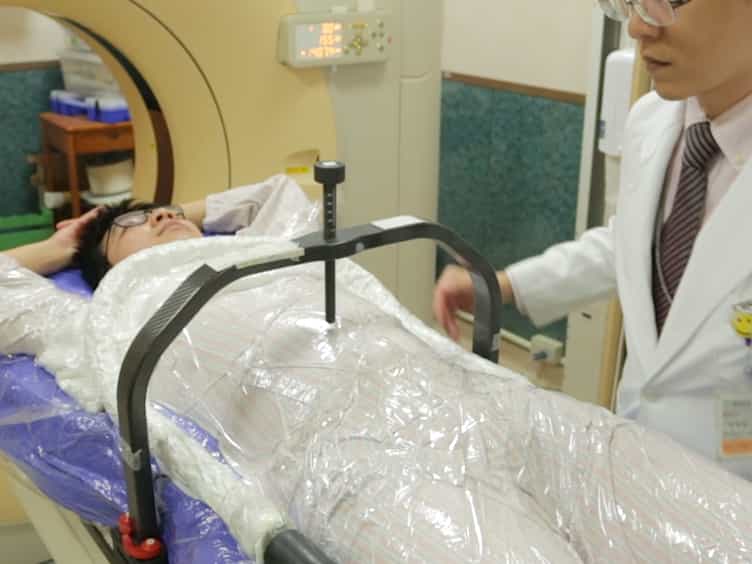

Treatment of Liver Metastases Using an Internal Target Volume Method for Stereotactic Body Radiotherapy
Published on: May 8, 2018
Additive local radical therapy in synchronous oligometastatic non-small cell lung cancer without oncogenic drivers: a
Maximilian Daniel Aßmann1, Marius Helmut Aust1, Dirk Rades2
1Medical Clinic III - Pulmonology, University Hospital Schleswig-Holstein (UKSH), Ratzeburger Allee 160, 23562, Luebeck, Schleswig-Holstein, Germany.

Introduction:
Synchronous oligometastatic disease (sOMD) in non-small cell lung cancer (NSCLC) is considered a potentially curable intermediate state between localized and widely metastatic disease. Whether adding local radical therapy (LCT after initial systemic therapy (S) or upfront) as surgery and/or radiotherapy to all visible sites improves outcomes in non-oncogene‑addicted sOMD remains uncertain.
Patients And Methods:
We conducted a retrospective, single‑center cohort study at a German university hospital. Patients diagnosed with histologically confirmed NSCLC (2018-2023) in stage T1-T3, N0-N2 and M1a, M1b or M1c with ≤3 metastases in ≤2 organs were eligible. Driver‑mutated tumors were excluded. Patients received S alone (control group) or S plus LCT to primary and all metastases (intervention group). Primary endpoints were a study-specific modified objective response rate (mORR), progression‑free survival (PFS) and overall survival (OS). Secondary endpoints were hospitalization‑requiring adverse events (CTCAE ≥3). Inverse‑probability‑of‑treatment weighting (IPTW) was used to adjust for baseline imbalances. Time‑to‑event outcomes were analyzed with weighted Cox models and Kaplan-Meier estimates; binary outcomes with logistic regression. Immortal time-bias was addressed using a time-dependent Cox model.
Results:
Among 47 eligible patients, 24 were in the control group and 23 in the intervention group. Baseline characteristics were largely balanced with exceptions for N stage and ECOG performance status, favoring the intervention group. Median PFS was 7.0 months in the control group and 7.4 months in the intervention group (hazard ratio (HR) 1.19); median OS was 19.3 vs 22.9 months (HR 0.65); neither difference was statistically significant. mORR did not differ significantly between groups. CTCAE ≥3 hospitalizations were fewer in the intervention than in the control group.
Conclusions:
Adding local radical therapy to systemic treatment yielded no statistically significant improvement in PFS or OS. Numerical trends favored the intervention for OS and severe hospitalizations were less frequent with the intervention. Whether treatment sequencing modifies the effect of local radical therapy warrants evaluation in sequence-stratified prospective trials.
