Related Experiment Video
Updated: Sep 26, 2026

3D Planning and Printing of Patient Specific Implants for Reconstruction of Bony Defects
Published on: August 4, 2020
An integrated digital-to-surgical framework for patient-specific chest wall resection and reconstruction using
Ira Goldsmith1,2, Thomas Bragg3, Aravindh Jayakumar4
1Department of Cardiothoracic Surgery, Morriston Hospital, Swansea, Wales, UK. Ira.goldsmith@swansea.ac.uk.

Abstract:
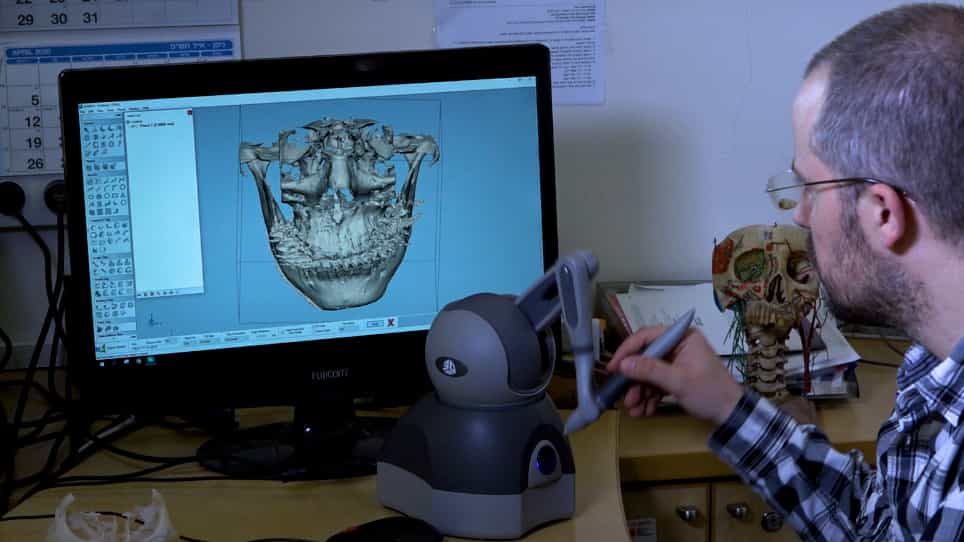
Patient-specific skeletal reconstruction of the chest wall following extensive resections that result in large, anatomically complex defects remains challenging using conventional reconstructive techniques. We describe an end-to-end digital-to-surgical workflow framework for patient-specific chest wall resection and reconstruction using three-dimensional (3D) printed titanium implants. The four-stage workflow integrates Computed Tomography (CT) imaging data, virtual 3D anatomical modelling, virtual tumour-margin planning, computer-aided implant design (CAD), stereolithographic prototype validation, and additive manufacturing using laser-powder bed fusion (L-PBF). High-resolution CT data in Digital Imaging and Communications in Medicine (DICOM) format were converted into patient-specific 3D-rendered models of the chest wall and tumour to enable virtual delineation of tumour extent and digitally planned resection margins. These digital resection models were then used to design anatomically matched patient-specific implants. Implant designs were validated using stereolithographic prototypes before definitive manufacture in titanium alloy. The workflow underwent clinical feasibility evaluation in six consecutive patients requiring major chest wall resection and reconstruction. Across all cases, digitally planned resections and reconstructions were performed without intraoperative modification. The implants demonstrated accurate anatomical fit, secure fixation, and satisfactory restoration of chest wall anatomy. During the available follow-up period ranging from 5 months to 5 years, no implant failures or implant-related complications were observed. Two patients who underwent reconstruction for palliation subsequently died from progression of their underlying disease. This proof-of-concept single-centre study demonstrates the clinical feasibility of a digital-to-surgical workflow and provides a foundation for future multicentre evaluation.