Related Experiment Video
Updated: Sep 26, 2026


Murine Appendectomy Model of Chronic Colitis Associated Colorectal Cancer by Precise Localization of Caecal Patch
Published on: August 24, 2019
Small-Bowel Perforation Caused by Multiple Metastases from Lung Adenocarcinoma Preceded by Obscure Gastrointestinal
Yusuke Hagiwara1, Junichi Ochi2, Saki Ohishi1
1Department of Surgery, Odate Municipal General Hospital, Odate, Akita, Japan.

Introduction:
Gastrointestinal metastasis from lung cancer is uncommon and rarely symptomatic, and small-bowel metastasis causing perforation is rare with a poor prognosis. Obscure gastrointestinal bleeding as the initial manifestation, preceding perforation, is seldom documented. We report such a case requiring emergency surgery.
Case Presentation:
A man in his 70s with a heavy smoking history was incidentally found, during an admission for bowel obstruction, to have left-lung lesions with hilar and subcarinal lymphadenopathy on CT, without abdominal disease. Bronchoscopic biopsy showed adenocarcinoma with a programmed death ligand 1 (PD-L1) tumor proportion score of 100% and no actionable driver alteration. Based on an ipsilateral separate-lobe pulmonary nodule, mediastinal nodal involvement, and a clinically suspected sacral bone metastasis, the disease was staged as cT4N2M1b, stage IVA. First-line pembrolizumab monotherapy was administered, and the thoracic disease remained controlled, with regression of the primary lesion and lymph nodes. After a cutaneous immune-related adverse event treated with corticosteroids (with pembrolizumab discontinuation), he developed melena and severe iron-deficiency anemia requiring transfusion. Esophagogastroduodenoscopy and colonoscopy identified no bleeding source, and obscure (suspected small-bowel) gastrointestinal bleeding was diagnosed. Approximately 2 months later, after an episode of shock, possibly related to infection and adrenal insufficiency following corticosteroid withdrawal, he developed acute abdominal pain with free intraperitoneal air. Emergency surgery revealed multiple small-bowel tumors with a perforation; partial small-bowel resection with functional end-to-end anastomosis and peritoneal lavage was performed. Histopathology showed multiple metastatic adenocarcinomas of the small intestine, a perforated metastatic ulcer, and mesenteric lymph node metastasis. Immunohistochemistry showed cytokeratin (CK) 7 positivity and CK20, caudal-type homeobox 2 (CDX2), thyroid transcription factor-1 (TTF-1), novel aspartic proteinase of the pepsin family A (Napsin A), CK5/6, and p40 negativity, matching the immunophenotype of the original lung biopsy. These findings were inconsistent with an intestinal primary and consistent with metastatic lung adenocarcinoma. Postoperative paralytic ileus resolved, and the patient was discharged on best supportive care.
Conclusions:
In patients with lung cancer, obscure gastrointestinal bleeding may herald small-bowel metastasis that can progress abruptly to perforation, even when the thoracic disease remains controlled after immune checkpoint inhibitor (ICI) therapy. Small-bowel metastasis should be considered when endoscopy is unrevealing, and new gastrointestinal symptoms should not be dismissed.
Related Concept Videos
 01:22
Esophageal Perforation-I: Introduction
The location of esophageal perforation can vary, occurring anywhere along the esophagus.
 01:28
Esophageal Perforation-II: Clinical Manifestations and Management
Clinical Manifestations:
 01:27
Inflammatory Bowel Disease I: Ulcerative Colitis
Inflammatory bowel disease, or IBD, encompasses a group of disorders characterized by chronic inflammation or ulceration of the gastrointestinal tract.
Risk Factors
The exact cause of IBD remains unclear, although it is believed to be due to a mix of genetic, environmental, microbial, and immune factors. Genetic factors are significant in determining susceptibility to IBD, with family history being a critical risk factor. Individuals with a first-degree relative who has IBD are at...
 01:07
Intestinal Obstruction II: Pathophysiology
 01:19
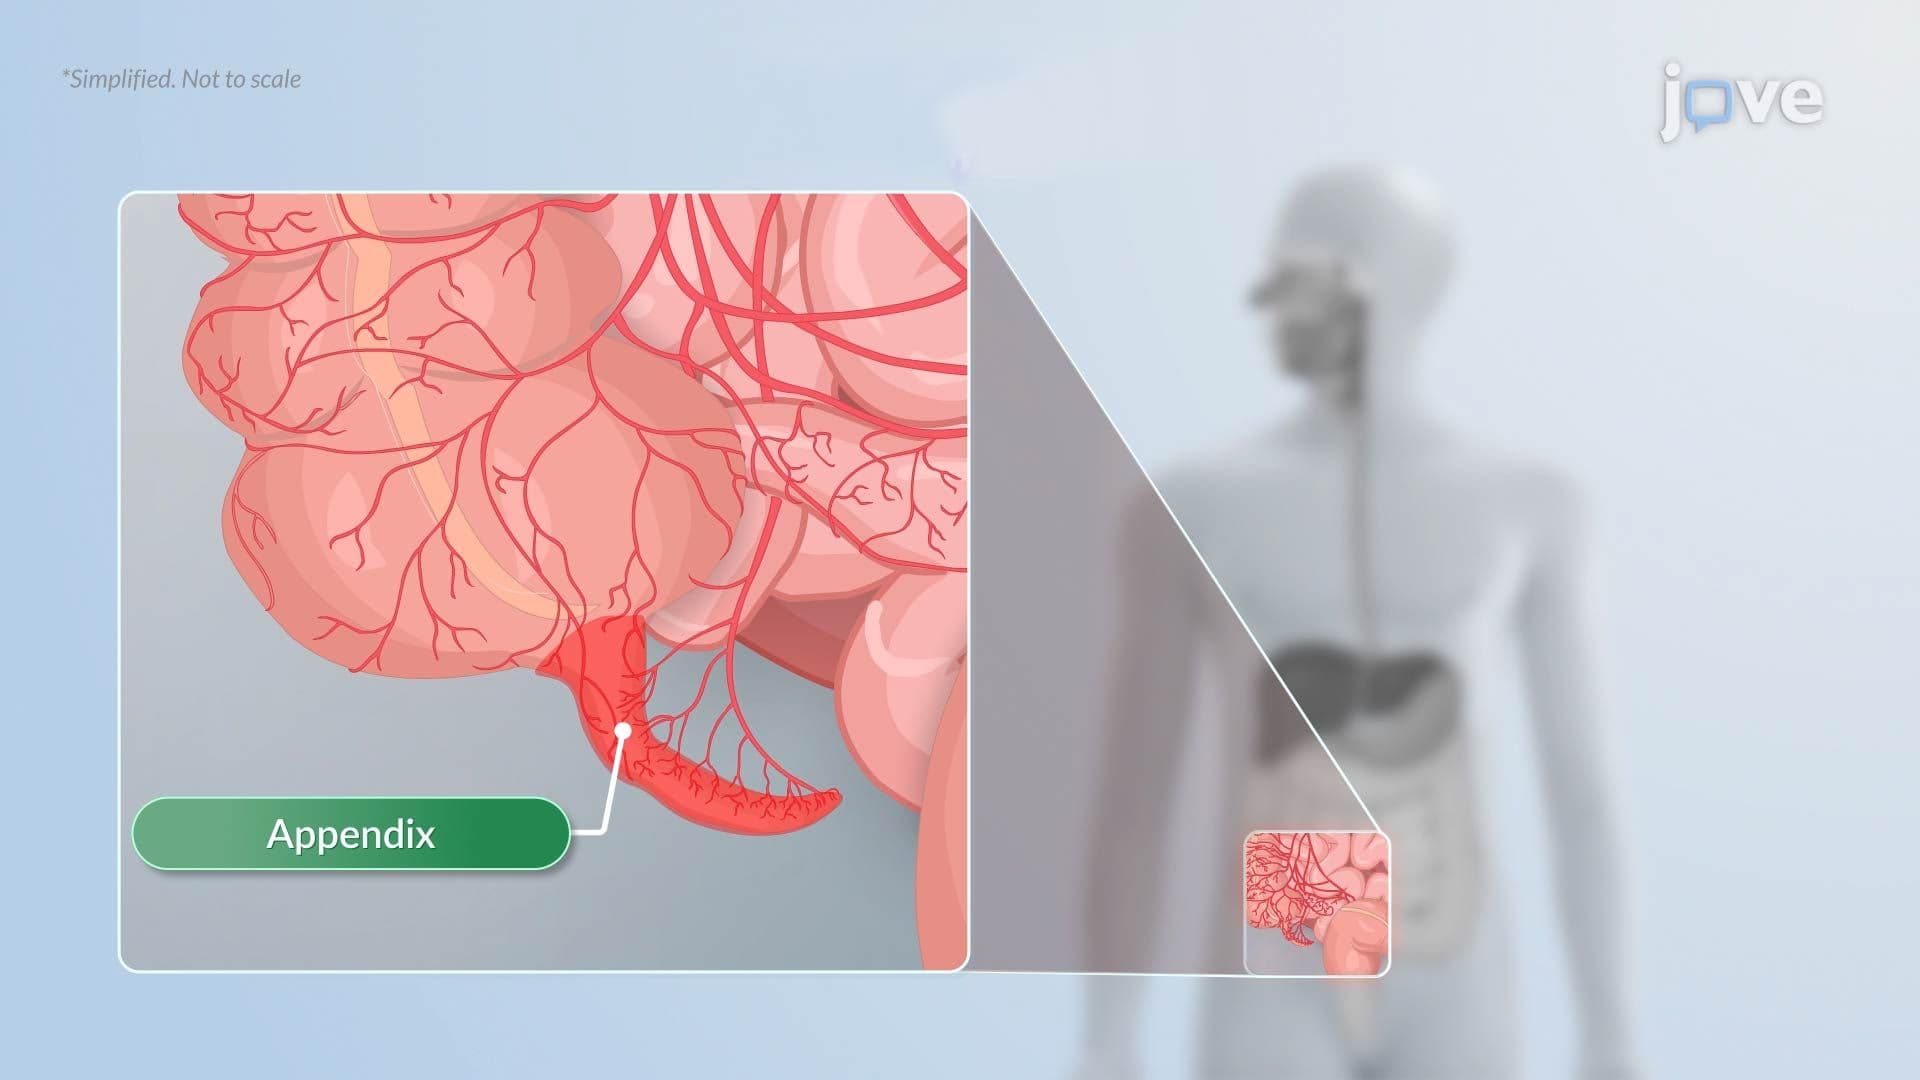
Appendicitis
 01:29
Intestinal Obstruction I: Introduction