Related Experiment Video
Updated: Sep 27, 2026
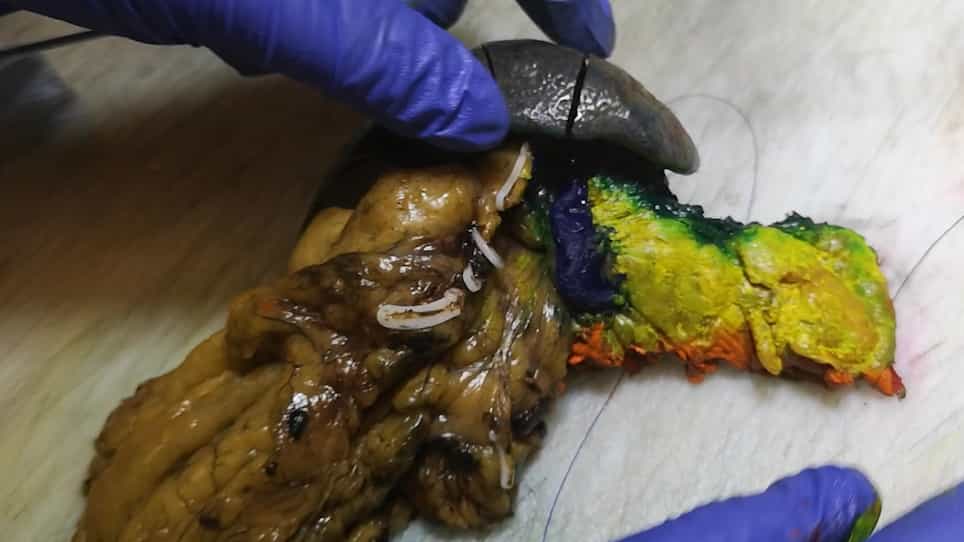

DIPLOMA Approach for Standardized Pathology Assessment of Distal Pancreatectomy Specimens
Published on: February 1, 2020
A modified CAP-based grading system incorporating non-tubular components for prognostic stratification in pancreatic
Naoki Sano1, Eriko Ikeda1,2, Kozue Ando2
1Department of Pathology, Jichi Medical University Hospital, 3311-1 Yakushiji, Shimotsuke, Tochigi, 329-0498, Japan.

Abstract:
Pancreatic ductal adenocarcinoma (PDAC) remains highly lethal; however, early-stage cases with improved survival are increasingly detected, underscoring the need for more standardized and clinically applicable histological grading in routine diagnostic practice. Based on 139 resected PDACs without neoadjuvant therapy, including 41 pT1 tumors, we propose a modified CAP-based grading system (mCAP). This system assesses the overall proportion of non-tubular components (NTC) and dense non-tubular clusters (DNTC), the latter defined as ≥ 30 non-tubular clusters within a 0.785 mm² area. DNTC was incorporated to capture focal dense non-tubular morphology not adequately reflected by overall NTC proportion alone. Tumors were classified as G1 (< 10% NTC and DNTC-negative), G2 (10-<50% NTC or < 10% NTC with DNTC positivity), or G3 (≥ 50% NTC). In Kaplan-Meier and log-rank analyses, mCAP showed prognostic stratification for both disease-free survival (DFS) and overall survival (OS). In multivariable Cox analysis for pT1c-pT3 tumors, mCAP G2/G3 remained independently associated with worse prognosis: the adjusted hazard ratios for mCAP G2/G3 versus G1 were 5.23 for DFS (95% confidence interval [CI], 2.58-10.61; P < 0.001) and 3.06 for OS (95% CI, 1.66-5.65; P < 0.001). In grade-only Cox models, mCAP showed the lowest Akaike information criterion (AIC) values for both DFS and OS among the three grading systems, suggesting more favorable model fit for mCAP. In the interobserver reproducibility study, unweighted Fleiss' kappa coefficients were 0.287 for WHO, 0.500 for CAP, and 0.531 for mCAP. Overall, mCAP may refine morphology-based risk stratification in resected PDAC.
