Related Experiment Video
Updated: Sep 27, 2026


Measuring Psoriasis Severity at Home
Published on: March 1, 2024
Potential of the electronic nose to diagnose psoriatic arthritis in different settings
Demy Dianne Gerritsen1, Marloes Leentjens2, Peter M Ten Klooster1
1Department of Technology, Human and Institutional Behaviour, University of Twente, Drienerlolaan 5, Enschede, 7522 NB , Netherlands.

Abstract:
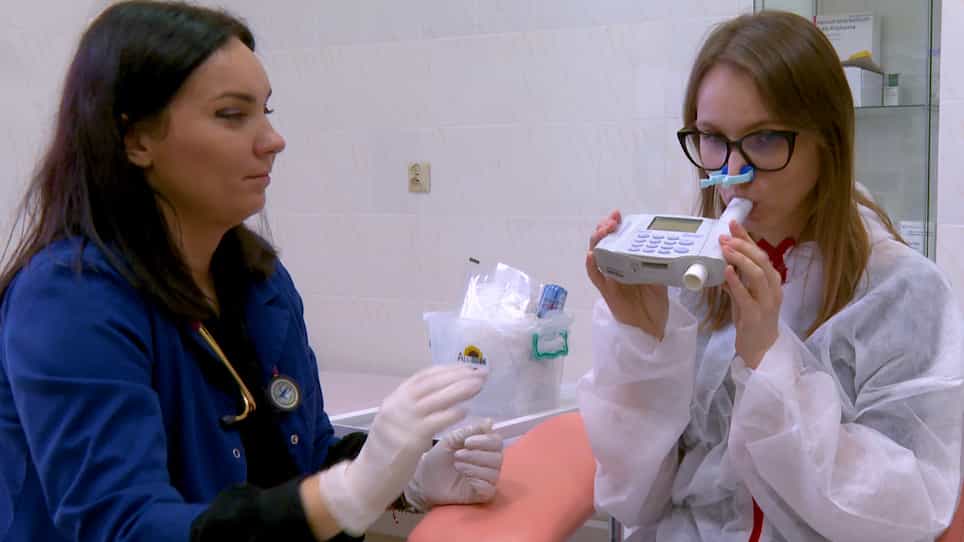
Early detection of psoriatic arthritis (PsA) is challenging because of its varied manifestations and diagnostic complexity. Disease-related factors such as inflammation influence metabolic processes and are detectable in volatile organic compounds (VOCs) in exhaled breath. This study explores the potential of an electronic nose (e-nose) for non-invasive PsA detection through exhaled breath analysis. Breath samples were collected from 57 outpatients with PsA and 180 healthy controls between November 2021 and March 2024. Sensor data were processed using the Aethena software package, and a Random Forest Extreme classifier was used to differentiate VOC patterns of PsA patients from healthy controls. Alternative thresholds for the e-nose risk scores were explored that maximized specificity while maintaining acceptable sensitivity (≥0.60) and vice versa. The e-nose classification score achieved an area under the receiver operating characteristic curve (AUROC) of 0.87 (95% CI: 0.80 - 0.93), effectively distinguishing PsA patients from healthy controls. The balanced risk score threshold showed a sensitivity and specificity of 0.82 and 0.79, respectively, with an accuracy of 0.80, positive predictive value of 0.55 and a negative predictive value of 0.93. Specificity could be increased to 0.97 (overall accuracy = 0.89) by increasing the classification threshold, whereas sensitivity could be increased to 0.89 (overall accuracy = 0.68) by decreasing the threshold. Exhaled breath analysis presents a promising non-invasive approach for diagnosing PsA, demonstrating good discriminatory ability. Differential cutoffs for e-nose risk prediction scores are proposed for settings that require either low false negative or false positive rates. Further studies that incorporate repeated assessments and account for the current design limitations are needed to confirm these findings.