Related Experiment Video
Updated: Sep 27, 2026


Percutaneous Endoscopic Unilateral-Approach Bilateral Decompression for Lumbar Spinal Stenosis
Published on: February 9, 2024
Preoperative versus Postoperative MRI Comparisons After the MILD Procedure vs. Open Decompression for Lumbar Spinal
Mark R Jones1, Luis M Fandos2, Jonathan S Daitch3
1Pain Medicine of the South, Knoxville, TN, USA; University of Tennessee Health Science Center College of Medicine, Knoxville, TN, USA.

Background Context:
The minimally invasive lumbar decompression (MILD) procedure, introduced in 2005, is a percutaneous fluoroscopy-guided technique designed as an alternative to open decompression for patients with lumbar spinal stenosis (LSS) causing neurogenic claudication. MILD specifically targets hypertrophied ligamentum flavum, allowing for expansion of the dural sac to relieve central stenosis, but it is not intended to treat lateral recess or foraminal stenosis. While published studies have reported symptomatic improvement, no study has evaluated pre- and postoperative MRI to assess its effectiveness in achieving anatomical decompression and improving nerve root sedimentation sign (SedSign).
Purpose:
To compare pre- and postoperative MRI findings in patients undergoing MILD versus open decompression, specifically evaluating changes in SedSign and anatomical decompression for LSS.
Study Design/Setting:
Multicenter cohort study conducted at seven centers between 2019 and 2024.
Patient Sample:
A total of 182 patients with LSS and a positive SedSign on preoperative MRI underwent either MILD (n = 162) by interventional pain management (IPM) physicians or open decompression (n = 20) by an orthopedic spine surgeon. All patients received postoperative MRI for assessment.
Outcome Measures:
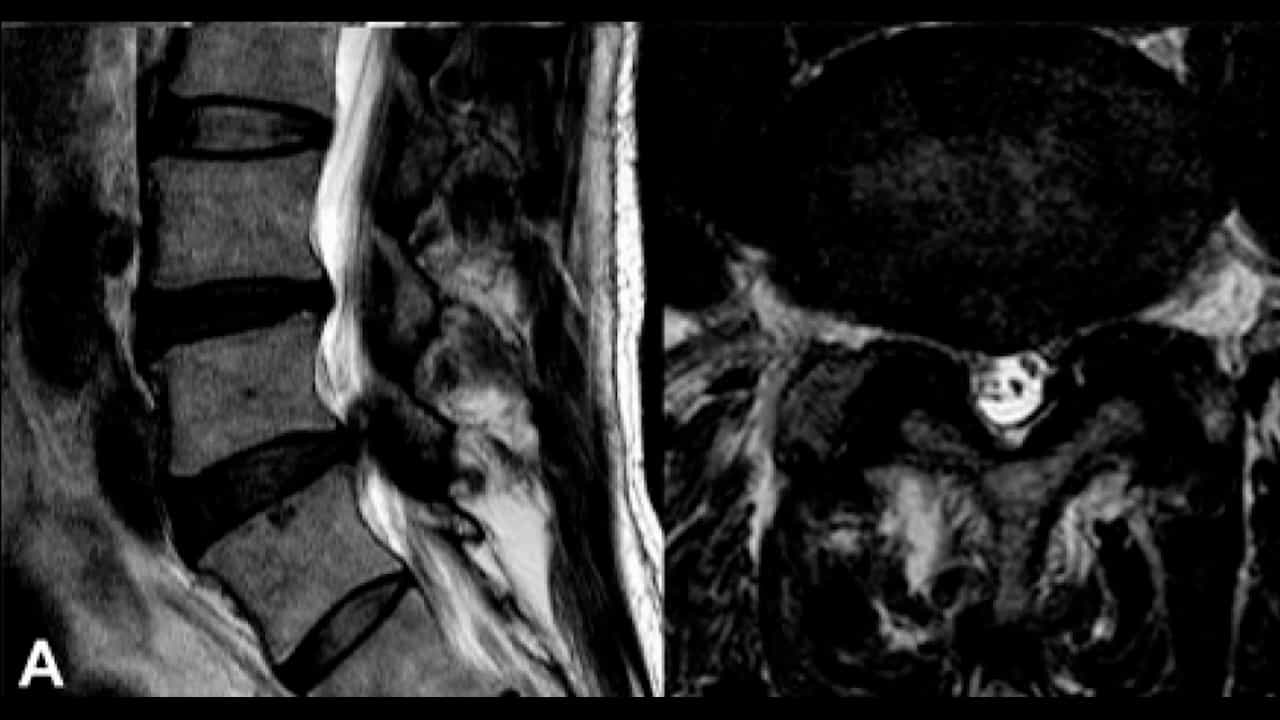
Measures included pre- and postoperative MRI assessments evaluating SedSign improvements, decrease in ligamentum flavum thickness, presence of a lamina defect and multifidus muscle scar signal changes.
Methods:
Patients were assigned to treatment based on the specialty of the consulting physician: IPM physicians performed MILD (Group 1), and an orthopedic spine surgeon performed open decompression (Group 2). Blinded radiologists reviewed pre- and postoperative MRI scans to assess SedSign and anatomical changes. Interobserver and intraobserver reliability were analyzed using Cohen kappa statistics.
Results:
Group 1 demonstrated no SedSign improvement or anatomical changes. Group 2 achieved 100% SedSign reversal, >90% ligamentum flavum removal, 100% lamina defect and multifidus muscle scar signal changes postoperatively. No complications were reported in either group.
Conclusion:
The MILD procedure did not produce anatomical decompression or SedSign reversal on MRI, whereas open decompression reliably achieved both. Secondary anatomical changes, such as scar tissue and muscle signal alterations, were observed only in the open surgery group. These findings suggest that while MILD is tissue-sparing, it may be insufficient for achieving anatomical goals in patients with central LSS. Future percutaneous strategies should aim to combine the anatomical effectiveness of open decompression with the reduced tissue disruption characteristic of less exposure approaches.