Related Experiment Video
Updated: Sep 27, 2026
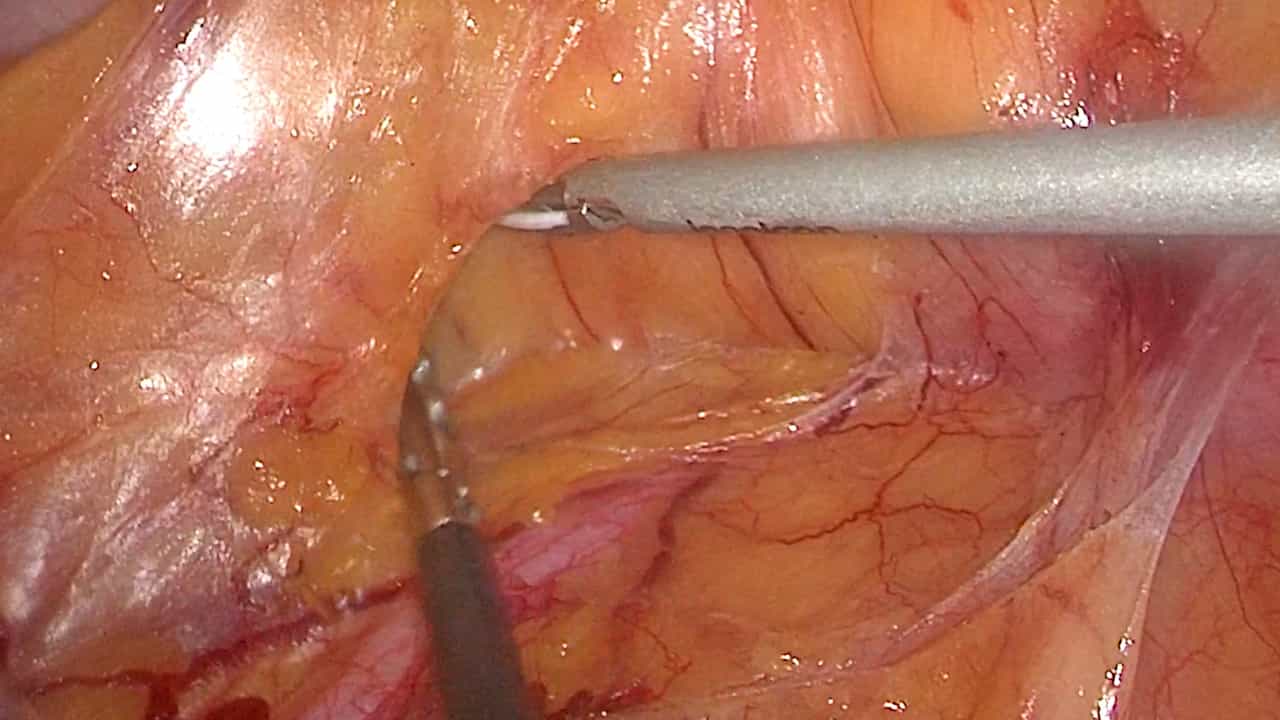

Caudal-to-cranial Approach in Laparoscopic Right Hemicolectomy with Complete Mesocolon Excision and D3 Lymph Node Dissection
Published on: January 9, 2026
Parastomal hernia outcomes after sutured versus unsutured composite techniques for specimen-extraction-site loop
Jiajia Mao1, Pingtian Xia1, Yanlei Wang1
1Department of General Surgery, Qilu Hospital of Shandong University, 107 West Wenhua Road, Jinan, Shandong, China.

Background:
Protective loop ileostomy created at the specimen-extraction site is a minimally invasive option after laparoscopic low anterior resection for rectal cancer. Whether different composite techniques influence parastomal hernia risk remains uncertain.
Methods:
This prospective, open-label, single-center randomized controlled trial enrolled patients undergoing laparoscopic low anterior resection for rectal cancer with protective specimen-extraction-site loop ileostomy. Patients were randomized intraoperatively to a sutured composite technique, consisting of fascial/peritoneal fixation without a supporting rod, or an unsutured composite technique, consisting of no fascial/peritoneal fixation, routine supporting rod placement, and creation of a smaller tailored fascial aperture. The primary outcome was parastomal hernia before ileostomy reversal, assessed by standardized clinical examination, routine pre-reversal computed tomography, and intraoperative assessment at reversal.
Results:
Of 233 randomized patients, 216 were analyzed per protocol, including 111 in the sutured group and 105 in the unsutured group. Parastomal hernia occurred in 13.5% (15/111) and 4.8% (5/105), respectively (risk ratio 0.35, 95% CI 0.13-0.94; risk difference -8.7%, 95% CI - 16.3 to - 1.2; P = 0.047). Stoma formation time was shorter in the unsutured group (median 24 vs 31 min; Hodges-Lehmann difference - 7.2 min, 95% CI -9.0 to -5.4; P <0.001). Time to first stoma output was earlier in the unsutured group (median 12 vs 15 h; Hodges-Lehmann difference - 3.0 h, 95% CI - 4.7 to - 1.8; P <0.001), although this difference was not associated with shorter hospital stay. Other stoma-related complications, reversal outcomes, and quality of life scores were similar between groups.
Conclusion:
The unsutured composite technique was associated with lower parastomal hernia risk and shorter stoma formation time compared with the sutured composite technique, without apparent differences in other stoma-related or reversal outcomes. Because the intervention comprised multiple technical components, the independent effect of each component could not be determined.
Trial Registration:
The trial was registered at ClinicalTrials.gov (NCT06344923).
