Related Experiment Video
Updated: Sep 27, 2026
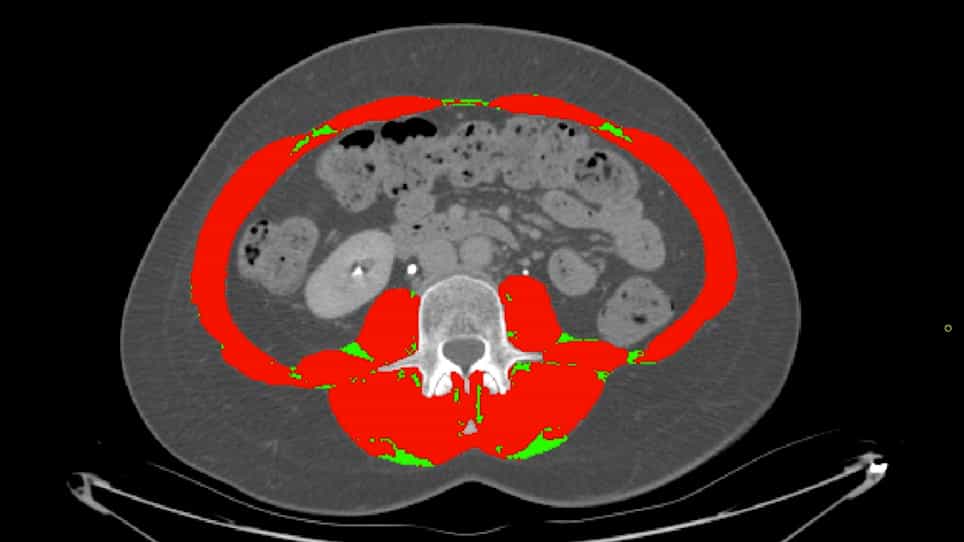

Segmentation and Linear Measurement for Body Composition Analysis using Slice-O-Matic and Horos
Published on: March 21, 2021
Pragmatic Screening for Sarcopenia in Non-Small Cell Lung Cancer: Development and Internal Validation of a
Zhuorui You1,2, Wei Dai3, Hechen Shen1
1Department of Thoracic Surgery, Sichuan Academy of Medical Sciences, Sichuan Provincial People's Hospital, University of Electronic Science and Technology of China, Chengdu, Sichuan, China.

Background:
Sarcopenia or low muscle mass is common in non-small cell lung cancer and predicts poorer outcomes, but its assessment typically relies on CT-based skeletal muscle index at the L3 vertebral level. Standard chest CTs often omit the L3 level, leaving many patients without a straightforward muscle mass measure, so sarcopenia frequently goes undetected. We therefore evaluated whether thoracic CT measurements could reliably substitute for L3 SMI and developed a simple, accurate clinical tool to identify patients at risk of CT-defined low muscle mass.
Methods:
In retrospective (n = 192) and prospective (n = 177) cohorts of NSCLC patients, cross-sectional muscle area was quantified on CT at L3, T12, and T4. Deming regression and Bland-Altman analysis were used to assess correlations and agreement between T4- or T12-derived SMI and reference L3 SMI. Candidate clinical predictors were selected based on univariate associations and clinical plausibility, and machine-learning methods identified five routine variables, which were combined into the Lung Cancer Patients' Sarcopenia Risk Model (LSRM). Model performance was evaluated in terms of discrimination, calibration, and risk stratification and compared with established clinical indices like BMI and the advanced lung cancer inflammation index (ALI).
Results:
T12-derived SMI showed a strong correlation and minimal bias versus L3, outperforming T4-derived SMI. A conversion equation was established to estimate L3 SMI from T12. The LSRM, incorporating age, body mass index, carcinoembryonic antigen, C-reactive protein, and lymphocyte count, demonstrated good discrimination, satisfactory calibration, and clear three-tier risk stratification. It outperformed BMI and ALI in identifying CT-defined low muscle mass.
Conclusion:
T12 measurements on routine chest CT can replace L3 for muscle assessment. The LSRM provides a practical bedside tool for screening patients at risk of CT-defined low muscle mass in NSCLC without additional imaging, supporting earlier risk identification and integration into routine care.