Related Experiment Video
Updated: Sep 27, 2026
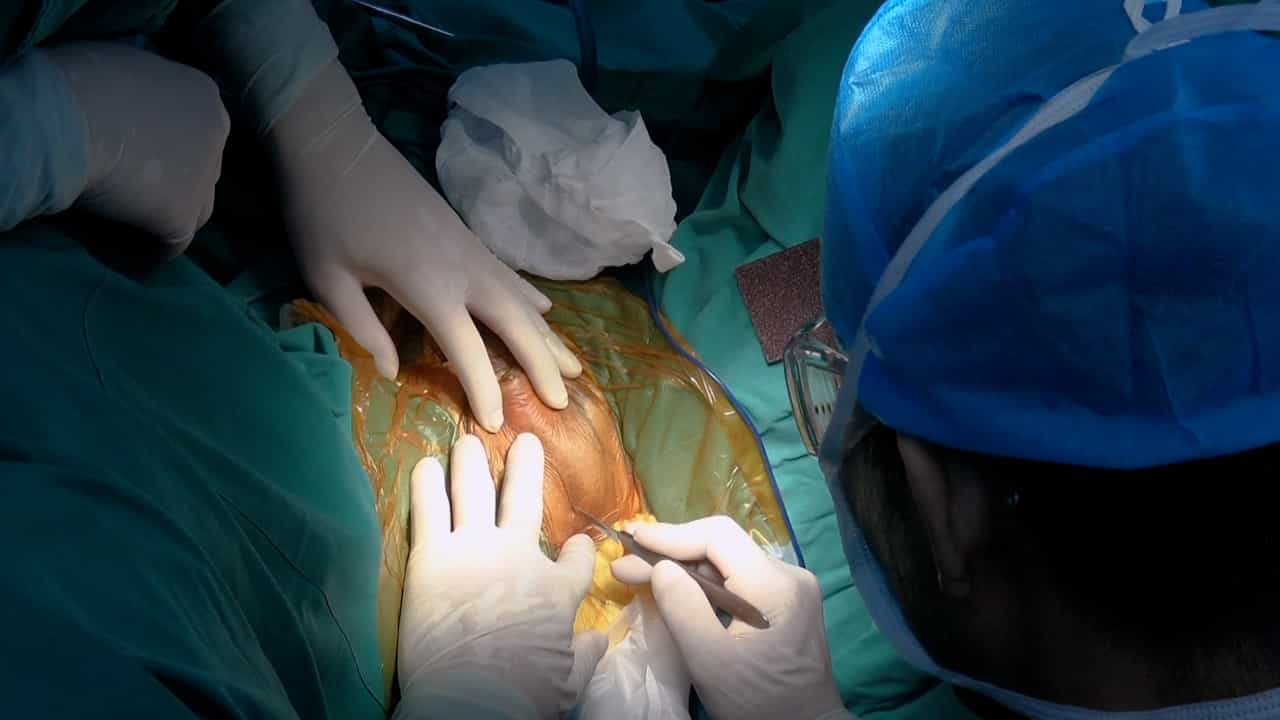

Transcorporal Artificial Urinary Sphincter Cuff Placement in a Case Requiring Revision for Urethral Atrophy
Published on: June 16, 2022
Early Outcomes After Discontinuing Routine Gentamicin Irrigation During AMS 800 Artificial Urinary Sphincter
Michał Andrzej Skrzypczyk1, Anna Pliszka1, Łukasz Białek1
1Department of Urology, Centre of Postgraduate Medical Education, 00-416 Warsaw, Poland.

Abstract:
Background/Objectives: Routine local gentamicin irrigation has been used during artificial urinary sphincter (AUS) implantation despite limited procedure-specific evidence. We evaluated early outcomes after its calendar-defined discontinuation. Methods: This single-centre retrospective before-after cohort included 173 uncoated AMS 800 procedures in 164 men: 59 under a gentamicin-containing local protocol and 114 after gentamicin withdrawal. Saline device immersion and Betadine-containing intraoperative irrigation of the operative field and both wounds continued in both periods. Clinician-recorded surgical-site infection (SSI) within 90 days was the antimicrobial outcome of greatest direct relevance. Complete explantation within 90 days for SSI and/or urethral erosion was an exploratory device-related endpoint; all-cause complications at 30 and 90 days were secondary safety outcomes. Results: SSI occurred after 1/59 (1.7%) gentamicin-protocol and 2/114 (1.8%) gentamicin-free procedures (risk difference +0.1 percentage points, 95% confidence interval -7.4 to +4.7; p = 1.000). Erosion occurred after 0/59 and 4/114 (3.5%) procedures; all four led to complete explantation. The explantation endpoint occurred after 1/59 versus 4/114 procedures (risk difference +1.8 percentage points, 95% confidence interval -5.8 to +7.2; p = 0.662). Thirty-day all-cause complications occurred after 14/59 versus 16/114 procedures and 90-day complications after 15/59 versus 26/114. Conclusions: No statistically significant between-period difference was detected in SSI, exploratory device-related explantation, or broad all-cause complications. Sparse events, wide confidence intervals and calendar-defined exposure amid concurrent era changes preclude conclusions regarding equivalence or absence of clinically relevant benefit or harm.
