Related Experiment Video
Updated: Sep 27, 2026

One-day Workflow Scheme for Bacterial Pathogen Detection and Antimicrobial Resistance Testing from Blood Cultures
Published on: July 9, 2012
Analytical and Clinical Evaluation of a Fully Automated Direct-from-Whole-Blood Multiplex PCR Assay Using
Chi-Sheng Tai1, Hsing-Yi Chung2, Tai-Han Lin2
1Graduate Institute of Medical Science, National Defense Medical University, Taipei City 11490, Taiwan.

Abstract:
Background/Objectives: Prompt identification of bloodborne pathogens and their antimicrobial resistance is critical for effective sepsis management. Direct molecular testing of blood offers faster results than blood culture; however, its clinical utility has been limited by suboptimal sensitivity and procedural complexity. This study evaluated an automated rapid multiplex PCR assay (BPID® system) and compared its performance with gold-standard methods. Methods: This was a preliminary, single-centre diagnostic-agreement study. Forty-three whole-blood samples were collected from patients with suspected bloodstream infection at Tri-Service General Hospital, Taipei, Taiwan, between January 2025 and January 2026, and were analysed. Three molecular methods and two culture-based methods were compared: the BPID® system, a Qiagen®-based workflow, the BioFire® FilmArray® BCID2 panel, blood culture, and MALDI-TOF MS identification. Positive percent agreement (PPA) was calculated at the organism level against a composite reference standard. Analytical sensitivity (limit of detection, LoD) was assessed in whole blood spiked with serial dilutions of ten reference organisms. Results: The composite reference standard yielded 47 reference-positive organisms across 42 samples. The BPID® system achieved a PPA of 95.74% (95% CI, 85.8-98.8), numerically similar to the post-culture BCID2 panel (93.62%; p = 1.00, exact McNemar test), and higher than the Qiagen® workflow (72.34%; p = 0.001), blood culture (72.34%; p = 0.007), and MALDI-TOF MS (74.47%; p = 0.013). In a sensitivity analysis using a composite reference standard from which the index test was excluded, 46 organisms remained reference-positive and the PPA of the BPID® system was 95.65% (44/46; 95% CI, 85.5-98.8), again numerically similar to the BCID2 panel (93.48%; p = 1.00). For antimicrobial resistance determinants covered by both panels, the BPID® system reproduced the BCID2 determinant profile in all 16 specimens in which such a determinant was reported (100%), versus 10 of 16 specimens (62.5%) for the Qiagen® method. Confirmed LoD values for the BPID® system were 0.67-20.81 CFU/mL, an 8.8- to 24.3-fold improvement over the Qiagen® method (6.51-224.61 CFU/mL). Conclusions: The automated BPID® system substantially improves PCR-based diagnostic sensitivity for bacteremia and, by operating directly on whole blood, removes the culture-incubation step that post-culture molecular panels require. Because the study was not designed as an equivalence or non-inferiority trial and evaluated only 43 specimens, the similar agreement observed for the BPID® system and the BCID2 panel should not be interpreted as demonstrated equivalence; these findings should be regarded as a preliminary clinical evaluation requiring confirmation in larger multicentre studies that also enrol culture-negative and uninfected controls.

Related Concept Videos
 01:24
Automated Microbial Diagnostics
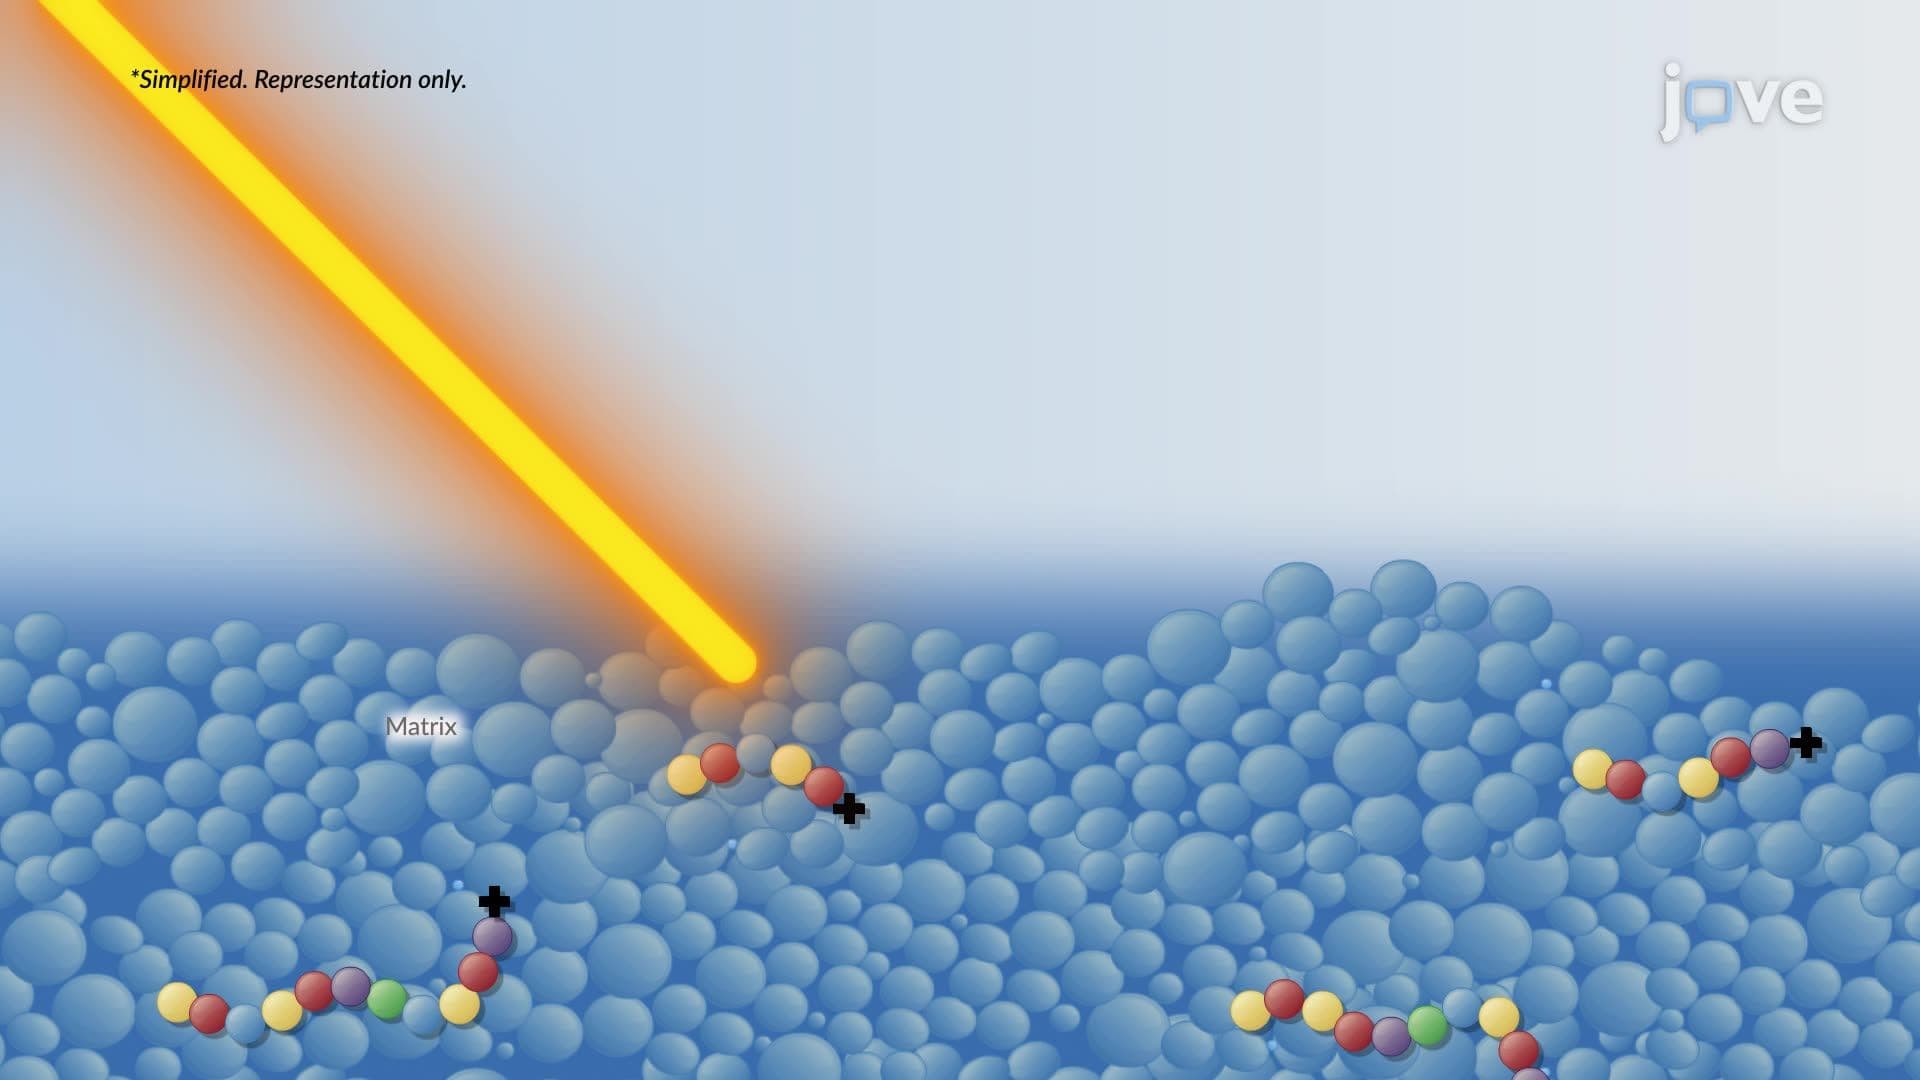 01:25
Rapid Identification of Pathogens