Related Experiment Video
Updated: Sep 27, 2026
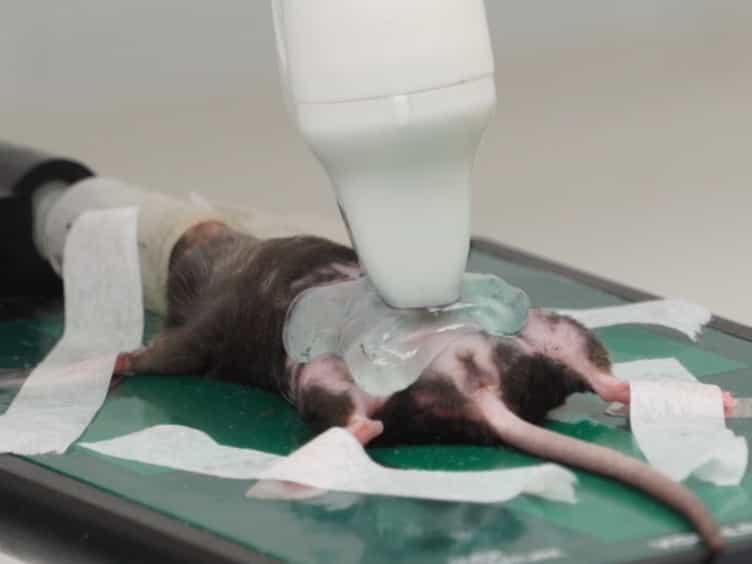

A Novel Use of Three-dimensional High-frequency Ultrasonography for Early Pregnancy Characterization in the Mouse
Published on: October 24, 2017
Development of Novel Prenatal Prediction Models for Birth-Weight Estimation in Low-Risk Third-Trimester Pregnancies
Sevda Yelec1, Rauf Melekoglu2, Yusuf Kemal Arslan3
1Department of Obstetrics and Gynecology, Diyarbakır Gazi Yasargil Health Research Center, University of Health Sciences, Diyarbakır 21070, Türkiye.

Abstract:
Objective: Sonographic evaluation of the fetus and estimation of fetal weight are integral components of modern obstetric practice. Estimated fetal weight (EFW) plays a crucial role in predicting macrosomia, diagnosing intrauterine growth restriction, and monitoring fetal development. This study aimed to improve birth-weight prediction in low-risk term pregnancies by combining conventional fetal biometry with maternal anthropometry and selected fetal soft-tissue and cardiac measurements. Materials and Methods: In 94 low-risk, term singleton pregnancies scheduled for elective cesarean delivery, standardized prenatal ultrasound was performed within 24 h before birth by a single operator. Neonatal anthropometry was obtained within 6 h postnatally. Multiple linear regression was used to develop conventional and extended prenatal birth-weight prediction models with actual birth weight as the dependent variable, and their performance was compared with Hadlock EFW. Results: Mean actual birth weight was 3178.9 ± 359.5 g and mean Hadlock EFW was 3201.6 ± 399.7 g. Hadlock estimation correlated strongly with birth weight (r = 0.826) and had a mean absolute error (MAE) of 181.0 g. Abdominal circumference was the strongest conventional sonographic correlate of birth weight. The conventional prenatal Model 2 achieved R2 = 0.710 and MAE = 150.1 g. The extended prenatal Model 5, which combined conventional biometry with symphysis-fundal height, femoral soft-tissue thickness, right atrial area, maternal abdominal fat thickness, and aortic valve diameter, showed the best performance (R2 = 0.783; MAE = 133.2 g). Its optimism-corrected and repeated cross-validated R2 values were 0.739 and 0.725, respectively. Conclusions: The newly proposed formulas, particularly Model 5, demonstrated better internally validated predictive performance than the Hadlock baseline in this cohort, suggesting that the integration of selected maternal anthropometric and additional fetal ultrasonographic measurements with conventional biometry may improve birth-weight estimation. These findings warrant external validation in larger and more diverse populations prior to clinical implementation.
