Related Experiment Video
Updated: Sep 27, 2026
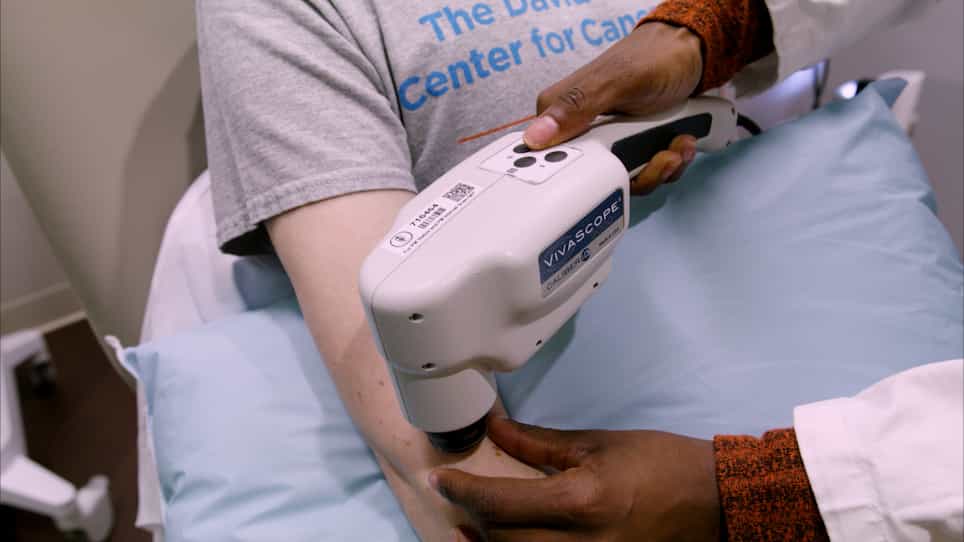

Combining Reflectance Confocal Microscopy with Optical Coherence Tomography for Noninvasive Diagnosis of Skin Cancers via Image Acquisition
Published on: August 18, 2022
Contemporary Multimodal Management of Cutaneous Malignancies: Surgery, Radiotherapy, Systemic Therapy, Molecular
Dariusz Kowalczyk1, Jolanta Jaworek2, Andrzej Ciborek1
1Faculty of Medicine and Health Sciences, University of Kalisz, 62-800 Kalisz, Poland.

Background:
The therapeutic management of cutaneous malignancies-cutaneous melanoma, cutaneous squamous-cell carcinoma (cSCC), basal-cell carcinoma (BCC) and Merkel-cell carcinoma (MCC)-has shifted toward multimodal, stage-adapted treatment integrating surgery, radiotherapy, molecularly targeted therapy and immune checkpoint inhibition.
Methods:
We conducted a structured narrative review with a structured literature search of PubMed/MEDLINE, Scopus and Web of Science (January 2015-6 September 2026), prioritising current clinical practice guidelines, randomised controlled trials and phase II-III studies; landmark older trials were included separately.
Synthesis:
Surgery with adequate histological margins, including Mohs micrographic surgery where appropriate, remains definitive for localised disease. In resectable macroscopic stage III melanoma, neoadjuvant ipilimumab plus nivolumab with response-driven postoperative management improved event-free survival versus adjuvant nivolumab in NADINA. SWOG S1801 independently demonstrated an event-free-survival advantage for perioperative pembrolizumab over adjuvant-only pembrolizumab in resectable stage III-IV melanoma. In advanced melanoma, dual immune-checkpoint strategies and BRAF/MEK inhibition require patient-specific sequencing; in the European Union, nivolumab plus relatlimab is authorised for first-line advanced melanoma with tumour-cell PD-L1 expression <1%. In high-risk cSCC after surgery and radiotherapy, adjuvant cemiplimab improved disease-free survival. In advanced BCC, Hedgehog-pathway inhibitors remain the principal first systemic option, with anti-PD-1 therapy after HHI failure or intolerance.
Clinical Implications:
Molecular testing should be indication-driven: BRAF V600 is a validated treatment-selecting biomarker, while broader NGS profiling (including NRAS, KIT, NF1, TERT and co-occurring alterations), PD-L1, tumour mutational burden and circulating tumour DNA have context-dependent, supportive or investigational roles.
Conclusions:
The major unresolved issues are optimal sequencing, response-adapted perioperative treatment, resistance, biomarker validation and treatment of transplant, frail and other under-represented populations.
Related Concept Videos
 01:27
Tumor Immunotherapy
 02:57
Targeted Cancer Therapies
There are several types of targeted therapies against specific...
02:57Targeted Cancer Therapies
There are several types of targeted therapies against specific...
 01:30
Skin Cancer
Basal Cell Carcinoma (BCC): BCC is the most common type of skin cancer, accounting for about 80% of cases. It typically develops in...
 02:49
Cancer Therapies
However, cancer treatments can pose several challenges, as therapies used to kill cancer cells are generally also toxic to normal cells. Moreover, cancer cells mutate rapidly and can develop resistance to chemical agents or radiation therapy. Besides, all types of cancer cells may not respond to the same therapy. Some cancer cells respond to one...
02:49Cancer Therapies
However, cancer treatments can pose several challenges, as therapies used to kill cancer cells are generally also toxic to normal cells. Moreover, cancer cells mutate rapidly and can develop resistance to chemical agents or radiation therapy. Besides, all types of cancer cells may not respond to the same therapy. Some cancer cells respond to one...