Related Experiment Video
Updated: Sep 27, 2026
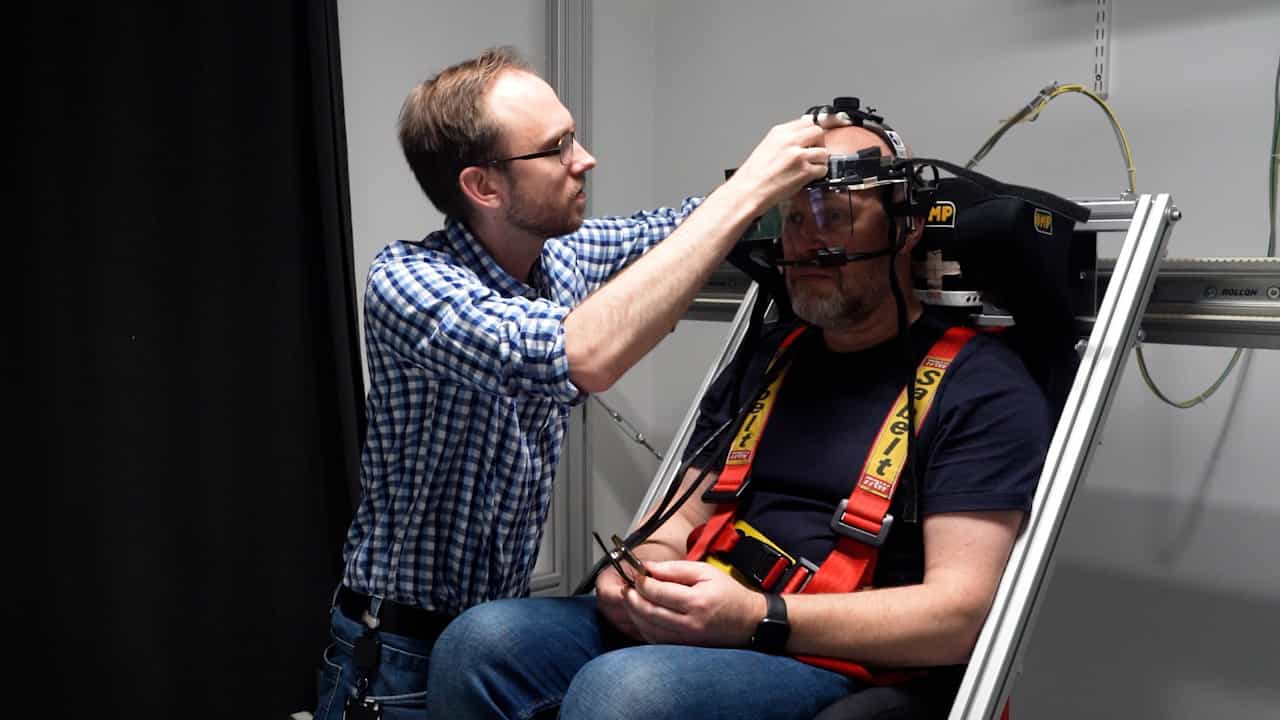

Using Eye-tracking to Assess the Relative Importance of Visual and Vestibular Input to Subcortical Motion Processing in the Roll Plane
Published on: August 22, 2025
Differentiating Persistent Postural-Perceptual Dizziness from Anxiety Disorder Using Behavioral Responses to Complex
Kübra Orman1, Hanifi Korkmaz2, Sevilay Hançer Tecimer3
1Department of Psychiatry, Malatya Turgut Özal University, Malatya 44210, Türkiye.

Abstract:
Background/Objectives: Persistent postural-perceptual dizziness (PPPD) and anxiety disorder (AD) share overlapping clinical features that make differentiation with conventional assessments challenging. This study examined whether virtual reality (VR)-based vestibular assessment and immersive phobic scenarios can reveal distinct response profiles between these conditions. Methods: In this preliminary, single-center, cross-sectional study, 32 participants (PPPD: n = 15, AD: n = 17) underwent joint otorhinolaryngological/audiological and psychiatric evaluation, including the Clinical Test of Sensory Interaction and Balance-VR (CTSIB-VR), Limits of Stability (LOS), Dizziness Handicap Inventory (DHI), Beck Anxiety Inventory (BAI), and two immersive VR scenarios (CrowdVR and Supermarket Scrolling). Symptom onset latency, maximum tolerated intensity, avoidance behavior, and post-scenario Simulator Sickness Questionnaire (SSQ) scores were recorded after each scenario. Results: Groups did not differ on any LOS parameter. CTSIB-VR Visual Preference was significantly higher in the PPPD group (74.07 ± 7.44 vs. 60.82 ± 2.46, p < 0.001). SSQ Disorientation scores during the CrowdVR and Supermarket Scrolling scenarios were significantly elevated in PPPD (p = 0.004 and p = 0.002, respectively); at baseline VR exposure, SSQ Disorientation showed the same directional pattern but did not reach significance (p = 0.069), and the SSQ Total Severity score at baseline was numerically higher in PPPD (51.61 ± 17.62 vs. 41.13 ± 11.83) at a trend level (p = 0.055). BAI Total was markedly higher in the AD group (29.82 ± 4.86 vs. 19.27 ± 6.43, p < 0.001). Symptom onset latency during CrowdVR exposure was longer in PPPD (median 5.36 vs. 3.10 min, p = 0.007), whereas avoidance behavior was more pronounced in the AD group (p = 0.027). Conclusions: PPPD and AD showed divergent, exploratory VR-based response profiles: PPPD was marked by visual dependence, prolonged tolerance, and greater disorientation, while AD showed higher anxiety burden and earlier avoidance. These preliminary, hypothesis-generating findings suggest scenario-based VR assessment may merit further study as an adjunct in differentiating PPPD from anxiety disorder, pending diagnostic-accuracy validation in larger, multicenter cohorts.