Related Experiment Video
Updated: Sep 27, 2026


Local Anesthetic Thoracoscopy for Undiagnosed Pleural Effusion
Published on: November 10, 2023
Diaphragm-Directed Strategies for Prolonged Air Leak Prevention After Lung Resection: A Narrative Review of the
Ruoran Xia1, Evgeniy Tarabrin1, Sergey Muraviev1
1Department of Hospital Surgery No. 2, Sechenov University, 119991 Moscow, Russia.

Abstract:
Background/Objectives: Prolonged air leak (PAL) remains one of the most common and costly complications after lung resection. A growing body of evidence implicates the residual pleural space (RPS) as a central pathogenetic link between recognized risk factors and persistence of the alveolopleural fistula. This review synthesizes evidence on RPS pathogenesis and compares six interventions that reduce RPS by acting on the diaphragm for PAL prevention. Methods: A narrative literature search was performed in PubMed, Google Scholar, Web of Science, eLibrary.ru, and China National Knowledge Infrastructure (CNKI), covering clinical and experimental studies, systematic reviews, and classic physiological work relevant to intrapleural pressure (IPP), RPS, and diaphragmatic control. Results: RPS and PAL are reciprocally linked, and major, upper-lobe, and right-sided resection independently predict both. RPS is accompanied by excess negative IPP, reduced lung compliance, and disproportionate wall stress at the resection margin. Six methods for reducing RPS volume through diaphragmatic control are described. Conclusions: RPS is the mechanistic link connecting established PAL risk factors to fistula persistence. Among the six methods, chemical denervation with botulinum toxin type A (BTX-A) is, in principle, the only method combining full reversibility, dose-dependent control, and no need for dedicated equipment. However, this conclusion rests on a single pilot animal study in a lower-lobectomy model, and translating it to upper-lobe, low-reserve patients, who carry the greatest PAL burden, requires dedicated dose-ranging and safety work before a clinical trial can be considered.
Related Concept Videos
 01:27
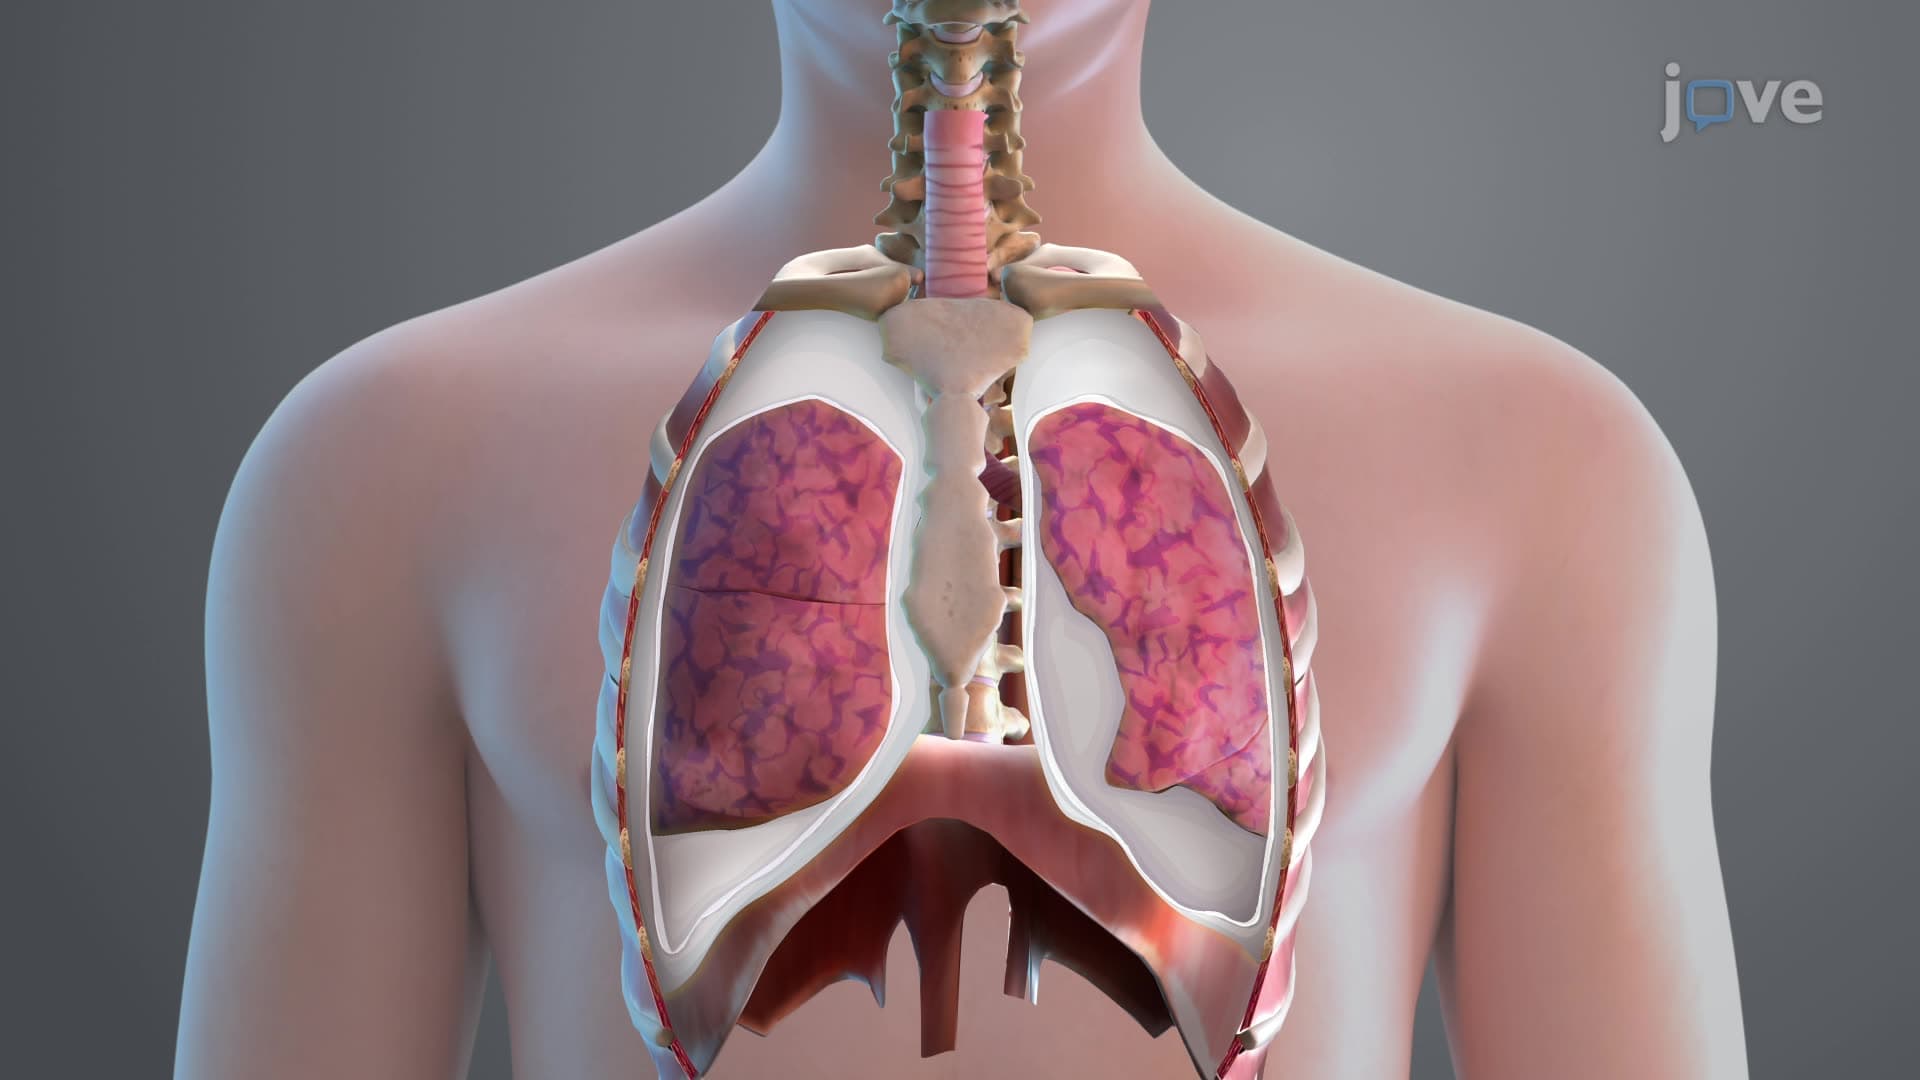
Pneumothorax-II
Clinical Manifestations:
 01:13
Pleura of the Lungs
 01:08
Pneumothorax II: Pathophysiology
 01:26
Pneumothorax-I
Pneumothorax can be even further classified as spontaneous, traumatic, and tension pneumothorax.
 01:28
Pleural Effusion II: Symptoms and Management
A pleural effusion is the abnormal collection of fluid between the parietal and visceral pleura layers of tissue that form the lining of the lungs and chest cavity. It can occur independently or due to surrounding parenchymal diseases, such as infection, malignancy, or inflammatory conditions.
Clinical Manifestations:
 01:30
Pleural Disorders: Types and Brief Description