Related Experiment Video
Updated: Sep 27, 2026
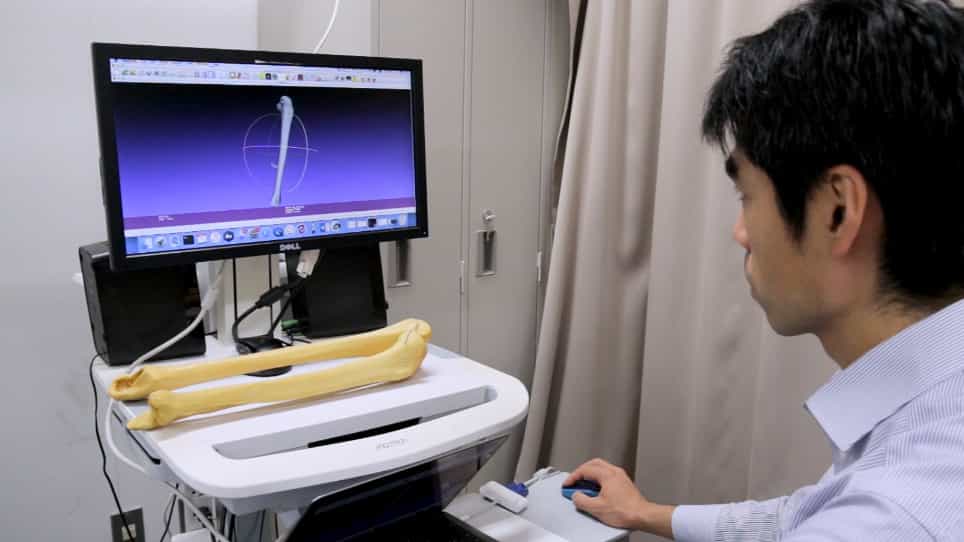

Four-Dimensional CT Analysis Using Sequential 3D-3D Registration
Published on: November 23, 2019
A Novel Lateral Tibiofibular Index for Simulated Posterior Fibular Translation: A Three-Dimensional CT Study
Oğuzhan Tanoğlu1, Hamit Çağlayan Kahraman2
1Department of Orthopaedics and Traumatology, Izmir Democracy University, 35140 Izmir, Türkiye.

Abstract:
Background/Objectives: The diagnosis of syndesmotic instability remains challenging, particularly in quantifying posterior fibular translation. This study aimed to assess the Lateral Tibiofibular Index (LTI), a novel lateral projection-based parameter, using standardized projections derived from three-dimensional computed tomography (3D CT) models. Methods: This retrospective simulation study included 80 adults (160 ankles; 40 women and 40 men; mean age, 42.7 ± 12.4 years). Native 3D models were used to generate standardized lateral projections, after which isolated posterior fibular translations of 1 mm and 2 mm were simulated. Three linear parameters (A, B, C) were defined based on fixed anatomical landmarks. The LTI was calculated using the formula (A + B)/(B + C). Four ratio-based candidate indices were evaluated. Receiver operating characteristic (ROC) analyses used participant-level clustered resampling to account for bilateral and repeated observations. Results: Mean LTI increased from 1.306 ± 0.099 in native ankles to 1.406 ± 0.109 after 1 mm translation and 1.515 ± 0.121 after 2 mm translation. The LTI showed an area under the curve (AUC) of 0.756 (95% confidence interval [CI], 0.727-0.793) for native versus 1 mm translation and 0.916 (95% CI, 0.885-0.946) for native versus 2 mm translation. Youden-derived thresholds were 1.357 (sensitivity, 67.5%; specificity, 74.4%) and 1.381 (sensitivity, 89.4%; specificity, 80.6%), respectively. Conclusions: The LTI showed promising simulation-based discrimination of native anatomy from controlled posterior fibular translation, particularly at 2 mm. An LTI of approximately 1.50 should be regarded as a provisional upper reference value rather than a validated diagnostic cut-off. Prospective clinical studies in patients with confirmed syndesmotic injury are needed to further evaluate the diagnostic and intraoperative applicability of this parameter.
More Related Videos
 09:01
Treatment of Ankle Osteoarthritis with Total Ankle Replacement Through a Lateral Transfibular Approach
Published on: January 24, 2018
 06:28
Anterior Cruciate Ligament Transection and Synovial Fluid Lavage in a Rodent Model to Study Joint Inflammation and Posttraumatic Osteoarthritis
Published on: September 2, 2025