Related Experiment Video
Updated: Sep 27, 2026


Home-Based Prescribed Pulmonary Exercise in Patients with Stable Chronic Obstructive Pulmonary Disease
Published on: August 24, 2019
Active Case Finding of Chronic Obstructive Pulmonary Disease in Romanian Primary Care
Andreea Narcisa Iana1, Daniela Gurgus1, Roxana Folescu1
1Family Clinic, Center of Preventive Medicine, University of Medicine and Pharmacy Victor Babes, 300023 Timișoara, Romania.

Abstract:
Background and Objectives: Chronic obstructive pulmonary disease (COPD) is one of the leading causes of death worldwide and represents a major contributor to the global burden of disease. According to the World Health Organization it is the third leading cause of death worldwide and the seventh leading cause of poor health worldwide. Our aim was to evaluate the effectiveness of active case finding of COPD in Romanian primary care through the COPD Assessment Test (CAT) and the Modified Medical Research Council (mMRC) dyspnea scale and post-bronchodilator (post-BD) spirometry. Materials and Methods: A prospective active case-finding study was conducted among 220 proactively selected patients with an age over 40 years and a documented history of at least one major respiratory risk factor. The study enrolled patients from one General Practitioner (GP) office. The exclusion criteria were malignancies and previously diagnosed obstructive disease. Demographics, tobacco exposure, clinical history and validated case-finding questionnaires (CAT and mMRC) were recorded. All participants underwent diagnostic post-bronchodilator spirometry. Airflow limitation was defined as a post-bronchodilator FEV1/FVC <0.70. The statistical analysis was performed with The Statistical Package for the Social Sciences version 27 (SPSS, Chicago, IL, USA). Results: Spirometry confirmed a positive COPD diagnosis in 48.2% (n = 106) of the study cohort. Severity staging revealed that 34.9% met criteria for GOLD 1 (Mild), 49.1% for GOLD 2 (Moderate), 15.1% for GOLD 3 (Severe), and 0.9% for GOLD 4 (Very Severe). Smoking history (p < 0.001) was significantly higher in the COPD group. While the mMRC scale at a cut-off ≥2 demonstrated excellent diagnostic specificity (82.5%), its low sensitivity (41.5%) means that relying solely on breathlessness in primary care questionnaires would result in missing probably more than half of the patients with a positive diagnosis. In contrast, the CAT score at a threshold ≥17 offers a more balanced trade-off (64.2% sensitivity, 74.6% specificity) for active case finding of COPD patients. Discussion: The findings of this study acknowledge the clinical utility of using validated questionnaires in active case finding of COPD in Romanian primary care. A comprehensive evaluation of symptoms-incorporating cough, sputum production, and sleep impact-provides a much more reliable clinical trigger for diagnostic spirometry than dyspnea alone. While tobacco smoking remains the predominant driver of airflow limitation in our cohort, the identification of obstruction in 4.7% of never-smokers acknowledges the clinical necessity of accounting for non-smoking risk factors, occupational dust, environmental exposures and documented histories of recurrent winter bronchitis, persistent morning cough, or unexplained sputum production. In the study cohort, a CAT score ≥17 showed the best observed balance between sensitivity and specificity; this threshold should be considered cohort-specific and requires external validation before being adopted as a universal screening cut-off. This study had limitations, including the small, single-center sample size, which may limit generalization to the Romanian population. Conclusions: The results support the implementation of a targeted active case-finding strategy in Romanian primary care. These findings support further evaluation of targeted case-finding strategies incorporating symptom burden and smoking exposure as well as algorithms like spirometry on individuals over 40 who present with a CAT score ≥ 17, or a tobacco history.
Related Concept Videos
 01:24
Chronic Obstructive Pulmonary Disease
Smoking is a primary risk factor for COPD, with over 80% of patients having a history of it. Patients typically experience progressive dyspnea or labored breathing, frequent coughing, and recurrent pulmonary infections. Many eventually succumb to respiratory failure, characterized by...
 01:27
Chronic Obstructive Pulmonary Disease-IV: Assessement and Diagnostic Studies
Medical History
 01:20
Chronic Obstructive Pulmonary Disease-I: Introduction
 01:23
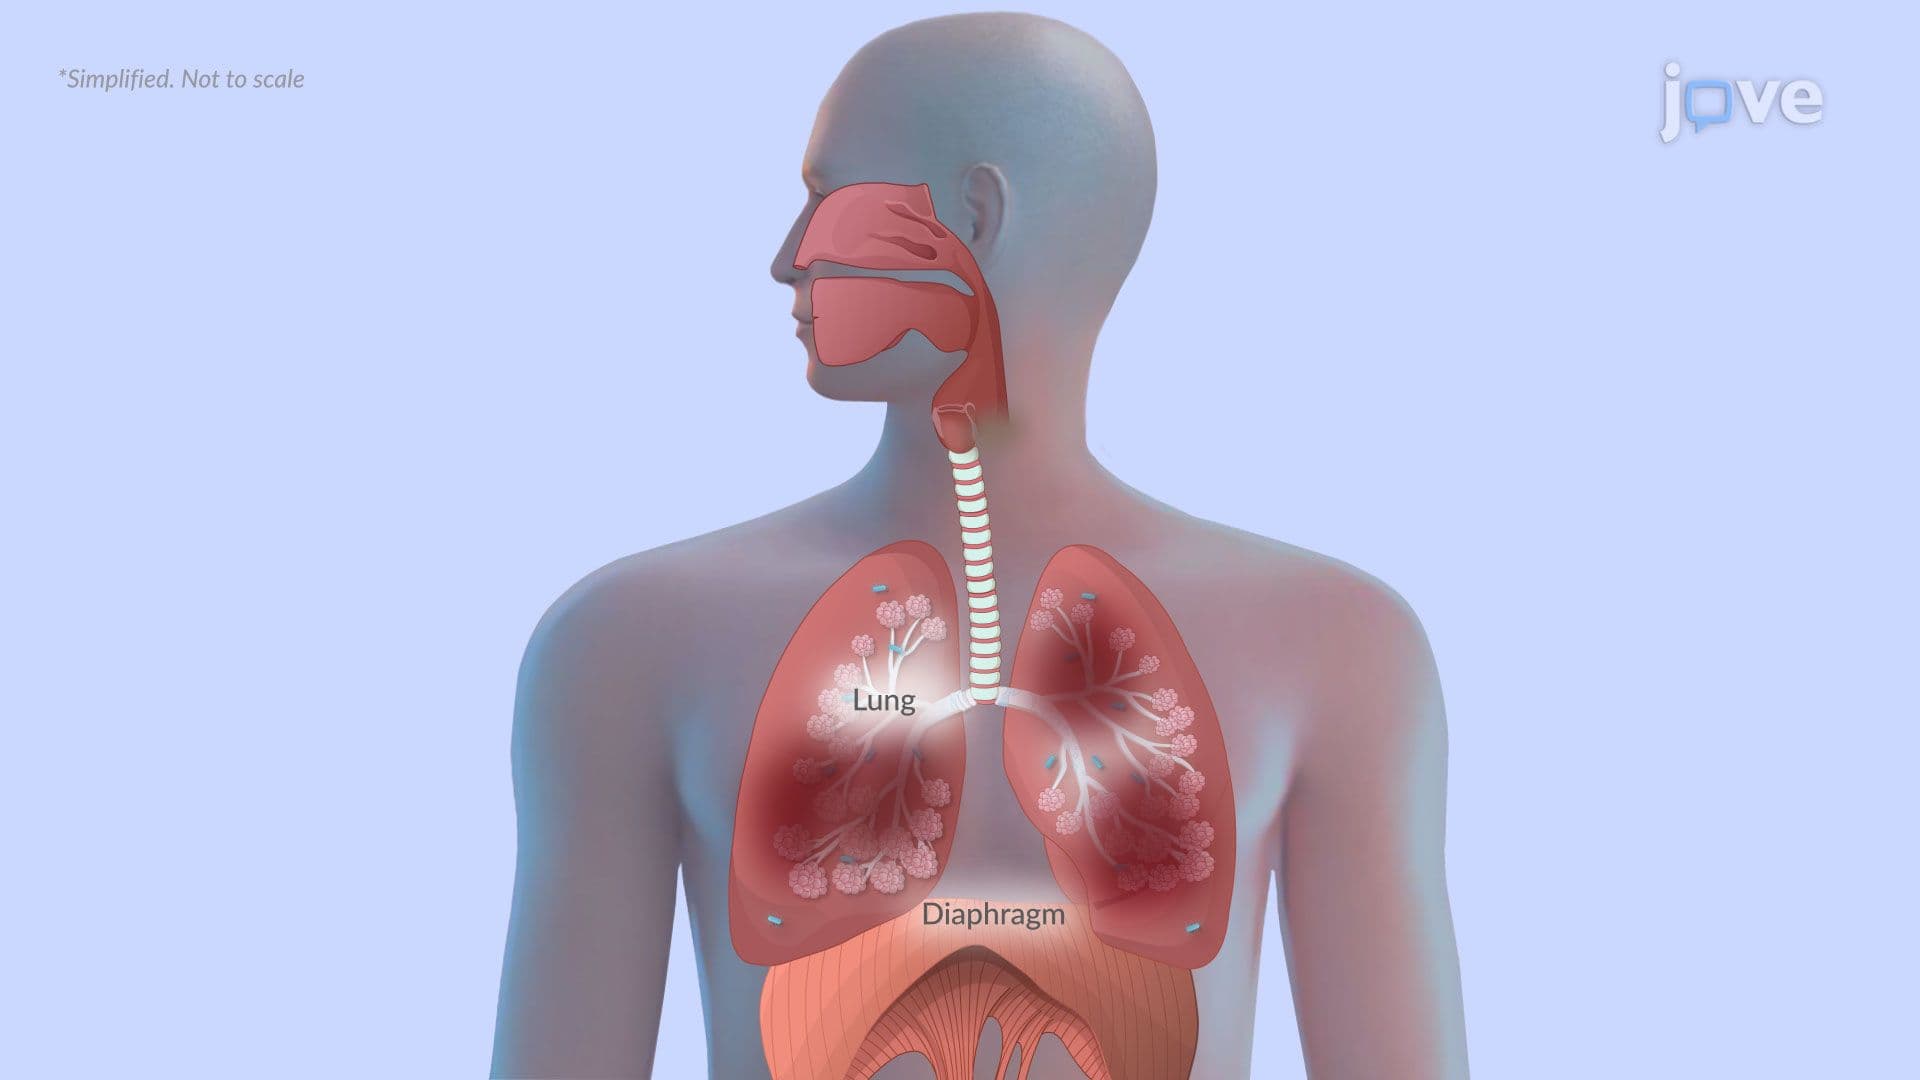
Chronic Obstructive Pulmonary Disease I: Introduction
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features
 01:19
Chronic Obstructive Pulmonary Disease IV: Clinical Manifestations