Related Experiment Video
Updated: Sep 27, 2026


Gastric Point of Care Ultrasound in Adults: Image Acquisition and Interpretation
Published on: September 22, 2023
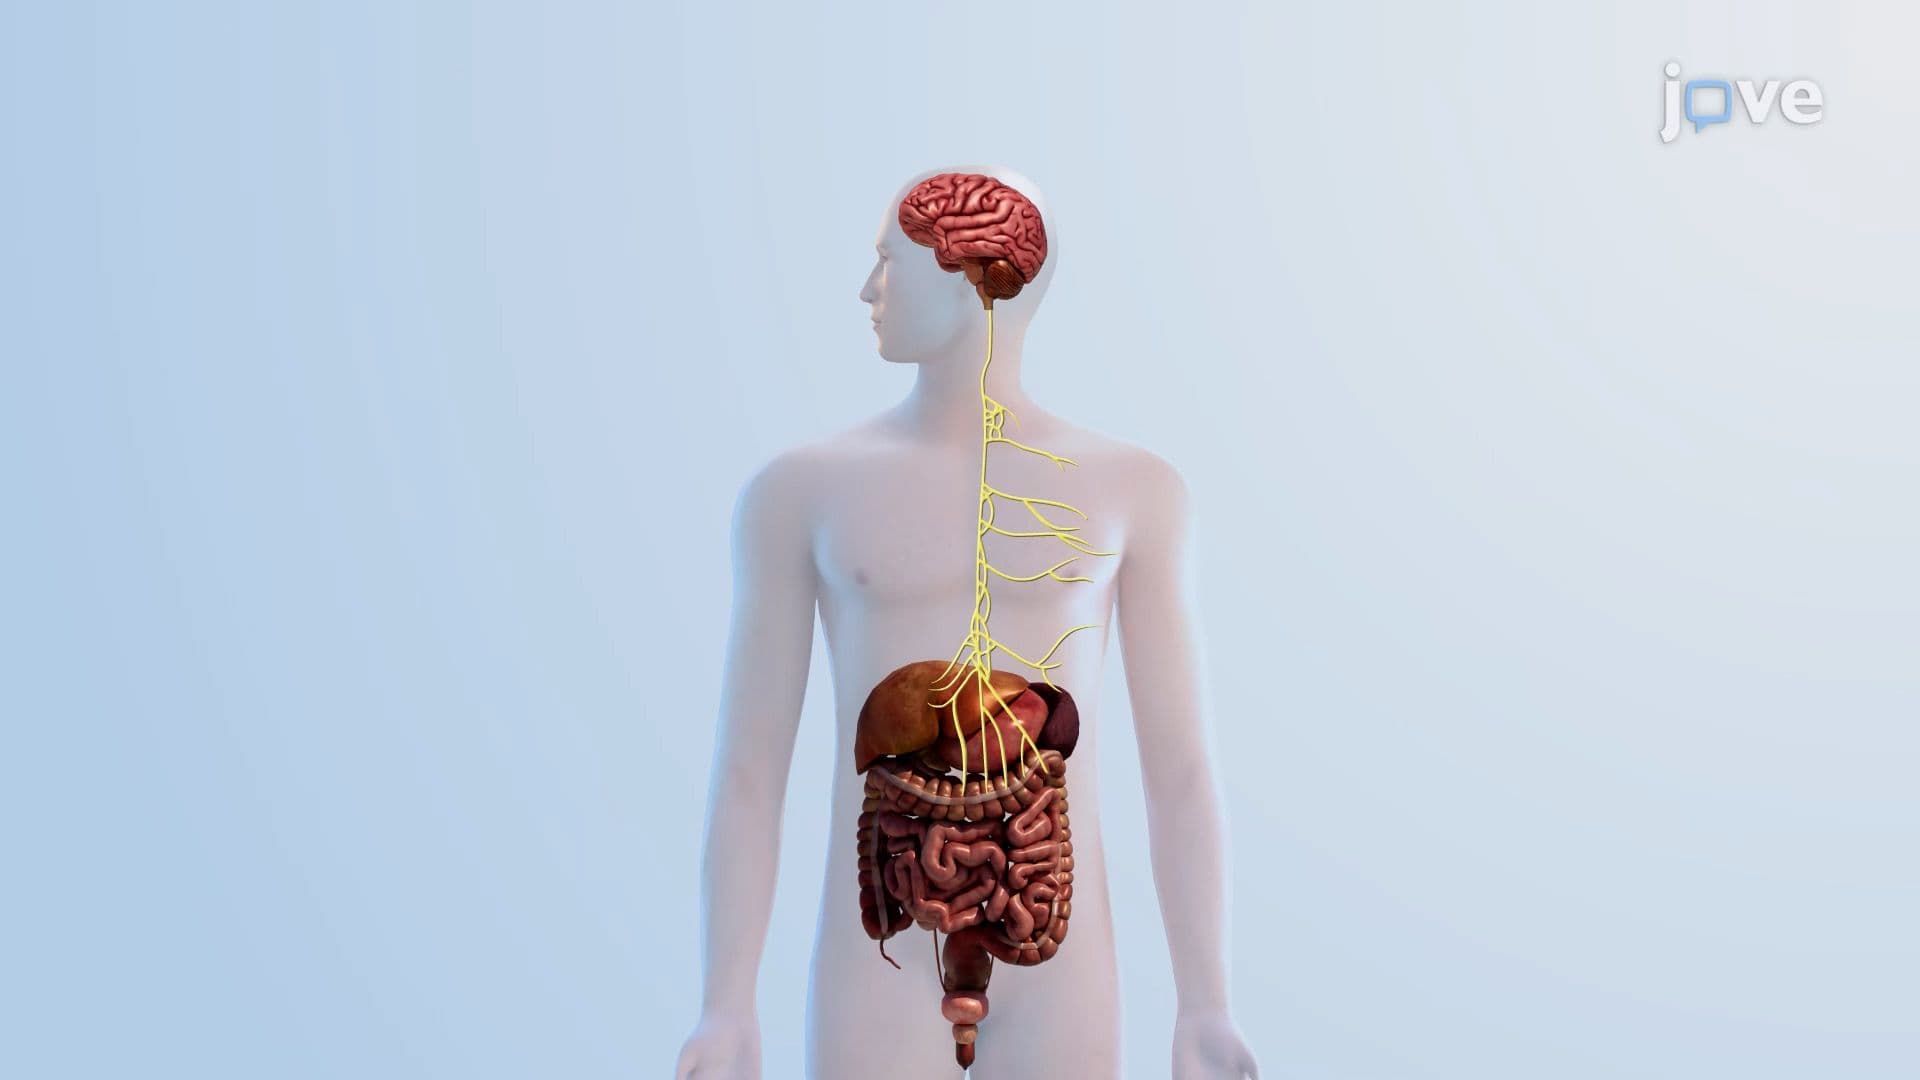
Gastric Residual Volume as a Candidate Brain-Gut Signal in Neurocritical Care: An Exploratory, Hypothesis-Generating
Geun-Hee Lee1, Jeong-Hyun Park1, Su-Min Kim1
1Department of Critical Care Medicine, Samsung Medical Center, Sungkyunkwan University School of Medicine, 81 Irwon-ro, Gangnam-gu, Seoul 06351, Republic of Korea.

Background/Objectives:
Elevated gastric residual volume (GRV) is traditionally read as feeding intolerance, and randomized trials in general intensive care units (ICUs) have discredited its routine use. Whether this holds in neurocritical patients is unknown.
Methods:
This exploratory, hypothesis-generating single-center retrospective cohort study comprised 355 neurosurgical ICU adults with documented GRV (2022-2026)-the exposure was a peak GRV ≥ 250 mL, the institutional feeding-hold threshold (n = 32). Three explanations were examined: prognosis (Firth penalized regression for in-hospital mortality), nutrition (standardized mean differences with causal mediation), and intracranial pathology (rank-based partial correlation between patient-level maxima of GRV and intracranial pressure (ICP) in the same early ICU window, plus trajectory phenotyping).
Results:
Elevated GRV was not significantly associated with in-hospital mortality (adjusted odds ratio 1.46; 95% confidence interval (CI) 0.52-3.65) and was not associated with greater deterioration in laboratory-based systemic inflammatory/nutritional indices than in comparators, with null mediation. The patient-level maxima of GRV and ICP were correlated before adjustment (ρ = 0.28) and 0.19 after full adjustment (95% CI -0.001 to 0.37, p = 0.051; 10 exposed of 109), and intracranial hypertension (ICP > 22 mmHg) occurred in 90% of exposed versus 61% of unexposed monitored patients. A high-GRV trajectory phenotype was the youngest class yet showed the most frequent intracranial hypertension, although its membership and persistence were highly sensitive to missing-data handling.
Conclusions:
In neurocritical patients receiving enteral tube feeding with documented GRV monitoring, elevated GRV was not associated with greater deterioration in laboratory-based systemic inflammatory/nutritional indices, whereas a possible association with higher early ICP was observed in a small, monitored subset. Because the ICP-monitored subset was small, these exploratory, hypothesis-generating findings do not establish a brain-gut signal. They raise the hypothesis that elevated GRV in this setting may reflect intracranial rather than solely gastrointestinal processes and require prospective confirmation with temporally paired measurements.