Related Experiment Video
Updated: Sep 28, 2026
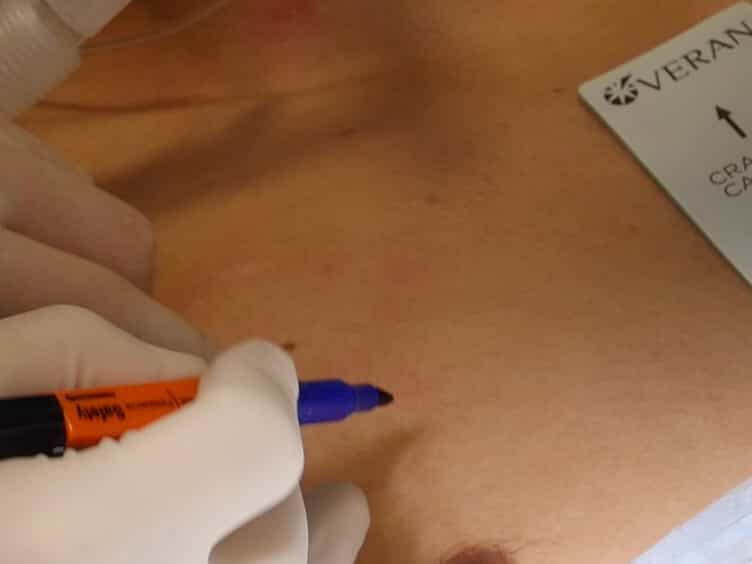

Use of Electromagnetic Navigational Transthoracic Needle Aspiration (E-TTNA) for Sampling of Lung Nodules
Published on: May 23, 2015
Is surgical lymph node assessment justified for ground glass opacity-dominant lung adenocarcinoma?
Benedikt Niedermaier1,2,3, Patric Engel1, Elizabeth Tong2,4,5
1Department of Thoracic Surgery, Thoraxklinik, Heidelberg University Hospital, Heidelberg, Germany.

Introduction:
The necessity of lymph node dissection (LND) as part of curative-intent surgery for ground-glass opacity (GGO)-dominant lung adenocarcinoma has been called into question, given the favorable prognosis and indolent behavior of these tumors. However, the oncological safety of omitting LND in cases of GGO-dominant lung adenocarcinoma remains controversial, and current guidelines continue to recommend it.
Methods:
This study was designed as a retrospective, single-center cohort study. Patients with cT1N0M0 lung adenocarcinoma who underwent surgical resection between 2010 and 2023 were categorized as GGO-dominant or solid-dominant cohorts based on consolidation-to-tumor ratios in preoperative computed tomography scans. The primary endpoint was the incidence of occult lymph node (LN) metastasis.
Results:
A total of 726 consecutive patients were included in this study, categorized as GGO-dominant in 50 patients and solid-dominant in 676 patients. GGO-dominant tumors were more frequently observed in female patients (p = 0.03), whereas no significant differences were found between the groups with respect to age, smoking status, or ECOG performance status. GGO-dominant morphology was associated with lower pT stage and lower rates of pleural and lymphovascular invasion. The incidence of occult LN metastasis was 4% (n=2) in the GGO-dominant cohort and 11.8% (n=80) in solid-dominant cohort. Only solid tumor size was a significant predictor of occult LN metastasis in multivariable logistic regression (OR 1.39 per 5mm increase, 95% CI 1.10-1.77, p = 0.006). Survival analysis revealed a higher rate of freedom from recurrence (p = 0.04) and favorable trends in overall survival (p = 0.09) and recurrence-free survival (p = 0.086) in the GGO-dominant cohort.
Conclusions:
The hypothesis that GGO-dominant morphology reliably predicts negative lymph node involvement was not confirmed. These findings support the continued role of surgical nodal assessment for accurate pathological staging.