Related Experiment Video
Updated: Sep 28, 2026


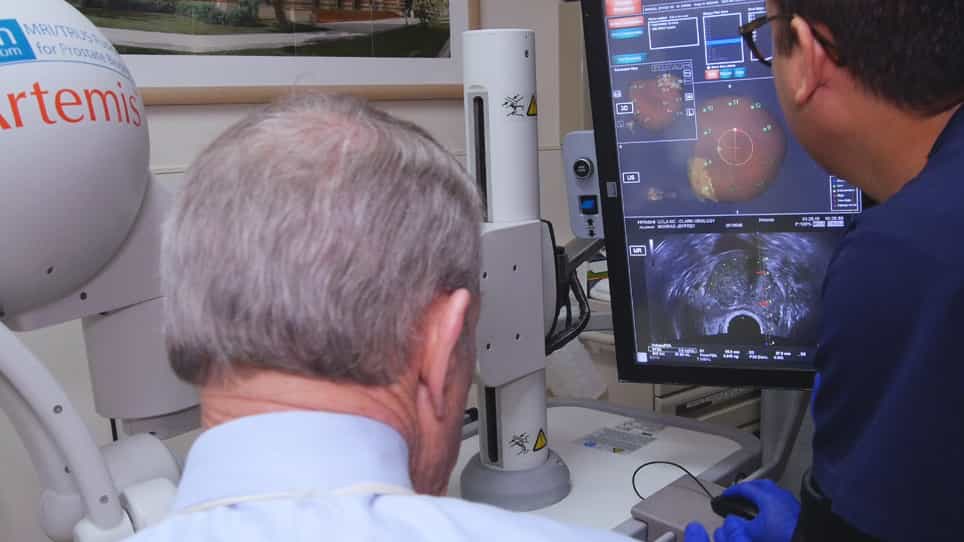
A Cognitive Fusion-guided Prostate Biopsy Using Multiparametric Magnetic Resonance Imaging and Transrectal Ultrasound
Published on: March 21, 2025
Incremental Value of Transrectal Ultrasound Target Visibility Beyond Clinical and MRI Variables for Predicting
Xiubin Tang1, Ming Chen1, Youhai Wu2
1Department of Ultrasound, Zhangzhou Affiliated Hospital of Fujian Medical University (Zhangzhou Municipal Hospital of Fujian Province), No. 59 Shengli West Road, Xiangcheng District, Zhangzhou, Fujian 363000, China.

Purpose:
To determine whether three-level transrectal ultrasound (TRUS) target visibility adds predictive information beyond clinical and magnetic resonance imaging (MRI) variables for patient-level biopsy-detected clinically significant prostate cancer (csPCa).
Materials And Methods:
This retrospective two-center study included 2,700 men undergoing cognitive transperineal biopsy. Center A provided development (n = 1,642) and temporal validation (n = 565) cohorts, and Center B provided external validation (n = 493). Gradient-boosting models were evaluated. TRUS visibility was retrospectively classified from contemporaneous biopsy-planning materials by readers blinded to pathology. Performance was assessed using AUC, average precision (AP), Brier score, quantitative calibration, exploratory decision-curve analysis, and interobserver reproducibility.
Results:
Adding visibility to the Clinical-MRI model produced modest but consistent improvement. In temporal validation, ΔAUC was 0.039 (95 % CI, 0.021-0.058), ΔAP 0.074 (0.034-0.116), and ΔBrier score - 0.016 (-0.023 to - 0.009); corresponding external differences were 0.023 (0.009-0.037), 0.045 (0.014-0.075), and - 0.016 (-0.023 to - 0.008). Calibration intercept/slope for the visibility model were - 0.074/1.160 temporally and 0.316/1.304 externally. Visibility-specific csPCa gradients were preserved in both validation cohorts, with no evidence of center-by-visibility heterogeneity. Interobserver agreement was high (linear-weighted Cohen's κ = 0.82).
Conclusion:
TRUS target visibility provides modest incremental post-TRUS risk information beyond clinical and MRI variables. Because csPCa was defined at the patient level from targeted or systematic cores, the observed association cannot distinguish lesion biology from improved localization or sampling. Its potential role is risk refinement and sampling assistance, not biopsy avoidance or evidence of causal benefit.