Related Experiment Video
Updated: Sep 29, 2026
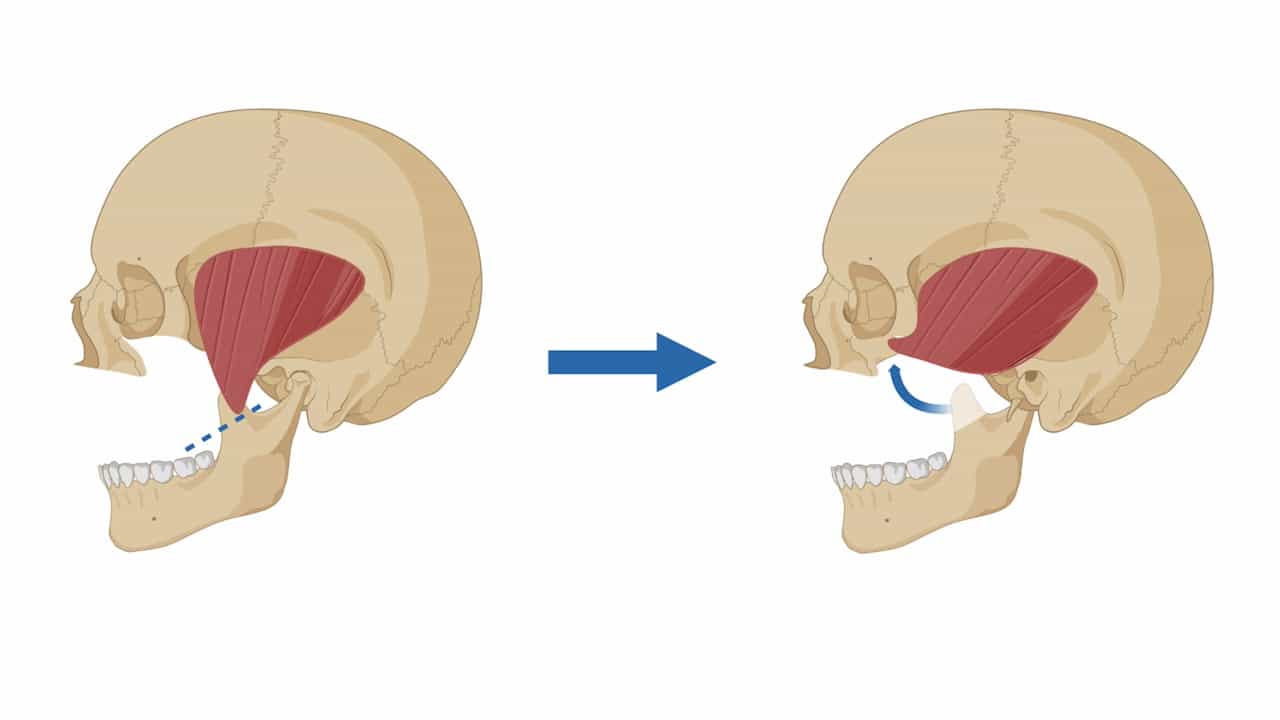

Coronoid-Temporalis Pedicled Flap for Orbital Floor Defect Reconstruction
Published on: December 5, 2025
Bone-Preserving Management of Maxillary Cemento-Ossifying Fibroma With Orbital Floor Thinning: A Case Report
Francisco Javier Cano Palacios1, Jael B Gomez Cabrales2, Sergio Morales Acosta3
1General Surgery, Hospital Regional "Dr. Manuel Cárdenas de la Vega, Instituto de Seguridad y Servicios Sociales de los Trabajadores del Estado (ISSSTE), Culiacán, MEX.

Abstract:
Cemento-ossifying fibroma (COF) is a benign fibro-osseous neoplasm that most often affects the mandible and occurs predominantly in women during the third and fourth decades of life. Maxillary involvement is less common and may remain minimally symptomatic while expanding into the maxillary sinus. We present a 26-year-old woman with a six-month history of progressive right midface enlargement without pain, nasal obstruction, diplopia, visual symptoms, or dental mobility. Computed tomography demonstrated a well-circumscribed expansile right maxillary lesion measuring 44.9 × 42.5 × 31.9 mm, occupying a substantial portion of the maxillary sinus and extending toward a thinned but radiologically intact orbital floor. A preoperative incisional biopsy showed a fibrocellular spindle-cell stroma with cementum-like mineralized deposits, supporting the diagnosis of conventional COF. Through a Weber-Ferguson approach, the encapsulated lesion demonstrated a favorable cleavage plane and underwent macroscopically complete enucleation with peripheral osteotomy while preserving the orbital floor and residual maxillary bone. Immediate reconstruction was not required. At approximately three months of follow-up, wound healing remained satisfactory without infection, dehiscence, ectropion, alar retraction, visual symptoms, or other functional complications. Infraorbital hypoesthesia persisted as the only postoperative neurologic finding. Follow-up computed tomography was reviewed by the treating surgical team and demonstrated postoperative changes without a discrete residual or recurrent expansile lesion. This case highlights the importance of individualized intraoperative assessment of lesion boundaries and remaining structural support when considering a bone-preserving strategy. Although the early clinical and radiologic outcomes were favorable, the limited follow-up precludes conclusions regarding long-term recurrence, structural stability, or definitive sensory recovery.