Related Experiment Video
Updated: Sep 29, 2026


Multiplex Therapeutic Drug Monitoring by Isotope-dilution HPLC-MS/MS of Antibiotics in Critical Illnesses
Published on: August 30, 2018
Model-Informed Ceftazidime-Avibactam Dosing Stratified by Renal Function and Renal Replacement Therapy Status in
Juan Hu1, Chu-Hui Wang2, Xiao-Juan Wang3
1Intensive Care Unit, The First Affiliated Hospital, Zhejiang University School of Medicine, Hangzhou, People's Republic of China.

Introduction:
Carbapenem-resistant organisms (CROs) threaten critically ill patients, requiring model-informed ceftazidime-avibactam (CAZ-AVI) dosing by renal function and renal replacement therapy (RRT) status.
Materials And Methods:
Thirty-three patients were prospectively enrolled at one center (18 RRT; 15 non-RRT). RRT settings were recorded. Samples were collected at 0, 1, 2, 4, 6, and 8 h after first-dose and steady-state infusions. Population pharmacokinetic modeling used NONMEM. Monte Carlo simulations evaluated joint probability of target attainment (PTA) for minimum inhibitory concentration (MIC)-directed therapy and pathogen-specific cumulative fraction of response (CFR) for empirical therapy using BRICS MIC distributions under two targets: (1) CAZ 100% fT > MIC and AVI 100% fT > 1 mg/L; and (2) CAZ 50% fT > 4MIC and AVI 50% fT > 1 mg/L. Robust model-informed regimens required joint PTA ≥90% under both targets for MIC-directed therapy and CFR ≥90% under both for empirical therapy; lower values were exploratory.
Results:
We analyzed 211 blood samples (120 RRT; 91 non-RRT). Creatinine clearance (CrCL) was retained in the final non-RRT models, whereas no covariate was retained in the final RRT models. RRT-model clearance (CL)/volume of distribution (Vd) estimates were 2.03 L/h/17.0 L for CAZ and 1.77 L/h/14.0 L for AVI; non-RRT estimates were 3.36 L/h/20.5 L and 4.27 L/h/16.0 L, respectively. At MICs ≤8 mg/L, robust model-informed regimens included 2000/500 mg q6h for augmented renal clearance and 2000/500 mg q12h during RRT. For CFR-based empirical therapy during RRT, robust model-informed regimens were 2000/500 mg q12h for carbapenem-resistant Klebsiella pneumoniae (CRKP) and 2000/500 mg q8h for carbapenem-resistant Pseudomonas aeruginosa (CRPA).
Conclusion:
Our study describes the pharmacokinetics of CAZ-AVI in critically ill patients and provides model-informed dosing regimens stratified by renal function and RRT status for both empirical and targeted therapy. Larger, multicenter prospective studies are warranted to validate these findings.
Related Concept Videos
 01:25
Drug Dosing in Renal Diseases: Dose Adjustments Based on Drug Clearance and Elimination Rate Constant
 01:11
Renal Failure: Dose Adjustments
Reduced renal clearance and elimination rate are common outcomes of renal impairment. These alterations lead to a prolonged elimination half-life and an altered apparent volume of distribution for drugs. As a result, dosage adjustments are typically necessary to maintain optimal drug levels in the body.
However, dosage adjustments...
 01:15
Determination of Multiple Dosing Parameters: Steady-State, Minimum and Maximum Concentrations
 01:20
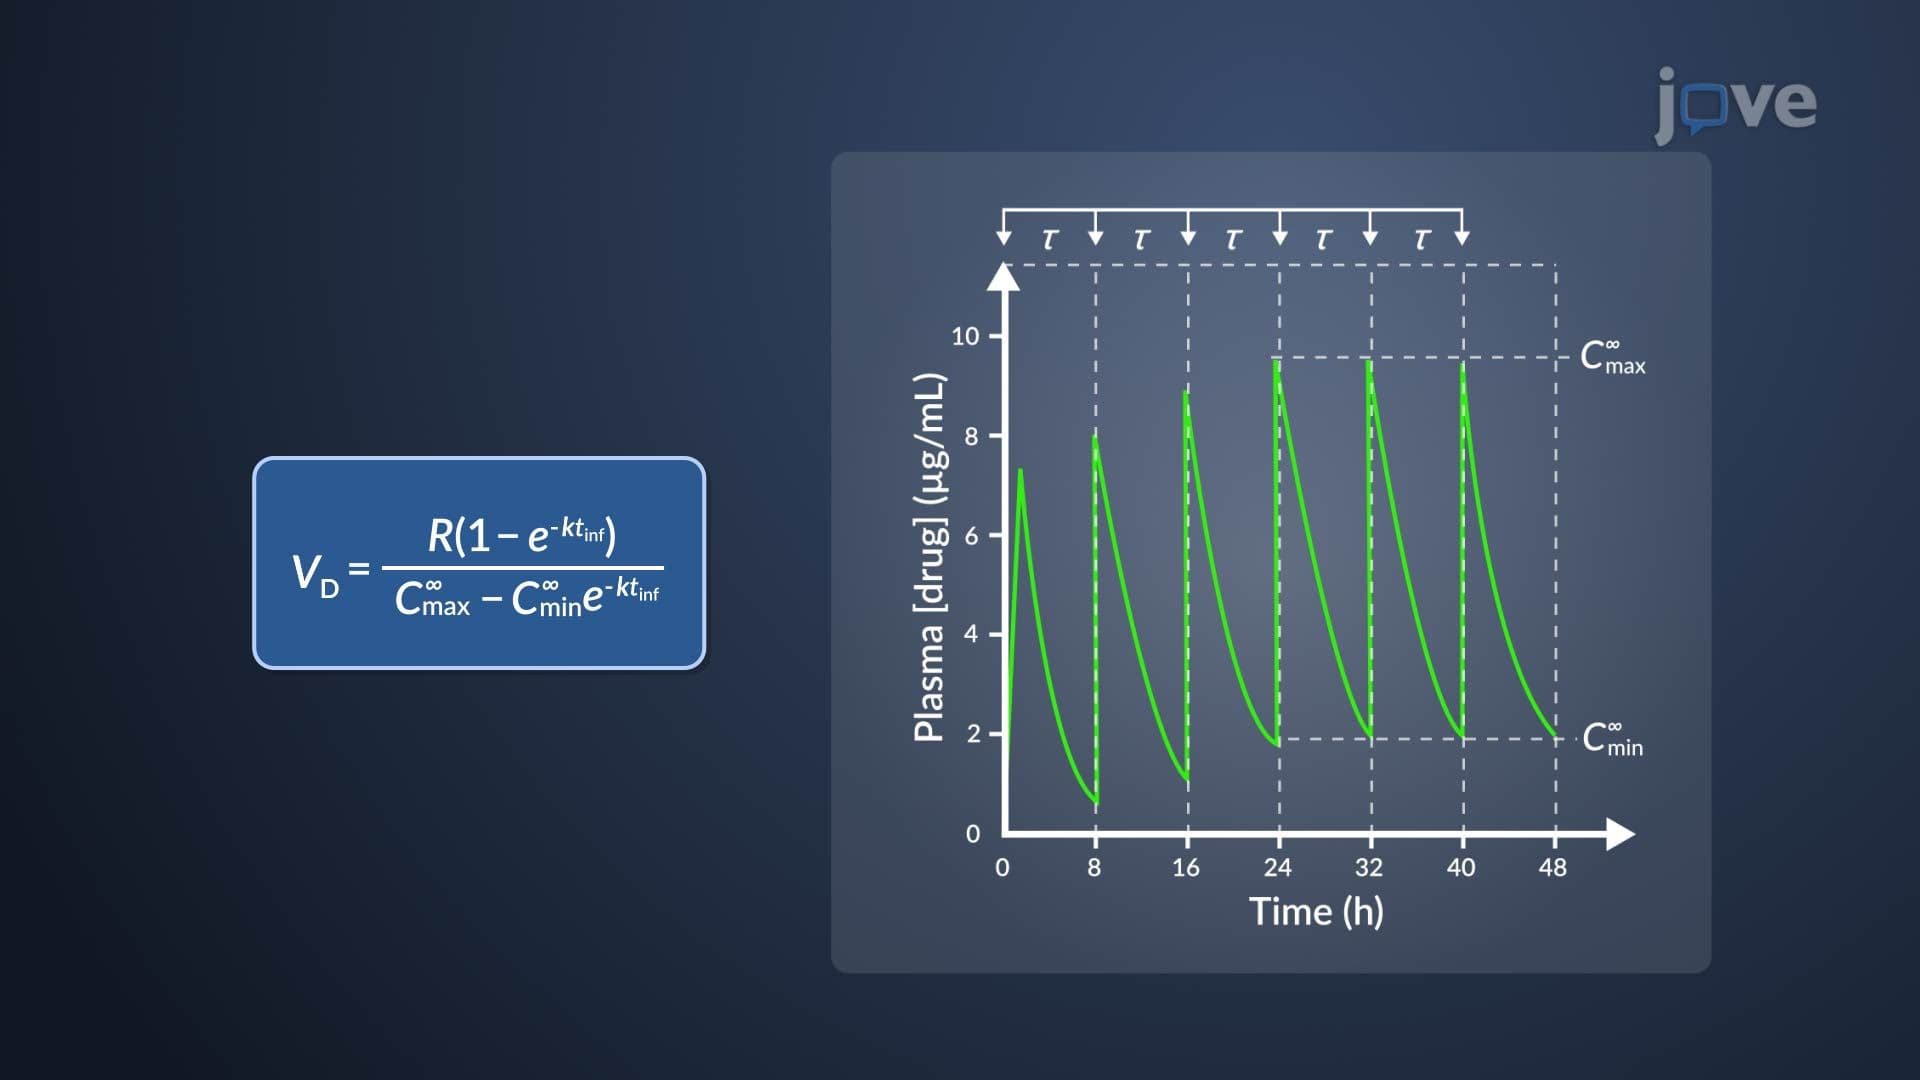
Estimation of k and VD of Aminoglycosides
 01:26
Extracorporeal Removal of Drugs: Continuous Renal Replacement Therapy
 01:30
Continuous Renal Replacement Therapy