Related Experiment Video
Updated: Sep 29, 2026
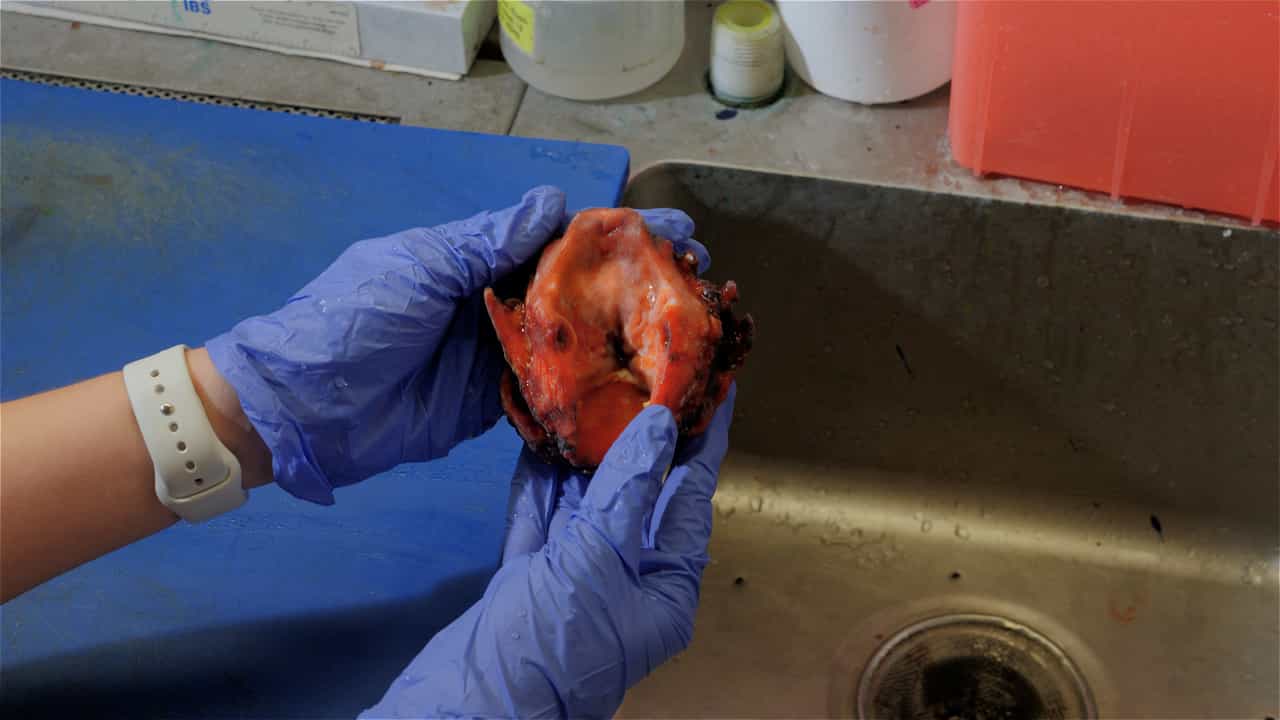

Enhanced Communication of Tumor Margins Using 3D Scanning and Mapping
Published on: December 15, 2023
Experiences of Shared Decision Making for Cancer Screening Among Deaf, DeafBlind, and Hard of Hearing Adults
Emmanuel Perrodin-Njoku1, Erika Bergeron1, Poorna Kushalnagar1
1Center of Deaf Health Excellence, Gallaudet University, Washington, DC, USA.

Abstract:
IntroductionDeaf, DeafBlind, and hard of hearing (DDBHH) adults using American Sign Language (ASL) face persistent disparities in cancer screening adherence, compounded by systemic communication barriers and documented deficits in shared decision making (SDM) with health care providers. Community health navigators (CHNs) who are fluent in ASL have been proposed as a strategy to bridge these gaps. This study explores 1) how ASL-using CHNs contributed or did not contribute to SDM for cancer screening among DDBHH adults who were nonadherent to screening recommendations and 2) identified factors influencing screening decisions in this population.MethodsA nested qualitative study from June to July 2025 with semi-structured exit interviews was conducted in ASL via videoconferencing with 15 DDBHH adults within a randomized clinical trial to address routine cancer screening adherence, all of who had completed closeout at the time of the interviews. Directed content analysis was applied using an a priori codebook organized around four domains: background and screening context, cancer knowledge, provider engagement and SDM, and navigator role.ResultsProvider communication about cancer screening was brief and directive; formal risk-benefit discussions were largely absent. Intervention participants described self-directed decision-making, greater pre-appointment knowledge, and higher confidence, whereas SOC participants more commonly described deferring to provider recommendations without deliberation. Video remote interpreting (VRI) access limitations were a near-universal barrier to meaningful shared decision-making. CHNs sharing a DDBHH identity were described as important to building trust and supporting participants' screening engagement and decision-making.ConclusionASL-fluent CHNs with shared DDBHH identity supported DDBHH patients in approaching cancer screening with greater self-perceived preparedness and self-efficacy. However, structural barriers, including inadequate interpreter access and insufficient provider training, are significant reported obstacles to shared decision-making. Integrating ASL-using navigators into cancer screening programs, alongside systemic improvements in communication access and medical education, remain promising approaches to improve cancer screening experiences for DDBHH populations.
