Related Experiment Video
Updated: Sep 29, 2026
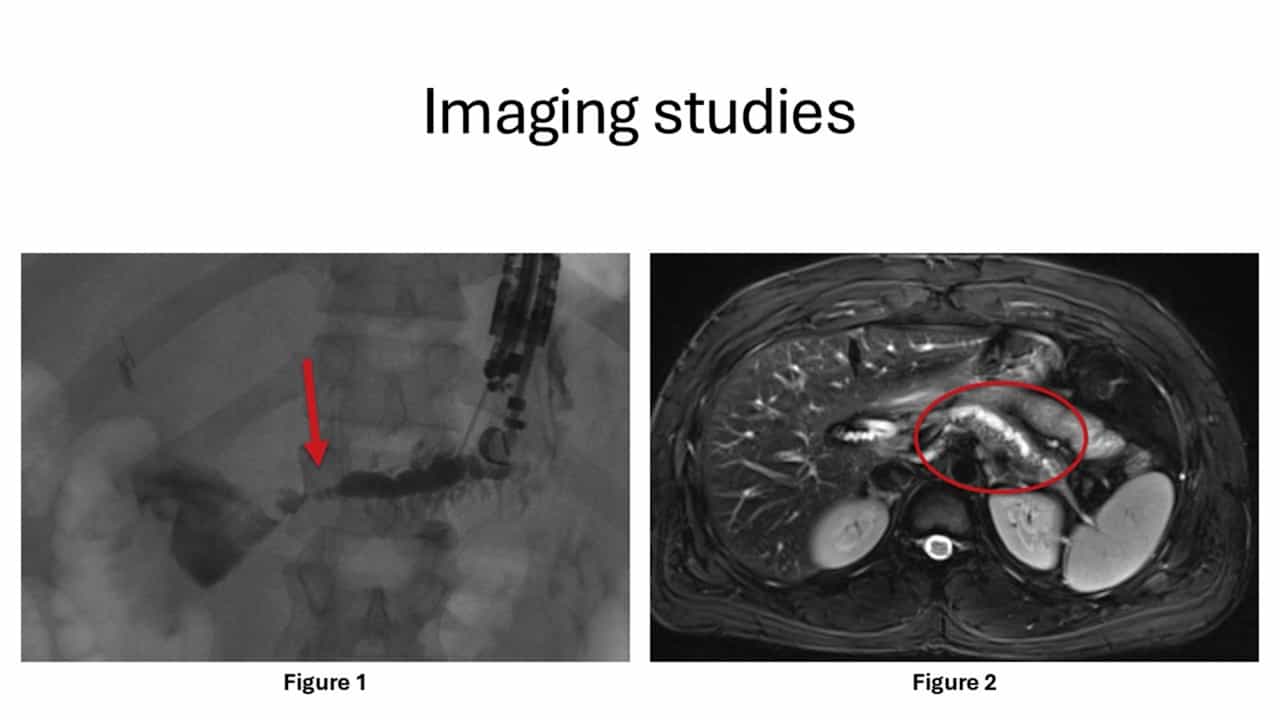

Robotic-assisted Lateral Pancreaticojejunostomy for Chronic Pancreatitis
Published on: September 5, 2025
Bailout Procedures, Downstream Outcomes, and Cost After Robotic vs Laparoscopic Cholecystectomy for Acute
Stephanie Yu1, Dillon Cheung1, Chee-Chee Stucky1
1Department of Surgery, Mayo Clinic Arizona, Phoenix, AZ.

Background:
Robotic cholecystectomy use is increasing, but comparisons with laparoscopic cholecystectomy have largely excluded bailout procedures, limiting assessment of difficult acute cholecystitis. We compared bailout use, downstream outcomes, and 1-year costs between approaches.
Study Design:
This retrospective cohort study used Healthcare Cost and Utilization Project databases from New York and Florida (2012-2021) to identify adults undergoing inpatient, unscheduled robotic or laparoscopic cholecystectomy for acute cholecystitis. Bailout included conversion to open, subtotal cholecystectomy, or cholecystostomy tube placement. Multilevel regression evaluated bailout, and postoperative outcomes were assessed through 1 year.
Results:
Among 384,617 patients, 4% underwent robotic and 96% laparoscopic cholecystectomy. Robotic cholecystectomy had higher bailout rates (1.7% vs 1.4%; adjusted OR 1.38, 95% CI 1.21-1.58), including higher odds of conversion to open (OR 1.61, 95% CI 1.28-2.03) and subtotal cholecystectomy (OR 2.02, 95% CI 1.68-2.43), but lower odds of cholecystostomy tube placement (OR 0.42, 95% CI 0.28-0.62). Bile duct injury rates were similar (1.6% for both; p=0.998). Among 5,448 patients requiring bailout, robotic cholecystectomy was associated with fewer postoperative endoscopic biliary (3.1% vs 7.7%; p=0.007) and surgical interventions (2.3% vs 7.5%; p=0.002). Median 1-year cumulative costs remained higher with robotic cholecystectomy ($29,702 vs $24,483; p=0.002).
Conclusions:
Robotic cholecystectomy was associated with marginally higher bailout use and similar bile duct injury rates but fewer downstream interventions after bailout. These potential benefits did not offset higher 1-year costs.
