Related Experiment Video
Updated: Sep 30, 2026
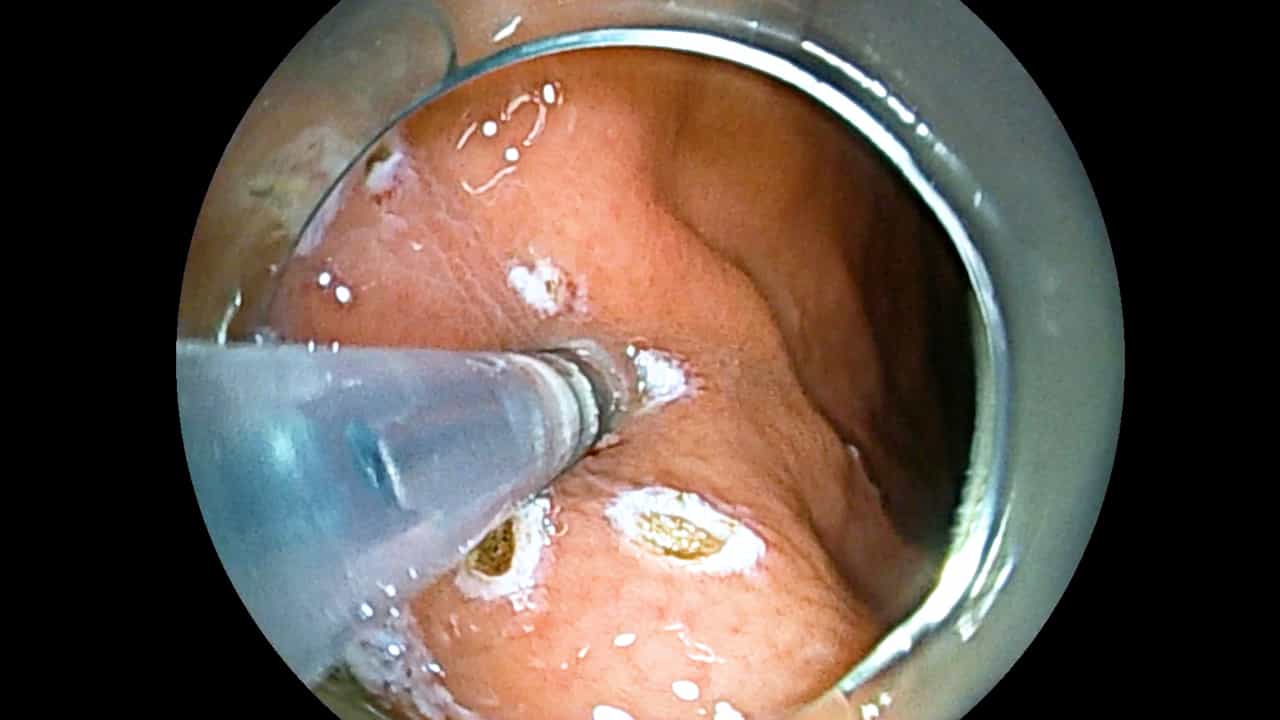

Evaluation of the Effectiveness of Longitudinal Incision for Endoscopic Submucosal Excavation of Gastric Subepithelial Lesions
Published on: April 28, 2026
Emergency Surgery for Diverticulitis: Does the Number of Days From Admission to Surgery Matter?
Roseanna Presutti1, Allison J Pang1, Nancy Morin1
1Division of Colon and Rectal Surgery, Jewish General Hospital, McGill University, Montreal, Quebec, Canada.

Introduction:
This study evaluated the association between time from hospital admission to surgery and the use of minimally invasive surgery (MIS) and primary anastomosis in emergency surgery for acute diverticulitis.
Methods:
This was a multicenter observational study using prospectively collected American College of Surgeons National Surgical Quality Improvement Program data from 2012 to 2022. Adult patients who underwent emergency left-sided colectomy for acute diverticulitis were included. The primary exposure was the number of days from hospital admission to surgery, categorized as early (0-1 d), subacute (2-4 d), and late (≥5 d). Outcomes included an MIS approach, primary anastomosis (with or without diversion), 30-d major morbidity, return to the operating room, and mortality. Multivariate logistic regression and sensitivity analyses excluding patients with preoperative septic shock were performed.
Results:
Among 13,827 patients, 71.3% underwent early surgery, 18.6% underwent subacute surgery, and 10.2% underwent late surgery. Patients were similar in median age (62.0, 60.0, and 63.0 y; P = 0.17) but differed in the proportion of female sex (49.6%, 48.5%, and 54.3%; P = 0.002) and American Society of Anesthesiologists score III/IV (66.3%, 66.8%, and 73.8%; P < 0.001). The use of MIS (11.0%, 14.1%, and 17.1%; P < 0.001) and primary anastomosis (26.1%, 29.5%, and 32.4%; P < 0.001) was higher with later surgery. After adjustment, patients who had later surgery had higher odds of MIS (subacute: adjusted odds ratio [aOR] 1.26, 95% confidence interval [CI] 1.10-1.43; late: aOR 1.57, 95% CI 1.33-1.86) and primary anastomosis (subacute: aOR 1.11, 95% CI 1.01-1.22; late: aOR 1.26, 95% CI 1.11-1.44). However, 30-d postoperative major morbidity (23.6%, 27.8%, and 32.6%; P < 0.001) and mortality (3.8%, 3.3%, and 6.4%; P < 0.001) were highest among patients undergoing late surgery.
Conclusions:
Delayed emergency surgery for diverticulitis was associated with higher rates of MIS and/or primary anastomosis and increased 30-d postoperative morbidity and mortality.

Related Concept Videos
 01:29
Appendicitis-II: Diagnostic Studies and Management
Diagnosing Appendicitis
It requires a multifaceted approach, starting with a detailed physical examination to pinpoint the location and nature of the pain and identify any associated symptoms. Laboratory tests play a crucial role. A complete Blood Count (CBC) typically reveals leukocytosis (an increased number of...
 01:26
Endoscopic Procedures IV: Sigmoidoscopy and Laproscopy
Sigmoidoscopy
Sigmoidoscopy is a diagnostic procedure that uses a flexible sigmoidoscope equipped with a light source and camera to examine the rectum and sigmoid colon. The procedure involves inserting the tube through the anus...
 01:27
Diverticular Disease of the Colon
 01:25
Endoscopic Procedures II: Colonoscopy
 01:21
Inflammatory Bowel Disease V: Surgical Management
Here are some common surgical interventions for IBD:
 01:22
Aneurysm IV: Nursing Management