Related Experiment Video
Updated: Sep 30, 2026


Analyses of Proteinuria, Renal Infiltration of Leukocytes, and Renal Deposition of Proteins in Lupus-prone MRL/lpr Mice
Published on: June 8, 2022
High complement activation index predicts renal progression in crescentic IgA nephropathy
Jingjing Wang1, Ling Jiang1, Yuhui Luo2
1National Clinical Research Center for Kidney Diseases, Jinling Hospital, Affiliated Hospital of Medical School, Nanjing University, Nanjing, China.

Background:
Crescentic immunoglobulin A nephropathy (IgAN) with Oxford C2 lesions (≥25% crescents) represents a severe disease phenotype. Individual complement markers show inconsistent prognostic value. We developed a composite Complement Activation Index (CAI) and tested its association with renal progression.
Methods:
This study enrolled 157 biopsy-confirmed patients with crescentic IgAN. The CAI was derived from four components: (i) urinary C3 > 2.8mg/L, (ii) serum C3 < 0.80 g/L, (iii) glomerular C3 immunofluorescence intensity ≥ 2+, and (iv) presence of glomerular C1q deposition. Each component contributed 1 point, categorizing patients into low- CAI and high- CAI groups. The association between CAI and the composite kidney disease progression event, defined as doubling of serum creatinine or end-stage renal disease, was assessed using Cox proportional hazards models.
Results:
A high CAI (43.9%, 69/157) was associated with worse baseline renal function (eGFR 39 vs. 65 mL/min/1.73 m², P<0.001), higher proteinuria (4.6 vs. 2.3 g, P<0.001), and more advanced tubulointerstitial injury. Over a median follow-up of 34.1 months, 44 patients (28.0%) reached the composite endpoint. High CAI independently predicted adverse outcomes (adjusted HR 2.58, 95% CI 1.15-5.80, P = 0.022), with each 1-point increase associated with an 87% higher risk (HR 1.87, 95% CI 1.10-3.20, P = 0.021). Adding CAI to the Oxford MEST model improved time-dependent AUC at 36 months (0.79 vs. 0.75, ΔAUC 0.04, 95% CI -0.02 to 0.12).
Conclusion:
Higher CAI was independently associated with renal progression in crescentic IgAN. As an exploratory composite index, CAI may complement existing pathological risk stratification, but its incremental clinical utility requires prospective validation.
Related Concept Videos
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:22
Acute Kidney Injury I: Introduction
 01:29
Acute Kidney Injury III: Clinical Manifestations
 01:26
Nephrotic Syndrome II : Assessment and Medical Management
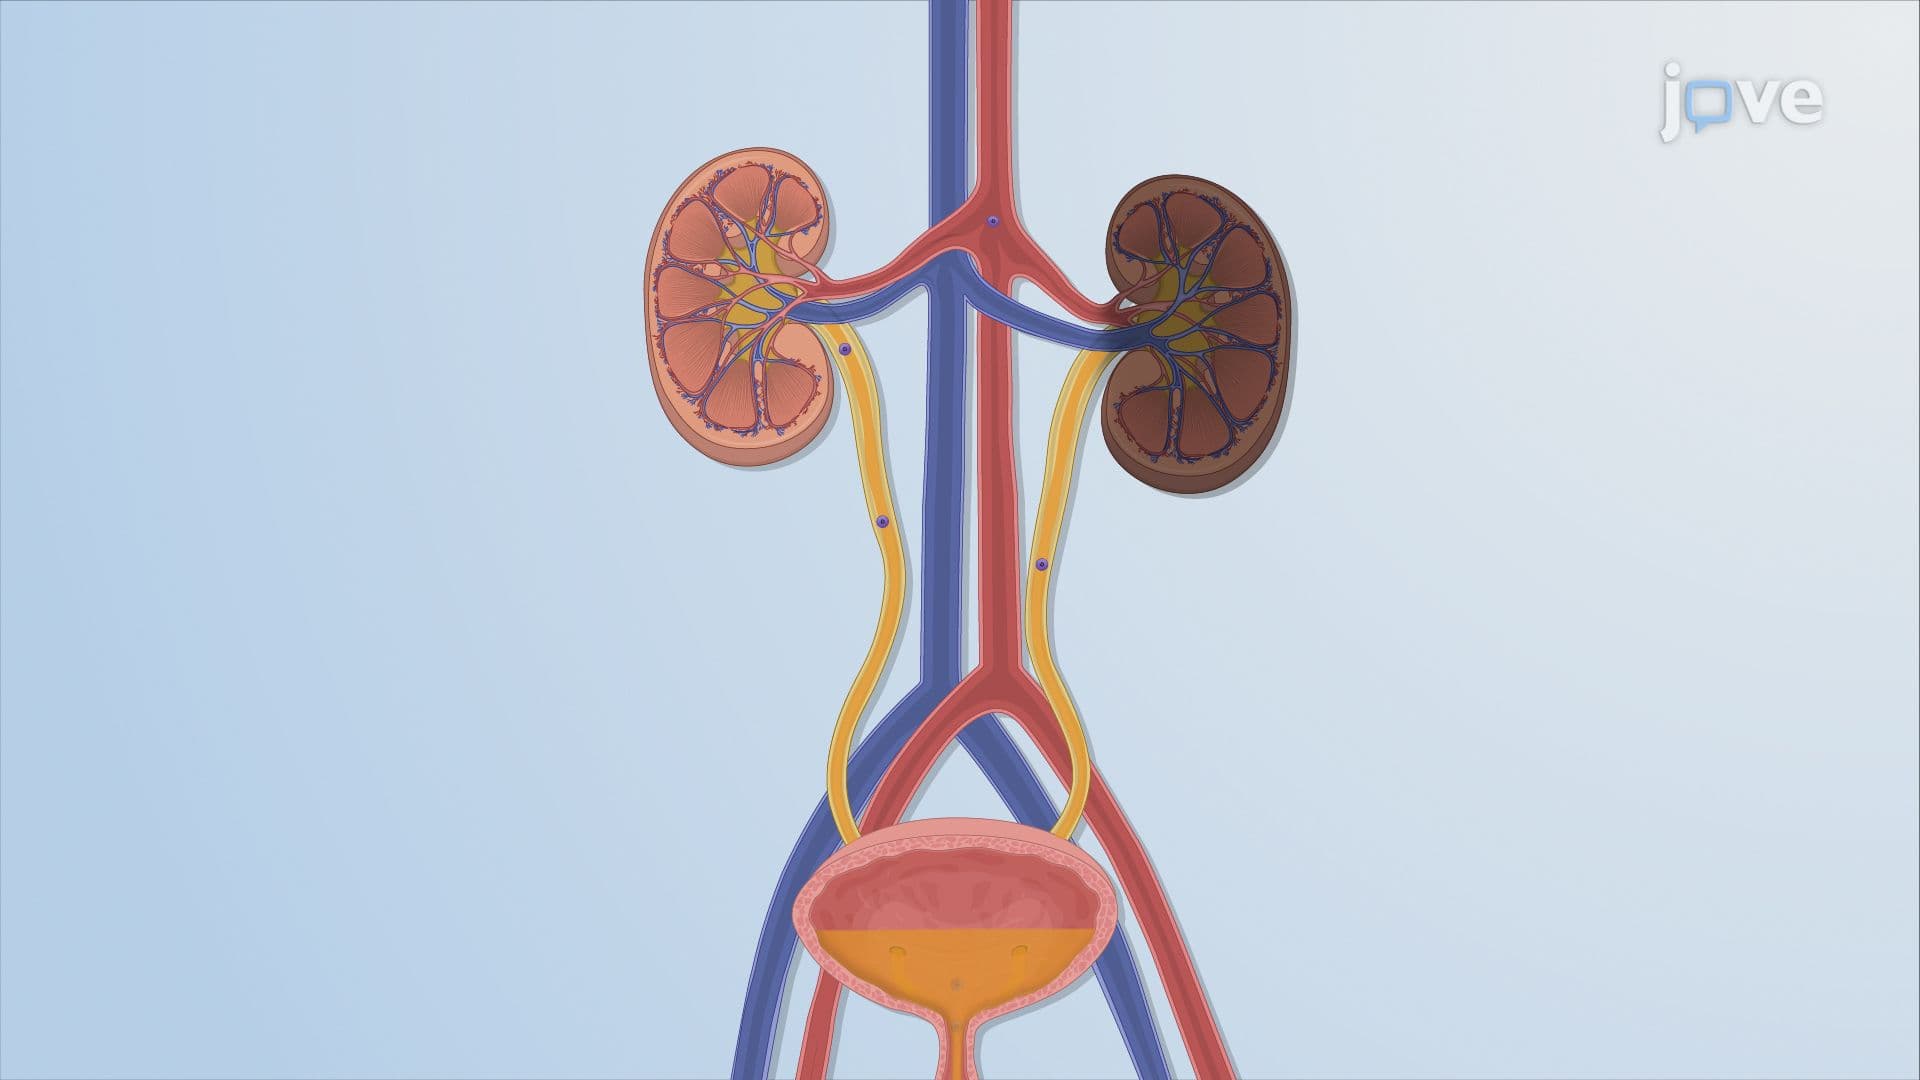 01:25
Drug Dosing in Renal Diseases: Measurement of Glomerular Filtration Rate
 01:28
Diabetic Nephropathy