Related Experiment Video
Updated: Oct 1, 2026


An Ivor Lewis Esophagectomy Designed to Minimize Anastomotic Complications and Optimize Conduit Function
Published on: April 17, 2020
Impact of hypercontractile esophagus on clinical and physiologic outcomes after antireflux surgery: a matched-control
Emma Venard1, Vineeth R Sadda1, Ahmed E Aly1
1Foregut Division, Surgical Institute, Allegheny Health Network, Pittsburgh, PA, United States; Chevalier Jackson Esophageal Research Center, Western Pennsylvania Hospital, Allegheny Health Network, Pittsburgh, PA, United States.

Background:
Hypercontractile esophagus is a motility disorder defined by ≥20% of swallows with a distal contractile integral (DCI) > 8000 mmHg·cm·s on high-resolution manometry. Although hypercontractility has been associated with gastroesophageal reflux disease (GERD), its impact on outcomes after antireflux surgery (ARS) and on postoperative esophageal physiology remains unclear.
Methods:
Patients undergoing primary ARS from 2014 to 2023 with hypercontractile esophagus were identified from a prospectively maintained database and matched 1:2 to controls without hypercontractility by age, sex, and procedure type. Symptom outcomes, objective reflux control, and postoperative manometric changes were compared between the cohorts.
Results:
Of 2205 patients undergoing ARS, 38 (1.7%) met the criteria for hypercontractile esophagus and were matched to 76 controls. Preoperative symptom burden and reflux severity were similar between the groups. At 1 year, GERD-Health-Related Quality of Life scores, Eckardt scores, satisfaction (86.7% vs 80.4%; P =.561), freedom from proton pump inhibitor use (87.5% vs 83.6%; P =.765), and pH normalization rates (73.9% vs 76.3%; P =.788) were comparable between the cohorts. Patients with hypercontractile esophagus demonstrated a reduction in postoperative DCI, whereas controls demonstrated an increase (-1681.5 vs +235.6 mmHg·cm·s; P =.024). Among those who underwent postoperative manometry, 50% no longer met criteria for hypercontractile esophagus.
Conclusion:
Patients with preoperative manometric hypercontractility achieved symptomatic and objective reflux outcomes comparable to those of matched controls after ARS. Among patients who underwent postoperative manometry, half no longer met the criteria for hypercontractility, and contractile vigor decreased rather than demonstrating the compensatory increase observed in controls. These findings suggest that manometric hypercontractility may be modifiable after reflux correction in a subset of patients and, when identified during preoperative evaluation, should not be considered a contraindication to ARS in appropriately selected patients.

Related Concept Videos
 01:29
Gastroesophageal Reflux Disease II: Clinical Features and Management
Clinical Manifestations
GERD presents itself in a multitude of ways, with symptoms varying from person to person. The hallmark symptoms are...
 01:21
Barrett Esophagus-II: Clinical Manifestations and Management
To diagnose Barrett's esophagus, healthcare providers often recommend an endoscopy for those showing symptoms of acid reflux. The procedure entails...
 01:26
Esophageal Strictures-II: Clinical Features and Management
Healthcare providers should gather a comprehensive medical history and conduct a physical examination for diagnosis. If esophageal stricture is...
 01:30
Esophageal Strictures-I: Introduction
Etiology
The primary cause of esophageal strictures is long-standing gastroesophageal reflux disease (GERD), accounting for about 70 to 80% of adult cases. Chronic acid reflux can lead to injury and scarring of the esophageal lining, culminating in...
 01:27
Esophageal Achalasia
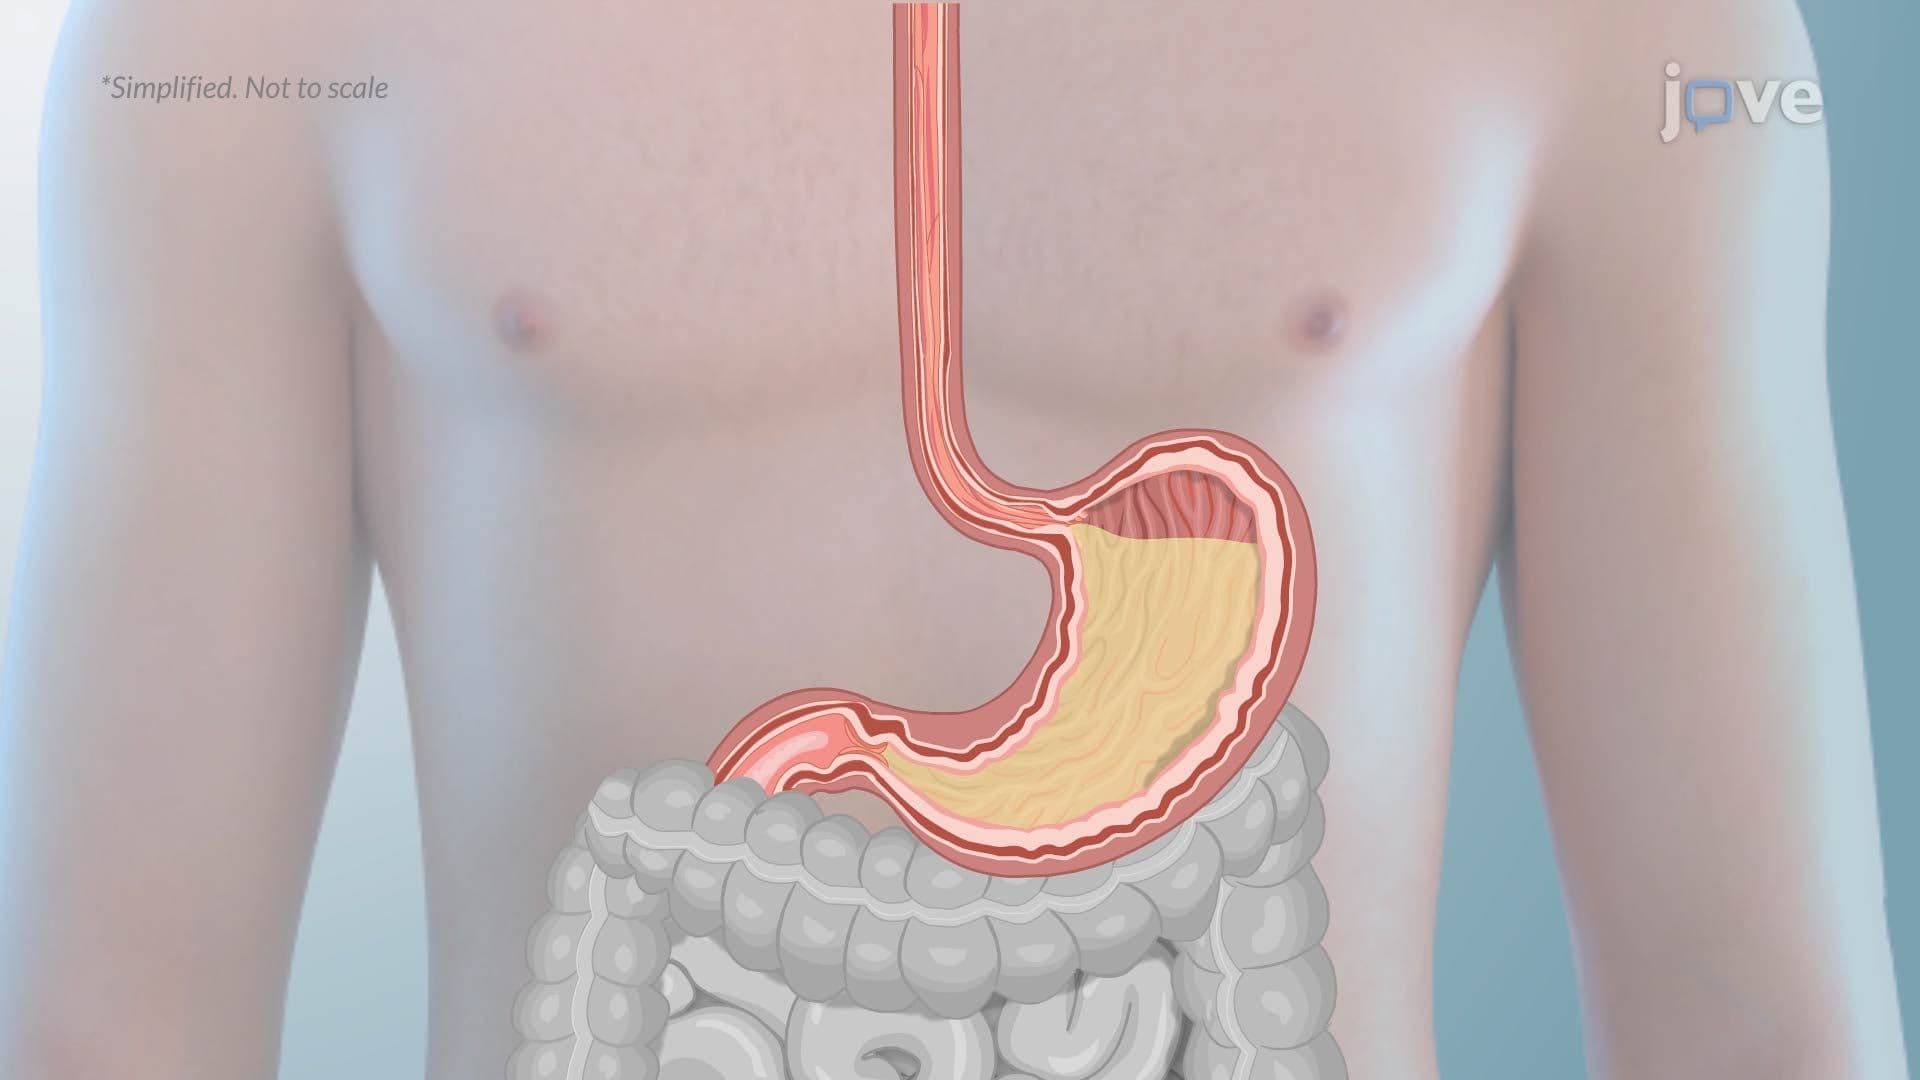 01:25
Gastroesophageal Reflux Disease