Related Experiment Video
Updated: Oct 1, 2026
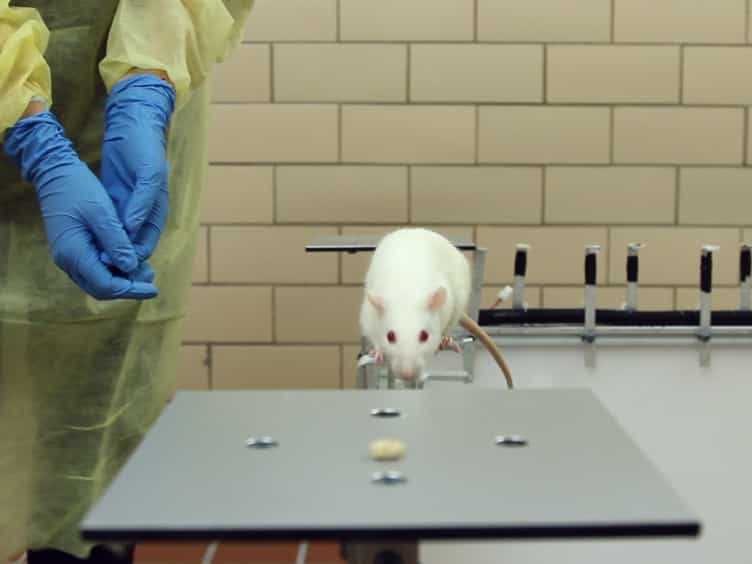

Asymmetric Walkway: A Novel Behavioral Assay for Studying Asymmetric Locomotion
Published on: January 15, 2016
Gait asymmetry phenotypes in subacute stroke: A cluster analysis of spatiotemporal parameters
1Department of Physical Therapy, College of Health Science, Yonsei University, Wonju, Republic of Korea; Department of Data Science Research, Seoul Rehabilitation Hospital, Seoul, Republic of Korea.

Background:
Gait asymmetry is a hallmark of post-stroke walking impairment, yet single-parameter measures may miss distinct multivariate patterns. Whether asymmetry-based phenotypes carry prognostic information independent of baseline clinical severity has not been tested.
Methods:
This retrospective cohort study included 245 individuals with subacute stroke who underwent instrumented walkway gait analysis. Seven variables-six asymmetry indices and leg-length-normalised walking velocity-were entered into k-means clustering. Cluster number was selected by three convergent criteria; stability was assessed by 1000 bootstrap resamples and cross-validation against partitioning around medoids. Functional Ambulation Category at discharge was modelled with cumulative link ordinal regression, with threshold-specific sensitivity analyses.
Findings:
Three clusters were identified (average silhouette width 0.308; bootstrap Jaccard ≥0.918): Cluster 1 (n = 70, "Stance-Phase Compensatory"), Cluster 2 (n = 112, "Near-Symmetric Fast") and Cluster 3 (n = 63, "Swing-Phase Dominant"). Unadjusted change in the Functional Ambulation Category differed among clusters (H = 18.20, ε2 = 0.067, P < 0.001), but cluster membership was not independently associated with the outcome after adjustment for its baseline value, age, onset time and lower-extremity Motricity Index (Cluster 2: odds ratio 0.94, 95% confidence interval 0.40-2.20; Cluster 3: 0.93, 0.48-1.79). Cluster effects were non-significant at every threshold in sensitivity analyses (all P ≥ 0.11).
Interpretation:
Three gait asymmetry phenotypes exist in subacute stroke, differentiated by swing-stance phase distribution. Their value appears descriptive-characterising qualitatively different compensation strategies-rather than prognostic; this requires prospective testing.

