Sentinel lymph node biopsy vs systematic lymphadenectomy for nodal staging in high-risk, early-stage endometrial cancer: a systematic review and meta-analysis
Related Experiment Video
Updated: Oct 1, 2026
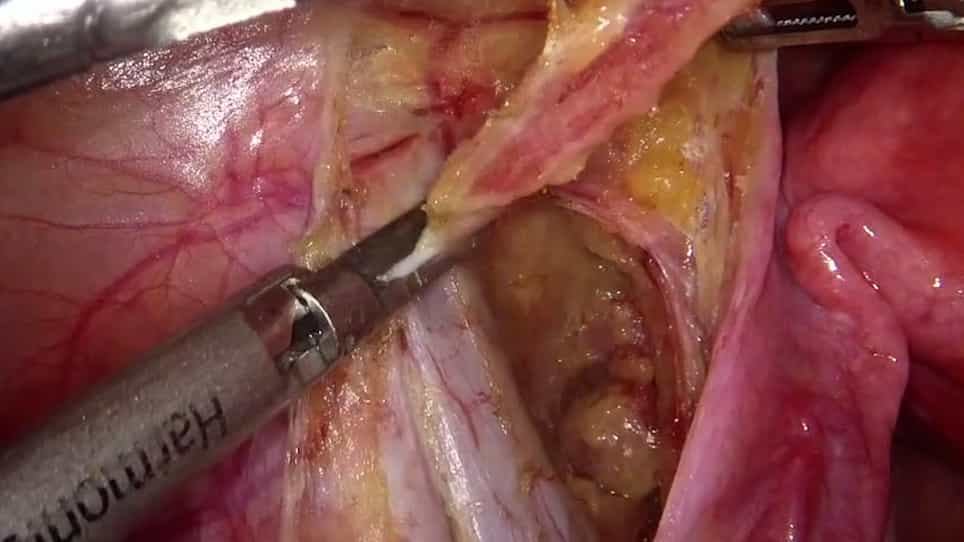
Sentinel Lymph Node Mapping and Biopsy for Endometrial Cancer at Early Stage with Laparoscopy
Published on: August 19, 2021
Suelen Queiroz1, Eurico Cleto Ribeiro de Campos1
1Department of Medicine, University of State of Ponta Grossa, Ponta Grossa, Brazil.

Background:
Sentinel lymph node (SLN) biopsy offers reduced morbidity compared with systematic lymphadenectomy (LND) for nodal staging in endometrial cancer, yet its oncologic safety in high-risk patients remains controversial. This study aimed to compare the nodal metastasis detection rate between SLN biopsy alone and systematic LND in women with high-risk, early-stage endometrial cancer.
Methods:
PubMed, EMBASE and the Cochrane Central Register of Controlled Trials were searched from database inception to 31 March 2025. Observational cohort studies comparing SLN biopsy alone with systematic LND (pelvic with or without para-aortic LND) in patients with high-risk endometrial cancer (FIGO stage I-II, grade 3 endometrioid, non-endometrioid histologies, or p53-abnormal molecular subtype) were included in this review. The primary outcome was the nodal metastasis detection rate. Pooled odds ratios (OR) with 95% confidence intervals (CI) were calculated using a DerSimonian-Laird random-effects model. Heterogeneity was assessed using the I2 statistic. This study followed PRISMA 2020 guidelines, and was registered prospectively with PROSPERO (CRD420261412396).
Findings:
Five observational cohort studies comprising 1327 patients (473 SLN, 854 LND) met the inclusion criteria. SLN biopsy detected significantly fewer nodal metastases than systematic LND (pooled OR 0.71, 95% CI 0.53-0.96; p=0.024). The pooled detection rate was 17.8% (84/473) in the SLN group vs 23.3% (199/854) in the LND group, representing an absolute difference of 5.5 percentage points. No statistical heterogeneity was observed (I2=0%; p for heterogeneity=0.77). Leave-one-out sensitivity analysis confirmed the robustness of the pooled estimate (OR range 0.68-0.74). A sensitivity analysis excluding the study by Gokce et al. yielded a pooled OR of 0.73 (95% CI 0.49-1.09; p=0.12), consistent in direction and magnitude with the primary analysis.
Interpretation:
SLN biopsy detects significantly fewer nodal metastases than systematic LND in high-risk, early-stage endometrial cancer. The interpretation that this reflects avoidance of over-staging rather than compromised oncologic safety is based on previously published survival data showing no difference between approaches. These findings highlight the need for prospective randomized trials to establish oncologic equivalence definitively. Based on these findings, coupled with the established reduction in morbidity associated with SLN biopsy, it is suggested that SLN biopsy should be the preferred nodal staging strategy for this population, pending confirmation from ongoing randomized controlled trials.