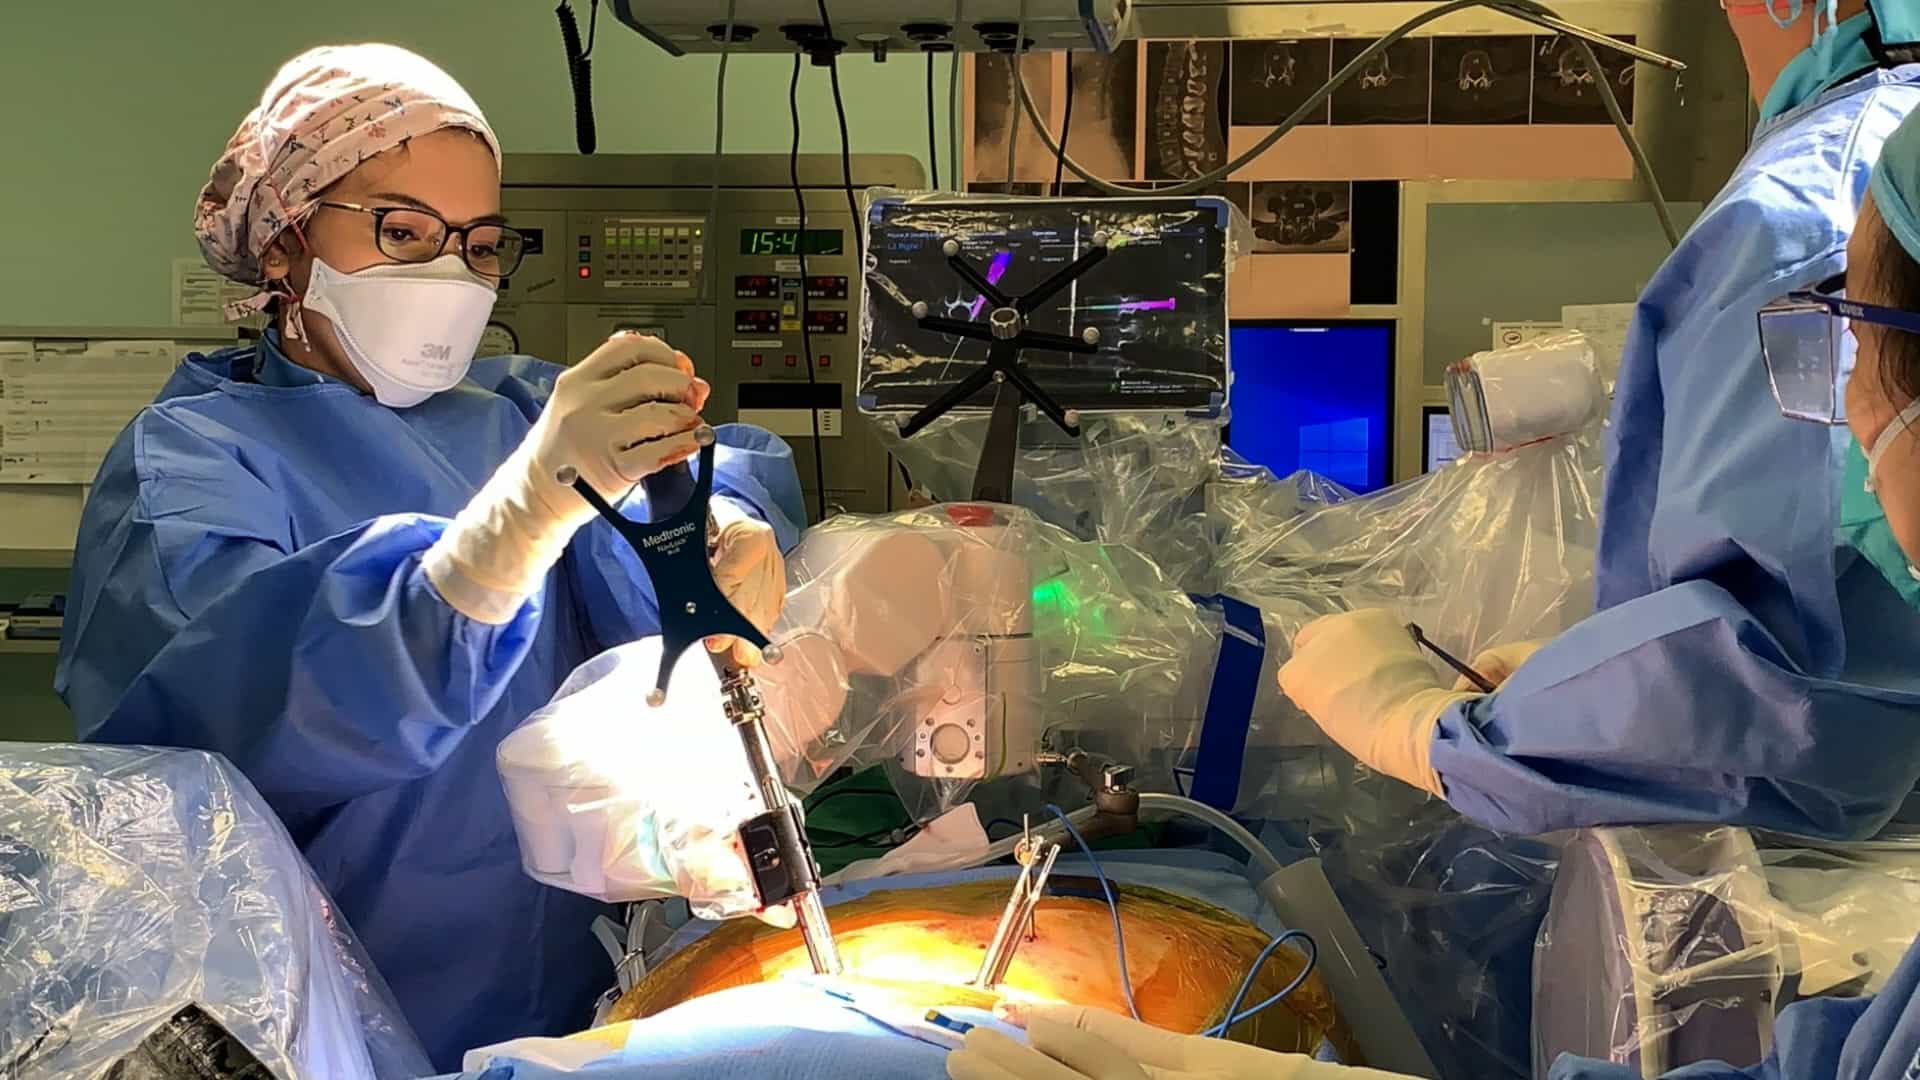
Related Experiment Video
Updated: Oct 1, 2026


Minimally Invasive Treatment for Thoracolumbar Burst Fracture Using Sagittal Alignment Screws and A Trauma Reduction Device
Published on: November 8, 2024
Robotic-assisted fixation with cortical bone trajectory versus conventional pedicle trajectory for short-segment
Wancheng Lin1, Yao Zhang1, Jipeng Song1
1Department of Spinal Surgery, Beijing Shijitan Hospital, Capital Medical University, Beijing, China.

Objective:
To compare the clinical outcomes of robotic-assisted fixation with cortical bone trajectory (RAF-CBT) versus conventional pedicle trajectory (RAF-CPT) in short-segment lumbar decompression and fusion.
Methods:
We conducted a retrospective, propensity score-matched cohort study. Patients undergoing short-segment decompression and fusion with robotic-assisted fixation for degenerative stenosis were assigned to RAF-CBT or RAF-CPT groups. The primary outcome was the change in Oswestry Disability Index (ODI) from baseline to 12 months. Secondary outcomes included changes in Japanese Orthopaedic Association (JOA) and Visual Analog Scale (VAS) scores, perioperative measures, radiographic results, and complications. Subgroup analyses focused on overweight/obese and osteoporotic patients.
Results:
After matching 82 pairs (n = 164), the RAF-CBT group showed a statistically significant but modest early improvement in ODI score at 1 month (difference, -3.66; 95% CI, -6.32 to -1.00; P = 0.0073), JOA score (difference, 0.99; 95% CI, 0.32 to 1.66; P = 0.0042) at 1 month and back pain VAS score (difference, -0.67; 95% CI, -1.18 to -0.16; P = 0.0107) at 1 week. Responder analysis showed significantly higher proportions of patients achieving MCID for ODI at 1 month (82.93% vs. 67.07%, P = 0.0191) and VAS back pain at 1 week (81.71% vs. 67.07%, P = 0.0318) in the RAF-CBT group. RAF-CBT was also associated with more favorable perioperative measures (incision length, operative time, blood loss, drainage, and hospital stay; all P < 0.0001). Radiographic outcomes and complication rates were similar. In the overweight/obese subgroup (n = 46 pairs), RAF-CBT showed more pronounced early benefits, with significantly greater ODI improvement at 1 month (difference, -4.04; 95% CI, -7.88 to -0.21; P = 0.0390) and back pain reduction at 1 week (difference, -0.91; 95% CI, -1.67 to -0.16; P = 0.0184). In the osteoporosis subgroup (n = 47 pairs), the rate of patients with ≥ 1 loosened screw was 14.89% in the RAF-CBT group versus 29.79% in the RAF-CPT group (P = 0.0830), with a GEE-adjusted OR of 0.45 (95% CI 0.18-1.12, P = 0.0860).
Conclusions:
In this propensity score-matched retrospective cohort, RAF-CBT showed favorable perioperative metrics and modest, statistically detectable early differences in patient-reported outcomes compared with RAF-CPT, while maintaining similar radiographic and 1-year outcomes. It was associated with specific advantages for overweight/obese and osteoporotic patients, suggesting its potential as a personalized surgical option.