Related Experiment Video
Updated: Oct 1, 2026

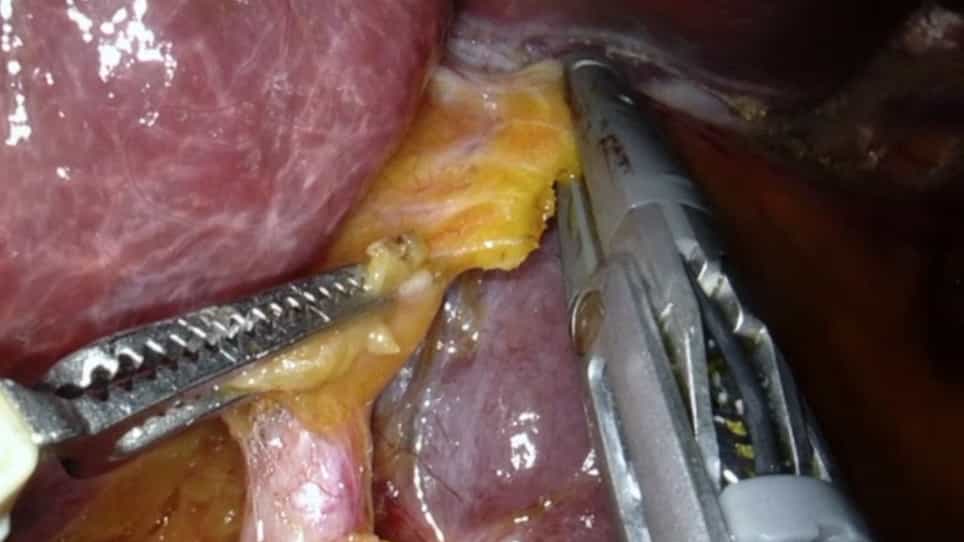
Laparoscopic Anterior Right Hepatectomy: A Single-Center Experience
Published on: December 4, 2023
Robotic versus laparoscopic anatomical hepatectomy: a post hoc analysis of the ROC'N'ROLL randomized controlled trial
Emrullah Birgin1,2, Marie Heibel3, Svetlana Hetjens4
1Department of General and Visceral Surgery, Ulm University Hospital, Ulm, Germany. emrullah.birgin@uniklinik-ulm.de.

Background:
Robotic liver surgery may overcome technical limitations of laparoscopic approaches, particularly for anatomical hepatectomy. Comparative prospective data remain limited.
Methods:
This exploratory post hoc analysis of the ROC'N'ROLL randomized controlled trial included patients scheduled for minimally invasive anatomical hepatectomy before randomization. Participants were randomized to robotic (RAH) or laparoscopic anatomical hepatectomy (LAH). The primary endpoint of this analysis was the rate of severe postoperative complications (Clavien-Dindo grade ≥ III) within 90 days. No subgroup-specific sample size calculation was performed. Secondary outcomes included conversion, operative time, blood loss, oncological outcomes, recovery, and patient-reported outcomes (PROs).
Results:
Among 81 randomized participants, 57 were scheduled for anatomical hepatectomy (RAH, n = 30; LAH, n = 27). Baseline imbalances were present, with larger tumors in the RAH group (median, 59 vs 40 mm; P = 0.048) and higher IWATE difficulty scores (median, 10 vs 7; P = 0.029). Operating time was longer with RAH (median, 252 vs 190 min; P = 0.021). Severe complications occurred in 13% after RAH and 37% after LAH (odds ratio, 0.27; 95% CI, 0.07-0.97; P = 0.045). No clear between-group differences were observed in conversion, blood loss, length of stay, functional recovery, margin status, mortality, or PROs.
Conclusions:
Robotic anatomical hepatectomy was associated with fewer severe complications despite higher procedural complexity. These exploratory findings support its use in high-difficulty cases but require prospective validation. (DRKS00027531).