Related Experiment Video
Updated: Oct 1, 2026


Clinical Efficacy of an Innovative Multidimensional Traction Therapy in Moderate Adolescent Idiopathic Scoliosis
Published on: February 10, 2026
From Spine to Limbs: Imaging Insights and Clinical Correlation in Caudal Regression Syndrome
1Dr Nafisa Munir, Radiologist, Department of Radiology and Imaging, Mymensingh Medical College Hospital, Mymensingh, Bangladesh;

Abstract:
Caudal regression syndrome (CRS) refers to a spectrum of congenital structural defects of the caudal region. We present a case of caudal regression syndrome with the objective of correlating the symptoms of caudal regression syndrome with the detailed imaging findings. A 05-year-old boy who was admitted to Mymensingh Medical College Hospital in August 2025 , presented with a post-urethroplasty state of hypospadias, complaining of urinary incontinence through the normal meatus and a urethrocutaneous fistula. He had dribbling of urine through hypospadias and deformed feet since birth. He also developed progressive lower limb weakness and walking difficulty at the age of 3 years. On clinical examination bilateral calf and hypothenar muscle wasting, reduced muscle power and tone, absent ankle and diminished knee jerks, diminished bulbocavernosus reflex, intact perianal sensation and anal tone were observed. Right-sided planovalgus (flat foot), left-sided cavus foot deformity, a smaller pelvic girdle with flat buttocks and hard swelling over the lower lumbar region were found. On x-ray lumbosacral spine both view, low-positioned L5 vertebra fused with a rudimentary S1 vertebra on the right with the absence of the rest of the sacral pieces and coccyx, broad spinous process of L5 were seen. Vertical talus, absent navicular bones and adducted forefeet and supinated great toes were seen on x-ray foot both view. RGU and MCU confirmed urethrocutaneous fistula. MRI of whole spine with contrast showed spinal cord and subarachnoid space termination at a slightly upper level with multifocal syrinx and anterior epidural lipoma. MR myelogram revealed short and thickened filum terminale. MR neurography demonstrated altered course of both sided lumbo-sacral plexus. Multifocal syrinx at cervical and dorso-lumbar vertebral levels resulted in lower motor type neuropathy and bladder incontinence. Though the patient had autonomic dysfunction of bladder due to the external urethral sphincter dysfunction, dribbling continued through the normal meatus and the weakest fistula tract evidenced by nil post voidal residue. This patient had no bowel incontinence due to intact inferior rectal nerve, a branch of pudendal nerve supplying the rectum.

Related Concept Videos
 01:16
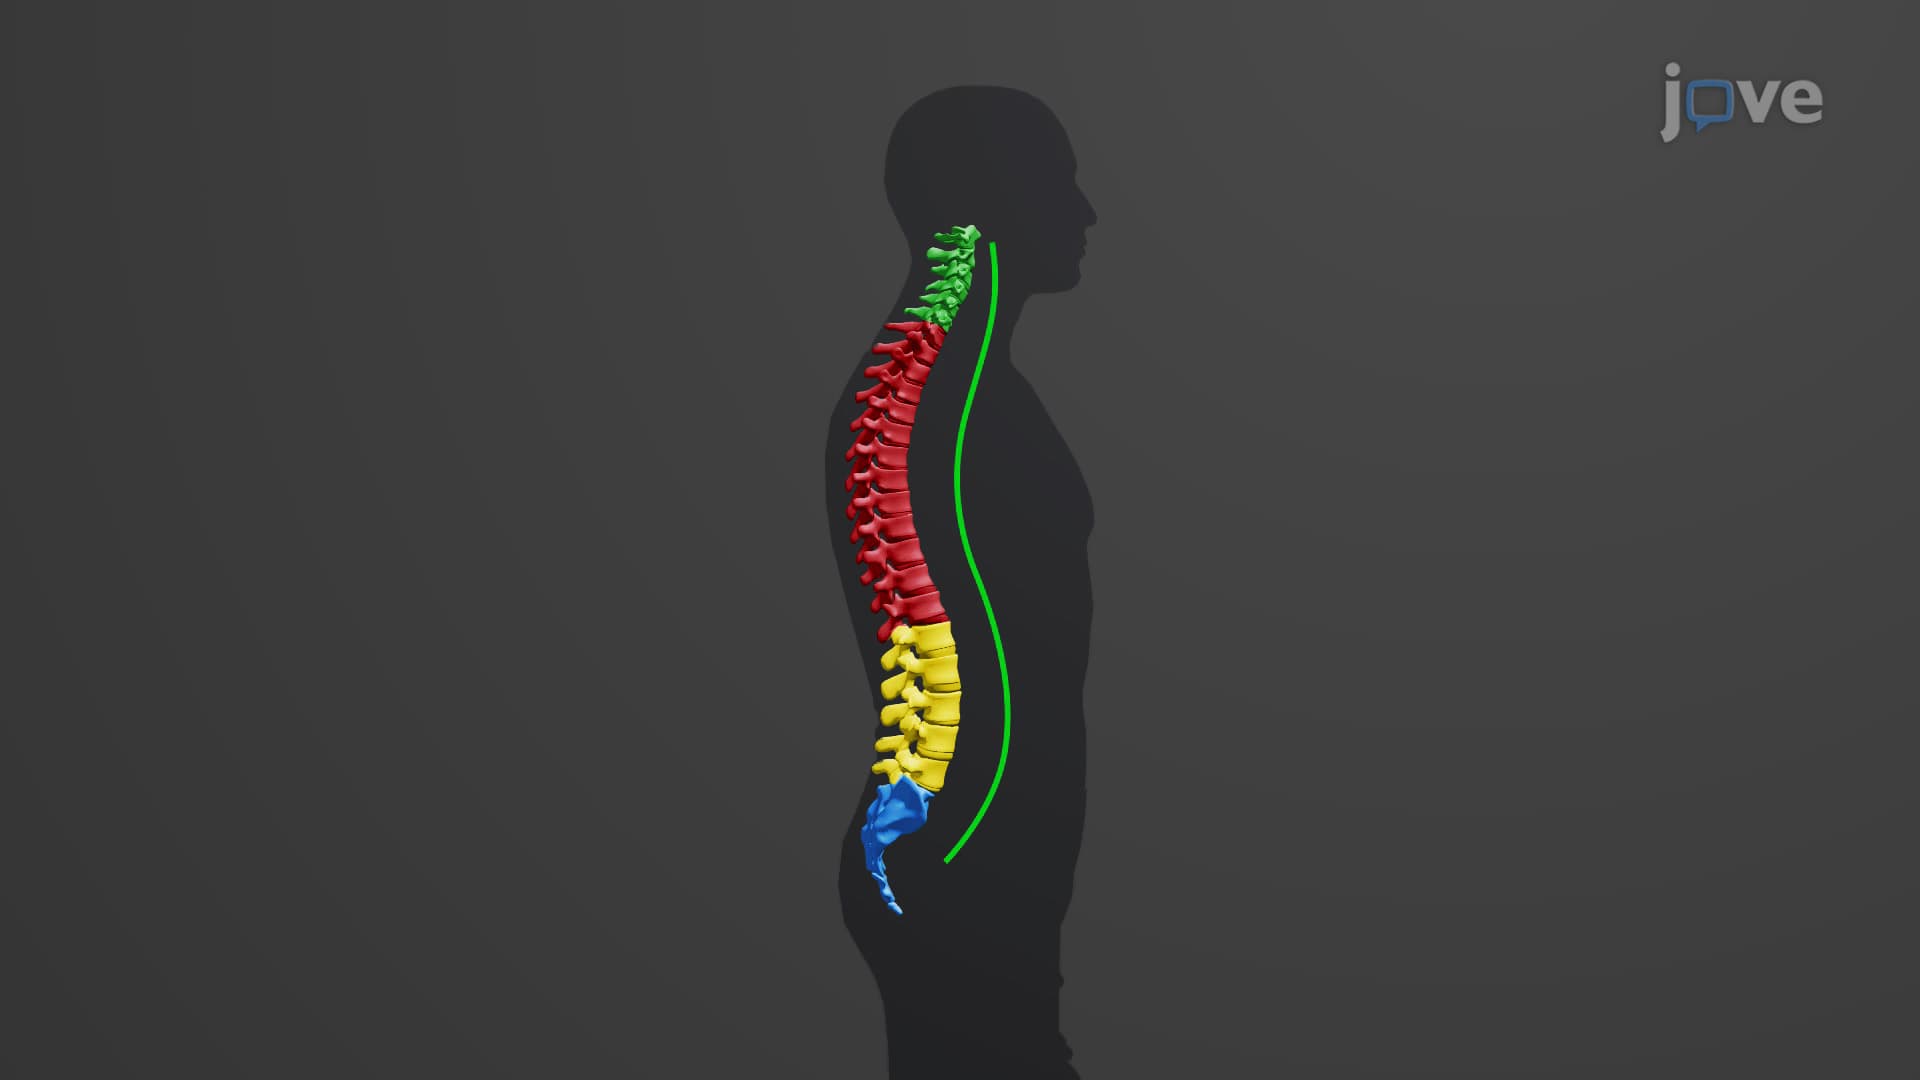
Vertebral Column: Regions and Curvature
Regions of the Vertebral Column
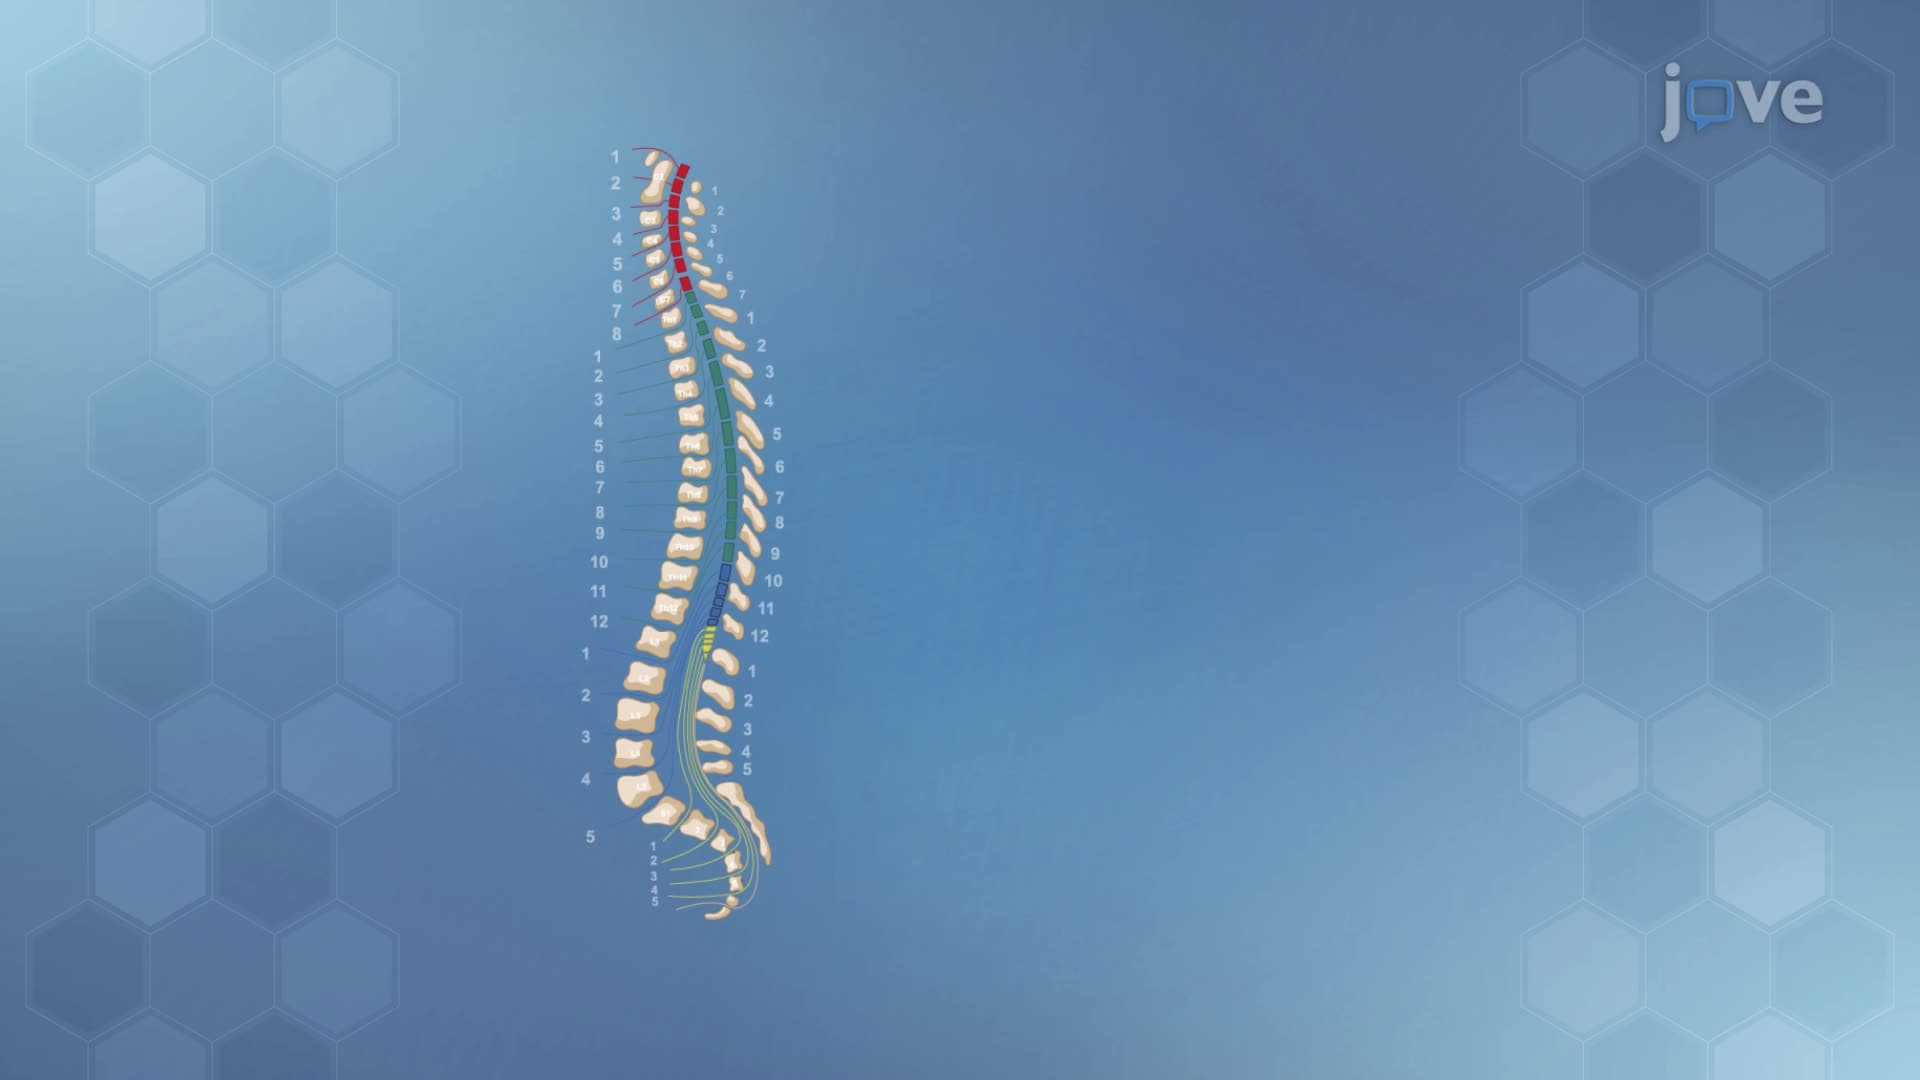
In an adult, the spine is subdivided into five regions: the cervical, the thoracic, the lumbar, the sacral, and the coccygeal region. The spine initially develops as a series of 33 vertebrae; after 20 years of age, the nine bones in the sacral region, five sacral, and four coccygeal bones fuse to form the...
 01:15
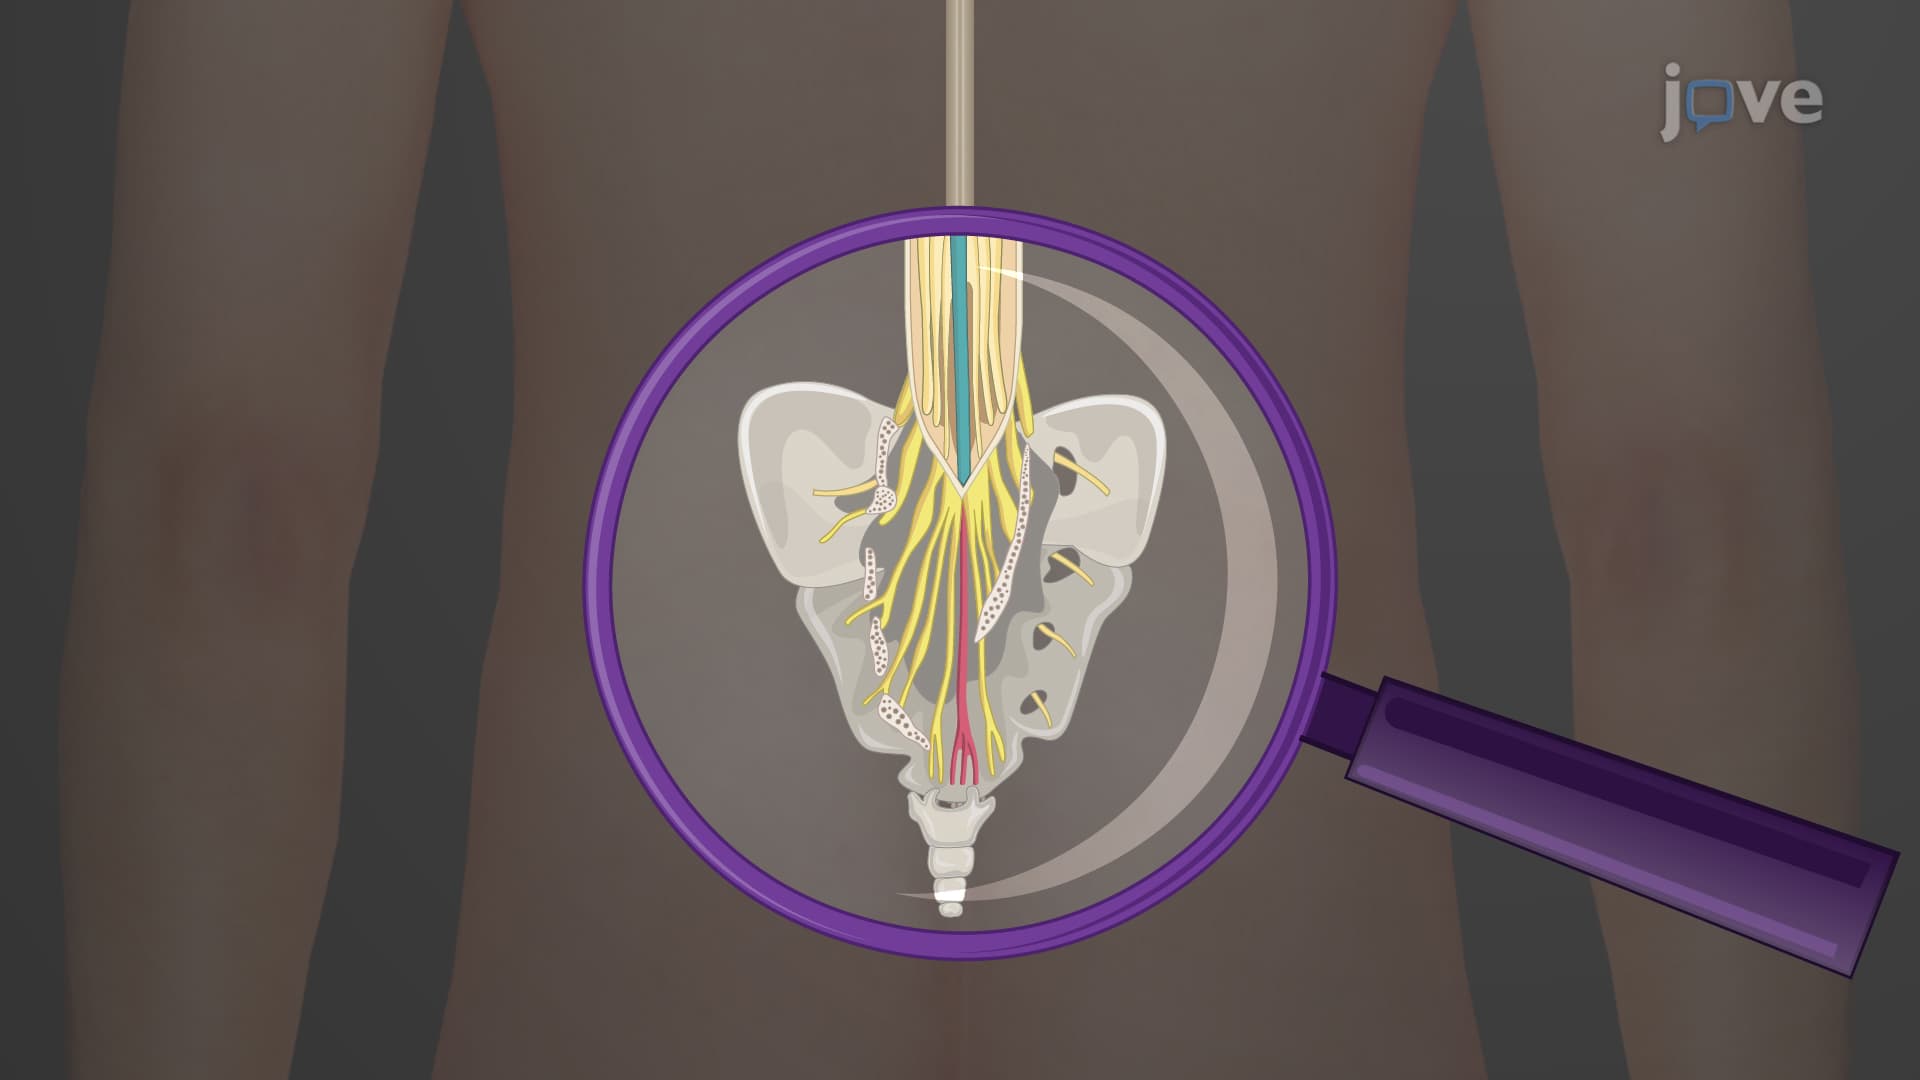
Spinal Cord: Gross Anatomy
 01:14
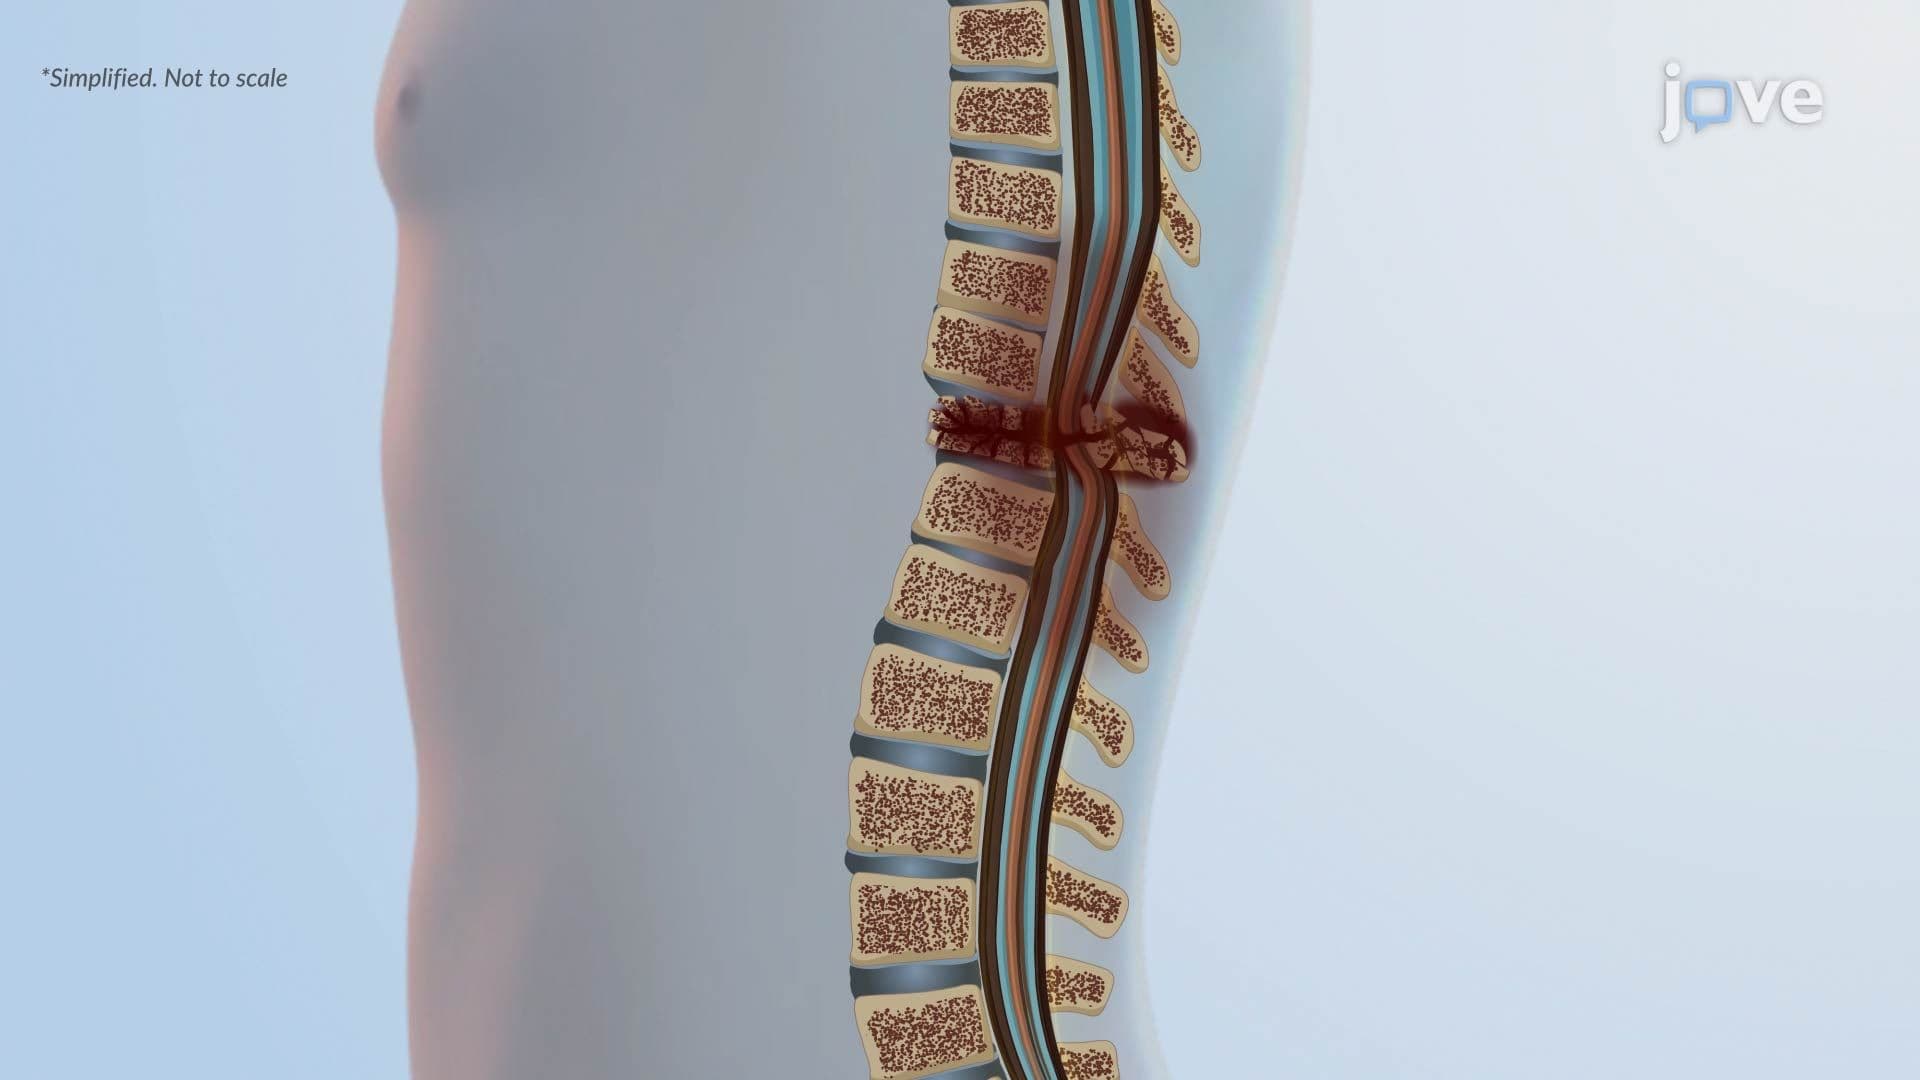
Spinal Cord Injury ll: Pathophysiology
 01:25
Secondary Spinal Cord Injury llI: Pathophysiology
 01:16
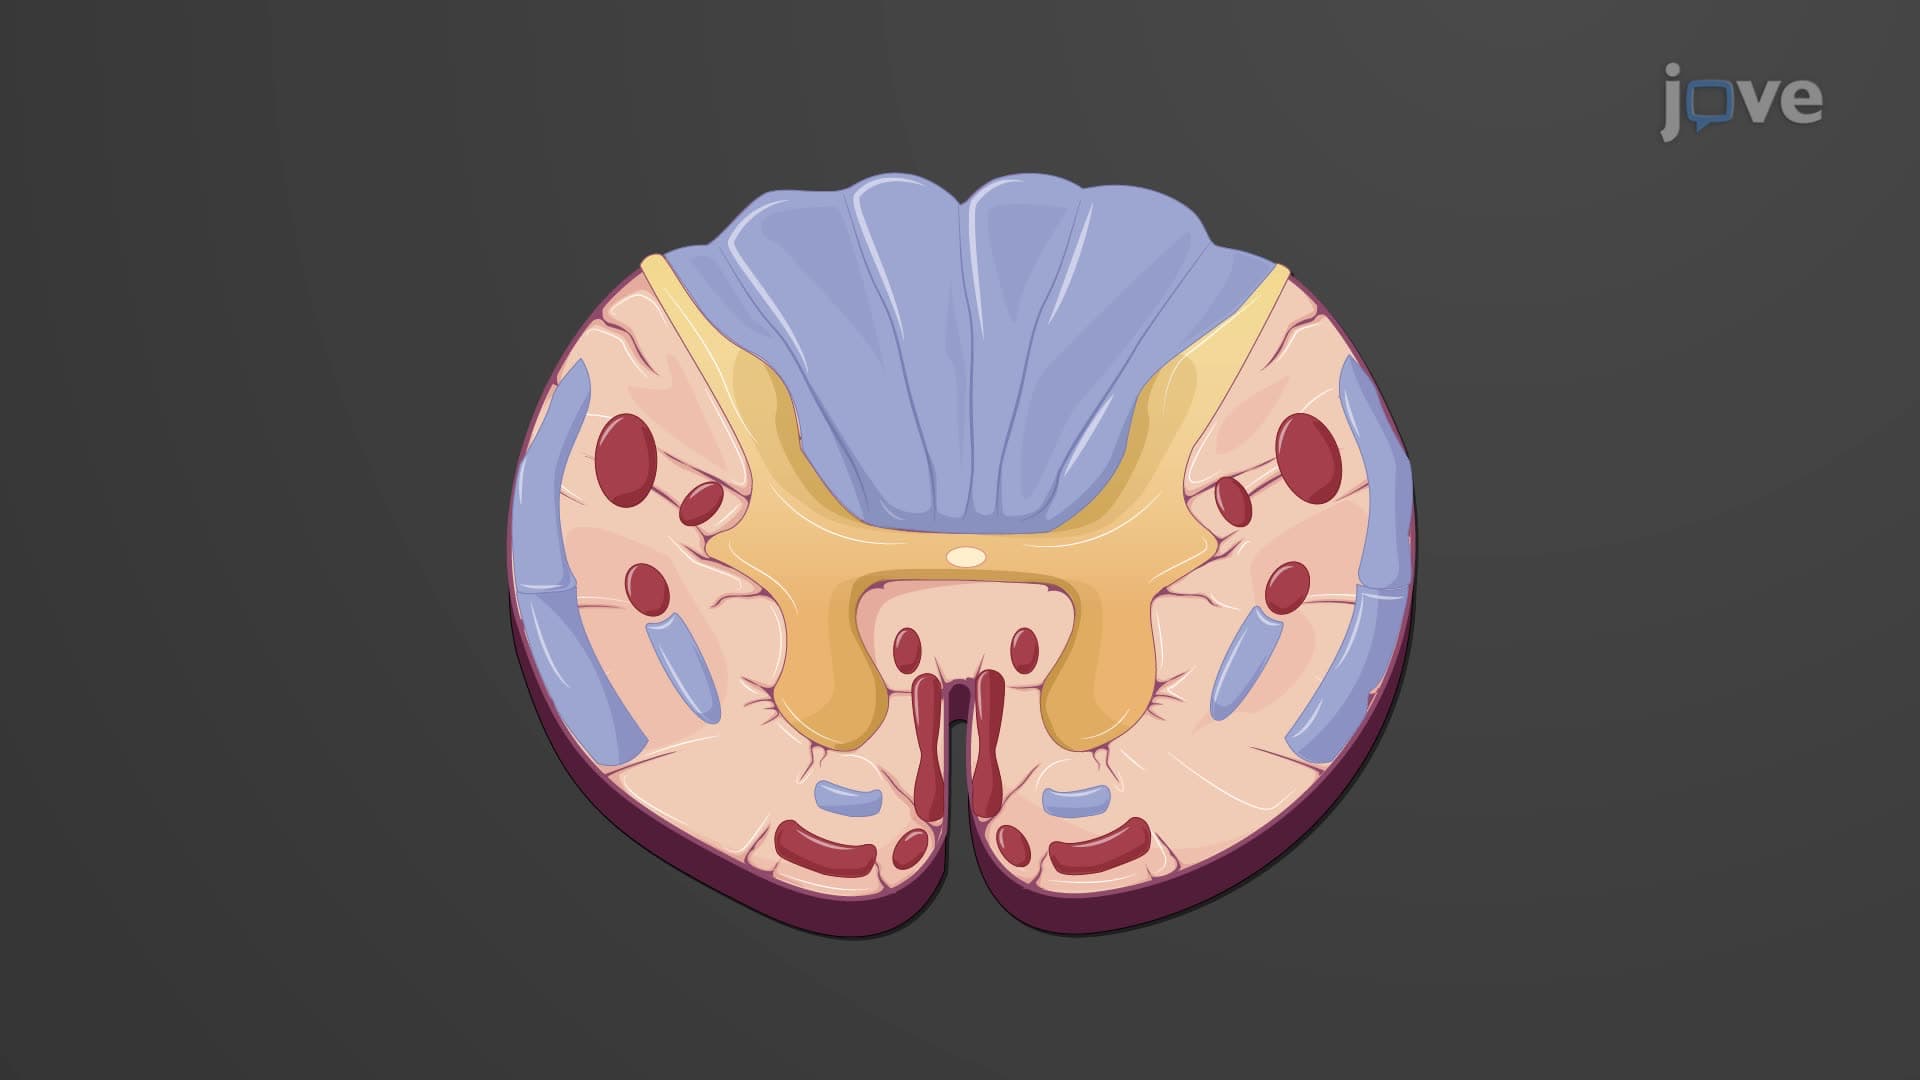
Spinal Cord: Cross-sectional Anatomy
Gray Matter and its Components
Central to the gray matter is...
 01:26
Spinal Cord