Related Experiment Video
Updated: Oct 1, 2026
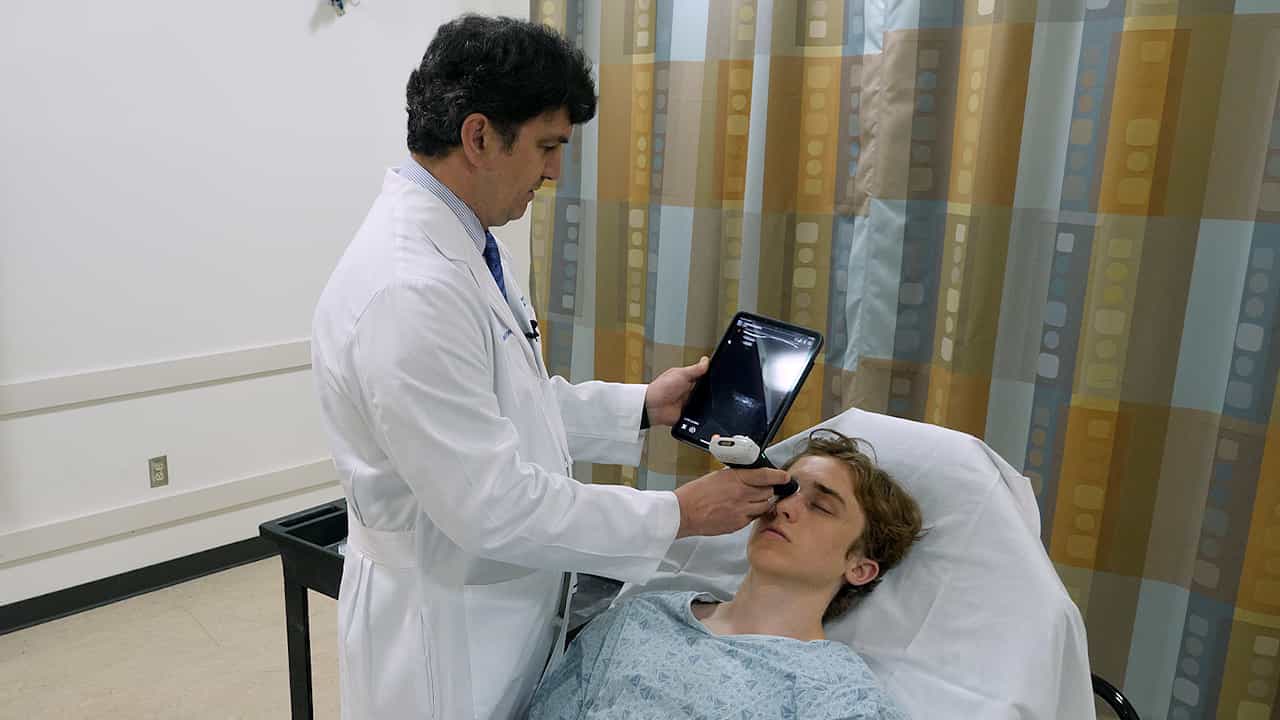

Optic Nerve Sheath Point of Care Ultrasound: Image Acquisition
Published on: August 18, 2023
Association between perioperative optic nerve sheath diameter and postoperative delirium after Bentall surgery: a
Anıl Onur1, Korgün Ökmen1, Tuğba Onur1
1Department of Anesthesiology and Reanimation, University of Health Sciences, Bursa Yüksek İhtisas Training and Research Hospital, Bursa, Türkiye.

Background:
Optic nerve sheath diameter (ONSD) is an indirect, technique-dependent marker of intracranial pressure; its association with delirium after Bentall surgery remains uncertain. Therefore, we assessed serial perioperative ONSD and its relationship with delirium.
Methods:
This prospective single-centre study included 53 adults undergoing elective Bentall surgery. Delirium analyses included 51 participants whose status was assessable with the Confusion Assessment Method for the Intensive Care Unit; two remained unassessable until death. Bilateral ONSD was measured at 10 perioperative time points. Mixed-effects models evaluated serial ONSD, time-point comparisons were Holm-adjusted, and measures underwent Firth regression and receiver operating characteristic analyses. Sensitivity analyses assigned each indeterminate outcome as either delirium present or absent.
Results:
Documented delirium occurred in 17 of 51 participants with assessable delirium status (33.3%). Average perioperative ONSD was 0.250 mm higher with delirium (95% confidence interval 0.031-0.470; p = 0.025). Across outcome assignments, the difference ranged from 0.237 to 0.248 mm (p-values ≤ 0.029), whereas the time-by-group interaction was sensitive to assignment (p-values ranged from <0.001 to 0.094). No point-specific comparison survived Holm correction (smallest adjusted p = 0.078), and the post-closure T6 minus preoperative baseline showed no clear group difference (p = 0.147). In an exploratory Firth analysis not adjusted for time-point selection, the odds ratio per 1-mm higher T6 ONSD was 3.75 (95% confidence interval 1.44-12.32; p = 0.005). Areas under the receiver operating characteristic curves were 0.654 for Preop, 0.689 for T0, 0.728 for T6, and 0.626 for change, without evidence of superior T6 discrimination. The five-variable model had an apparent area under the curve of 0.839 and a conditional optimism-corrected value of 0.778; predictor and time-point selection were not repeated during validation. The internally selected 4.90-mm operating point was not an intracranial-hypertension threshold.
Conclusions:
Higher perioperative ONSD was associated with documented delirium, but the temporal interaction was sensitive to unobserved outcomes, and the data did not establish a superior time point or a causal intraoperative change. These findings require external validation.
Trial Registration:
ClinicalTrials.gov NCT07452367; retrospectively registered 5 March 2026.